Related Experiment Video
Updated: Aug 29, 2026


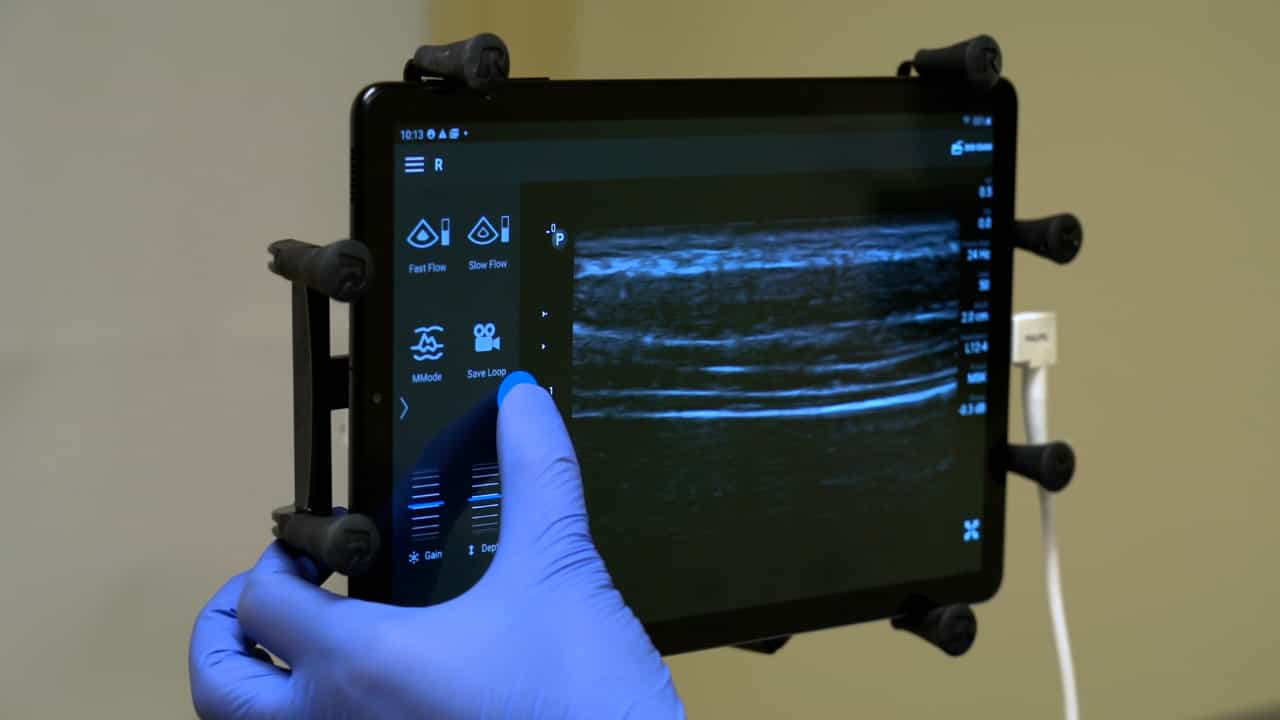
Diaphragmatic Ultrasound in Adults: Image Acquisition and Interpretation
Published on: January 31, 2025
[Diagnostic study on children's diaphragmatic fatigue]
Yun-gang Yang1, Zheng-xia Zhang, Liang-gang Hu
1Department of Pediatrics, Xiamen First Hospital, Xiamen 361003, China.

Insights
This study introduces impedance respirography (IRG) as a simple, non-invasive method to diagnose diaphragmatic fatigue in children. IRG effectively categorizes fatigue into three types, guiding timely intervention to prevent respiratory failure.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Diagnostic Technology
Background:
- Diagnosing diaphragmatic fatigue in children is challenging due to limitations of existing methods like EMG and Pdi.
- There is a need for accessible, non-invasive techniques to evaluate diaphragmatic function in pediatric patients.
Purpose of the Study:
- To explore the diagnosis of diaphragmatic fatigue in children using ribcage-abdomen motion analysis via impedance respirography (IRG).
- To analyze the asynchrony of ribcage-abdomen motion and correlate it with physiological parameters.
Main Methods:
- Fifty-three children with signs of respiratory dysfunction underwent impedance respirography (IRG) to assess ribcage-abdomen motion synchrony.
- M levels and alpha angles were calculated from IRG data, alongside measurements of respiratory rate, heart rate, and arterial blood gases.
Main Results:
- Asynchronized respiratory motion was classified into three types (I, II, III) based on IRG patterns (M levels, alpha angles).
- Type I and II diaphragmatic fatigue showed significantly lower pH and higher PCO2 levels compared to Type III and normal subjects.
- Respiratory and heart rates were elevated in all fatigue types, with significant differences among them.
Conclusions:
- Impedance respirography (IRG) is a reliable, simple, and non-invasive tool for diagnosing diaphragmatic fatigue in children.
- Diaphragmatic fatigue can be categorized into three distinct types based on IRG characteristics.
- Identifying Type III diaphragmatic fatigue via IRG is crucial for timely intervention to prevent respiratory failure.
Objective:
In the recent twenty years, the diaphragmatic contraction, relaxation functions and electric activity have been explored through electromyography (EMG) and transdiaphragmatic pressure (Pdi) determination. But these techniques required some complex and expensive instruments, so the diagnosis and treatment of children's diaphragmatic fatigue have not been well evaluated. The present study explored the diagnosis of children's diaphragmatic fatigue through measuring ribcage-abdomen motion and analyzed its asynchrony.
Methods:
Fifty-three children (male 37, female 16, and age rage from 1 months to 9 years) with respiratory rate > 30 breaths/min, heart rate > 110 beats/min, and respiratory dysfunction had asynchronized ribcage-abdomen motion showed by impedance respirograph (IRG). The authors observed whether ribcage-abdomen motion was synchronic and calculated M levels (staggered peak time/total duration of the breathing cycle). The ribcage and abdomen outputs were displayed on vertical (for rib cage) and horizontal (for abdomen) axes of X-Y instrument. In addition, the change of respiratory frequency and heart rate was observed and arterial blood-gas analysis was also performed.
Results:
(1) M levels in one-dimensional IRG were positively correlated with alpha angle in two-dimensional IRG (r = 0.956, P < 0.001). Asynchronized respiratory motions could be divided into three types. type I showed completely contra-directional movements of respiration, M levels for (48.1 +/- 4.4)%, an irregularly clockwise loop in the two dimensional IRG, and alpha angle for (138.3 +/- 15.0) degrees. In type II, one dimensional IRG showed displaced peak of the chest and abdomen motion curves, M levels were (16.5 +/- 4.7)%, two dimensional IRG was displaced in a counterclockwise direction, and alpha angle was (55.3 +/- 10.8) degrees. In type III, abdominal motion curve of one dimensional IRG had double peaks, M levels were 0, two dimensional IRG was presented as 8-shaped double circles, alpha angle was (41.3 +/- 3.8) degrees; (2) pH levels in the patients with type I and type II diaphragmatic fatigue were significantly lower, and PCO(2) levels were significantly higher than those with type III or in the normal subjects (P < 0.001 for all), but there was no statistically significant difference between type III and the normal subjects (P > 0.05); (3) Both of respiratory rate and heart rate in type I, type II and type III were higher than those in the normal subjects (all P < 0.001), and the differences among the three types were significant (P < 0.001 for all); (4) Both M levels and alpha angle were negatively correlated with pH levels (r = -0.514, P < 0.001 and r = -0.497, P < 0.001), while positively correlated with PCO(2) levels (r = 0.672, P < 0.001 and r = 0.625, P = 0.01).
Conclusions:
(1) IRG can be reliably used to diagnose children's diaphragmatic fatigue. This technique is simple and easy to perform and non-invasive. It is therefore worthy of recommending for further clinical investigations. (2) According to the characteristics of IRG, diaphragmatic fatigue can be divided into three types. (3) The development of children's diaphragmatic fatigue has a series of characteristic changes. (4) To avoid the patients suffering from respiratory failure, it is the key time to adopt the policies of prevention and treatment when IRG shows signs of type III diaphragmatic fatigue.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...