Electronic monitoring and voice prompts improve hand hygiene and decrease nosocomial infections in an intermediate care unit
Related Experiment Video
Updated: Aug 29, 2026

A Method to Test the Efficacy of Handwashing for the Removal of Emerging Infectious Pathogens
Published on: June 7, 2017
Sandra M Swoboda1, Karen Earsing, Kevin Strauss
1Johns Hopkins University School of Medicine, Baltimore, MD, USA.

Objective:
To determine whether electronic monitoring of hand hygiene and voice prompts can improve hand hygiene and decrease nosocomial infection rates in a surgical intermediate care unit.
Design:
Three-phase quasi-experimental design. Phase I was electronic monitoring and direct observation; phase II was electronic monitoring and computerized voice prompts for failure to perform hand hygiene on room exit; and phase III was electronic monitoring only.
Setting:
Nine-room, 14-bed intermediate care unit in a university, tertiary-care institution. All patient rooms, utility room, and staff lavatory were monitored electronically.
Participants:
All healthcare personnel including physicians, nurses, nursing support personnel, ancillary staff, all visitors and family members, and any other personnel interacting with patients on the intermediate care unit. All patients with an intermediate care unit length of stay >48 hrs were followed for nosocomial infection.
Interventions:
Electronic monitoring during all phases, computerized voice prompts during phase II only.
Measurements And Main Results:
We evaluated a total of 283,488 electronically monitored entries into a patient room with 251,526 exits for 420 days (10,080 hrs and 3,549 patient days). Compared with phase I, hand hygiene compliance in patient rooms improved 37% during phase II (odds ratio, 1.38; 95% confidence interval, 1.04-1.83) and 41% in phase III (odds ratio, 1.41; 95% confidence interval, 1.07-1.84). When adjusting for patient admissions during each phase, point estimates of nosocomial infections decreased by 22% during phase II and 48% during phase III; when adjusting for patient days, the number of infections decreased by 10% during phase II and 40% during phase III. Although the overall rate of nosocomial infections significantly decreased when combining phases II and III, the association between nosocomial infection and individual phase was not significant.
Conclusions:
Electronic monitoring provided effective ongoing feedback about hand hygiene compliance. During both the voice prompt phase and post-intervention phase, hand hygiene compliance and nosocomial infection rates improved suggesting that ongoing monitoring and feedback had both a short-term and, perhaps, a longer-term effect.

Related Concept Videos
 01:23
Hand hygiene
Hand washing...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:18
Handwashing I: Introduction and Types of Equipment
Hand wash basins in clinical areas should have faucets that can be turned on and off without using the hands; that is, they should be non-touch or lever-operated.
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:15
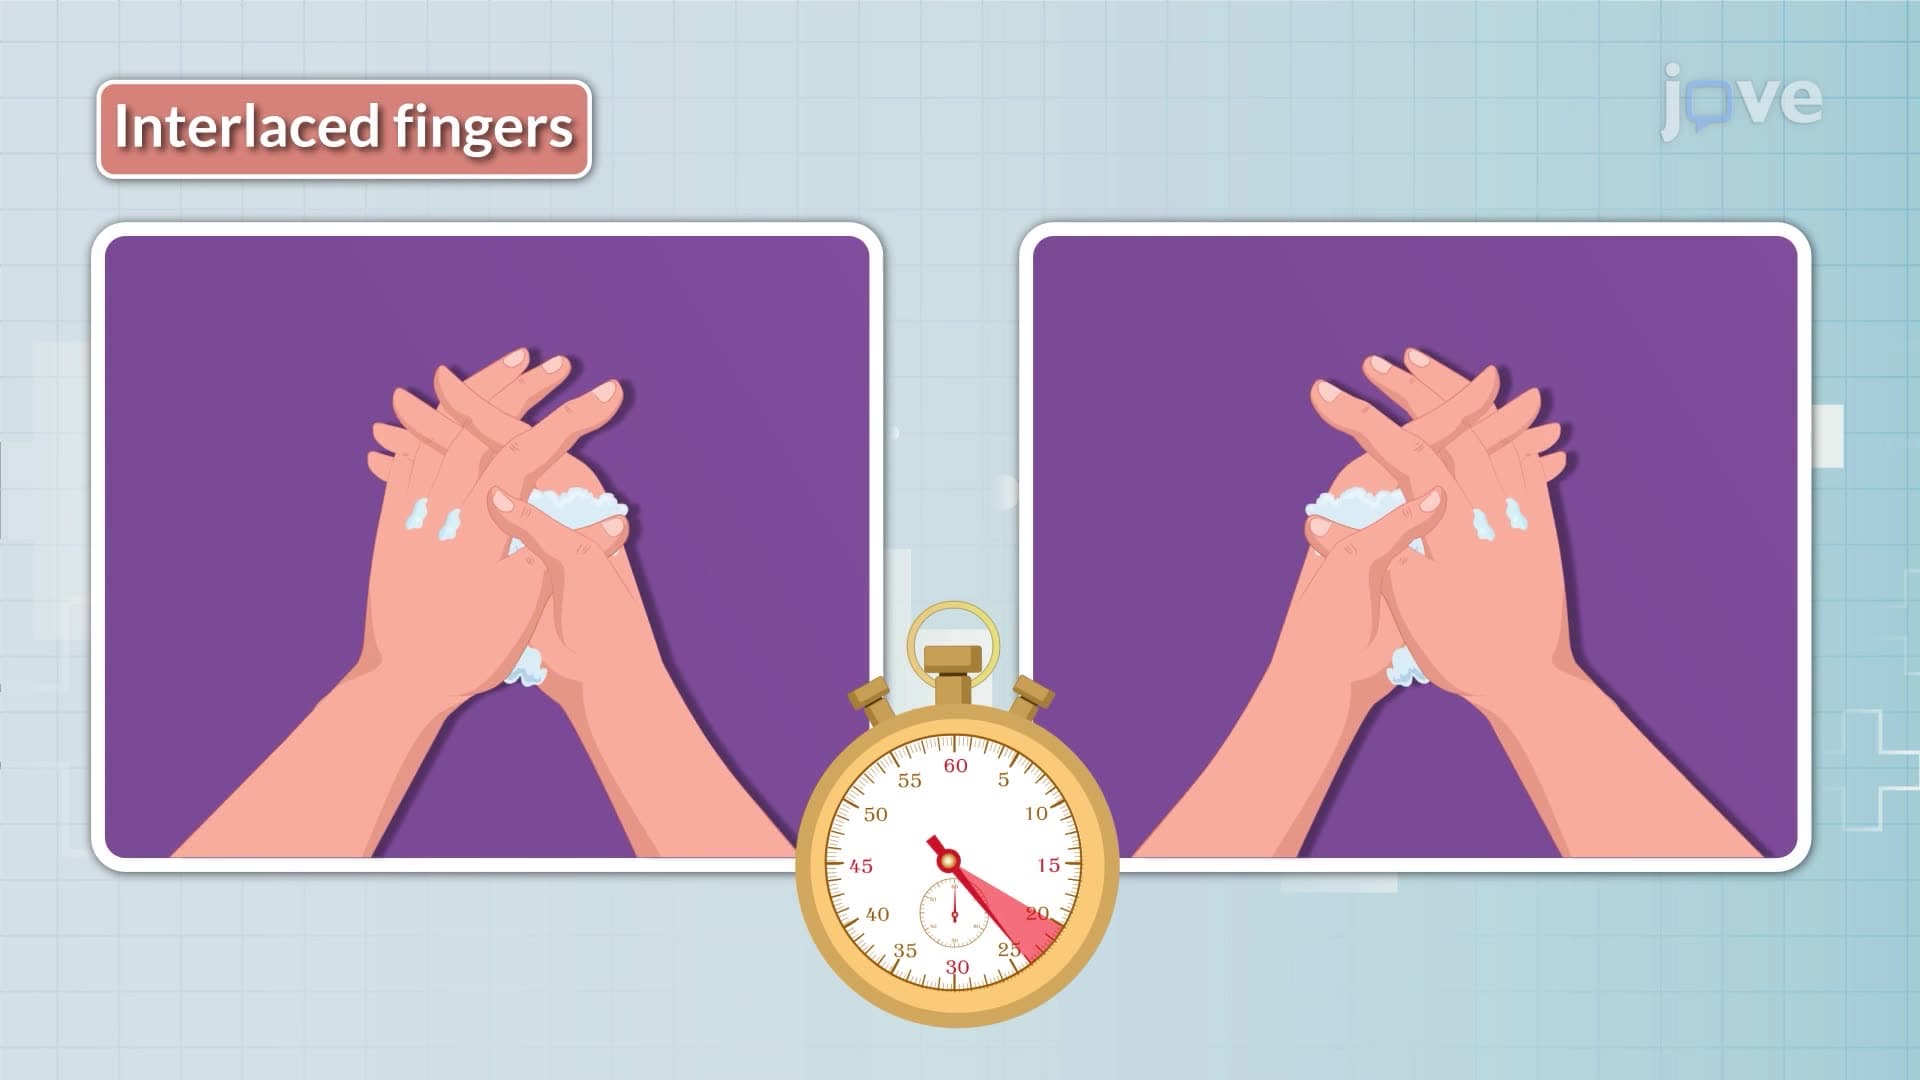
Handwashing III: During the Procedure and Post-Procedure Steps
 01:19
Handwashing II: Pre-procedure and Initial Procedure Steps
The hand washing procedure itself includes the following steps. First, cover cuts, if any, on hands with a waterproof dressing. Cuts and abrasions can become contaminated with bacteria hindering the ability to clean the area thoroughly. In addition, repeated hand washing can worsen an injury. The nails must be short and clean, without nail paint...