Related Experiment Video
Updated: Aug 26, 2026
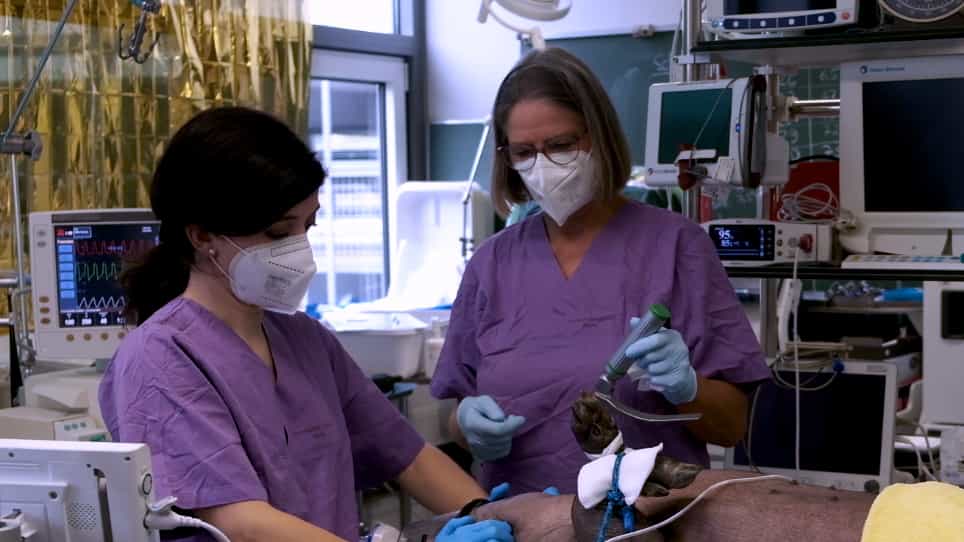

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Management of unanticipated difficult intubation: a survey of current practice in the Oxford region
A Bokhari1, S W Benham, M T Popat
1The John Radcliffe, Nuffield Department of Anaesthetics, Headley Way, Oxford, UK. asima.bokhari@orh.nhs.uk

Background And Objective:
Unanticipated difficulty in tracheal intubation in an anaesthetized patient has always been a cause of concern to anaesthesiologists. This difficulty may lead to morbidity and mortality. This survey was carried out to determine the technique commonly favoured in centres in the Oxford region in the UK for the management of unanticipated difficult intubation.
Methods:
We conducted a clinical scenario-based questionnaire survey of 181 anaesthesiologists in the Oxford region. In this scenario, difficulty in endotracheal intubation is recognized only after induction of anaesthesia. A number of options were available to deal with this situation. We used this scenario as a tool to gain insight into the training and the training needs of anaesthesiologists at various levels of training.
Results:
Of the 181 questionnaires sent, we received 143 (79%) completed replies. The vast majority (141/143 (99%)) of anaesthesiologists would use a gum-elastic bougie together with head and neck positioning and optimal external laryngeal manipulation to gain the best attempt at intubation. If intubation still failed, overall 129/143 (90%) had a back-up plan, while 14/143 (10%) had no plan. Flexible fibreoptic techniques were more commonly planned by 92/143 (64%) anaesthesiologists compared to blind techniques which were less commonly planned by 37/143 (26%) anaesthesiologists. Differences in choice of technique among anaesthesiologists in teaching and district general hospitals were not significant (P = 0.87). Overall, trainees were less likely to choose fibreoptic techniques compared to consultants (P = 0.0009) and would use blind techniques or ask a more experienced colleague to take over. The main reason for the choice was previous experience with the technique.
Conclusions:
Although fibreopric techniques were most commonly planned, these were less often chosen by trainees than consultants due to lack of experience/training, while unavailability of intubating laryngeal mask airway (Intavent) was an additional issue precluding its use as an adjunct to intubation.


Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...