Vascular and connective tissue diseases in the paediatric world
Related Experiment Videos
1Department of Paediatrics, Rheumatology Unit, University of Florence, Firenze, Italy. falcini@unifi.it

Insights
Pediatric rheumatologists face challenges with connective tissue diseases. New immunosuppressant therapies and aggressive treatments improve outcomes for juvenile lupus and dermatomyositis, while other conditions like Kawasaki disease and Henoch-Schönlein purpura require ongoing research.
Area of Science:
- Pediatric Rheumatology
- Connective Tissue Diseases
- Immunology
Background:
- Connective tissue diseases present ongoing challenges in pediatric rheumatology despite recent advances.
- Current therapeutic regimens, while improved, necessitate further refinement for optimal patient outcomes.
Purpose of the Study:
- To review current therapeutic strategies for various pediatric connective tissue diseases.
- To highlight areas of therapeutic consensus and ongoing debate in pediatric rheumatology.
- To suggest optimized treatment approaches for improved survival and reduced organ damage.
Main Methods:
- Review of existing literature on classification, outcomes, and therapeutic regimens for pediatric connective tissue diseases.
- Analysis of treatment effectiveness and controversies for specific conditions including juvenile SLE, dermatomyositis, Henoch-Schönlein purpura, Kawasaki disease, and polyarteritis nodosa.
Main Results:
- Corticosteroids remain first-line for juvenile SLE, but immunosuppressants are suggested for better survival and less organ damage.
- Aggressive treatment with corticosteroids and methotrexate improves prognosis in juvenile dermatomyositis.
- Treatment for Henoch-Schönlein purpura and Kawasaki disease shows ongoing debate, particularly regarding corticosteroid use and renal involvement.
- Polyarteritis nodosa requires aggressive corticosteroid and immunosuppressant therapy, while cutaneous polyarteritis needs infection control and penicillin prophylaxis.
Conclusions:
- A shift towards immunosuppressant therapy is warranted for juvenile SLE to improve long-term outcomes.
- Optimized and aggressive treatment strategies are crucial for improving prognosis in juvenile dermatomyositis.
- Further research is needed to establish definitive treatment guidelines for Henoch-Schönlein purpura and Kawasaki disease, especially concerning corticosteroid efficacy and management of incomplete diagnostic criteria cases.
- Effective management of polyarteritis nodosa and cutaneous polyarteritis involves aggressive immunosuppression and infection control, respectively.
Abstract:
Despite the fact that in recent decades many advances have been made in classification, outcomes measurements and therapeutic regimens, connective tissue diseases remain a challenge for paediatric rheumatologists. Corticosteroids are still the first choice therapy in juvenile systemic lupus erythematosus (SLE); however, it is time for a new therapeutic approach with immunosuppressant drugs in order to obtain a more prolonged survival and reduced organ system damage. A prevention of relapse of thromboembolic phenomena using low-dose aspirin is strongly suggested in children with anticardiolipin antibodies, particularly in those with SLE. The long-term prognosis in juvenile dermatomyositis is significantly improved due to a more aggressive treatment with corticosteroids and methotrexate. The treatment of Henoch-Schöenlein purpura is still under debate, and no agreement has been reached regarding the role of corticosteroids in the prevention of renal involvement. The management of the acute phase of Kawasaki disease is now well established, although there is controversy regarding the role of corticosteroids. It is still under debate how and whether to treat patients who do not fulfil the diagnostic criteria. Polyarteritis nodosa is a disease at risk of death and requires an aggressive approach with corticosteroids and immunosuppressants, while cutaneous polyarteritis needs a close control of an underlying streptococcus infection and prophylaxis with benzatin-penicillin to prevent relapses.
Related Concept Videos
 01:20
Overview of the Vascular System
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:20
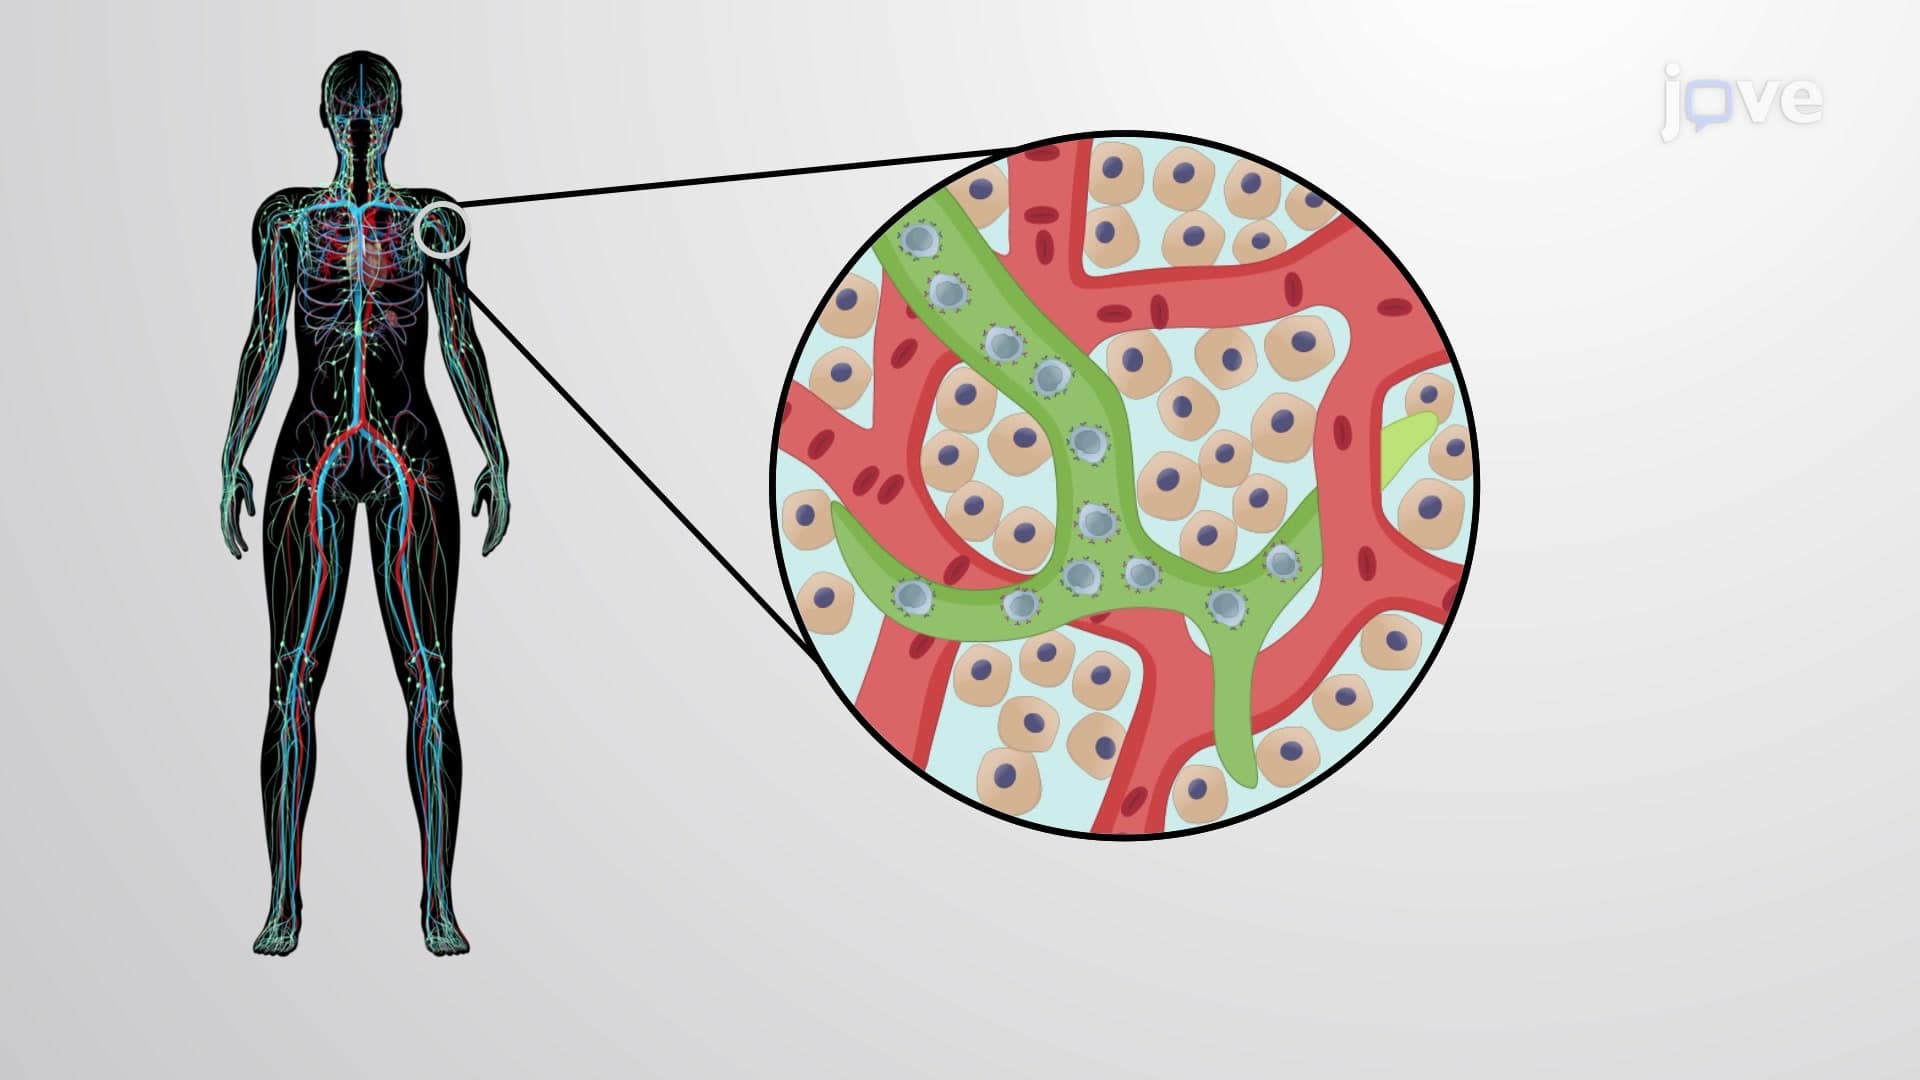
Fluid Connective Tissues: Blood and Lymph
Blood
The blood flows through blood vessels— arteries, capillaries, and veins. Blood plasma is primarily made of proteins, solutes, and water.
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...