Related Experiment Video
Updated: Aug 26, 2026

Differential Effects of Lipid-lowering Drugs in Modulating Morphology of Cholesterol Particles
Published on: November 10, 2017
A clinical comparison of calculated versus direct measurement of low-density lipoprotein cholesterol level
Cameron C Lindsey1, Maqual R Graham, Thomas P Johnston
1Department of Pharmacy Practice, School of Pharmacy, University of Missouri-Kansas City, USA. lindseyca@umkc.edu

Study Objectives:
To determine if, and to what extent, the low-density lipoprotein cholesterol (LDL) level is underestimated when it is calculated by the Friedewald formula compared with the LDL level measured by a direct method. A secondary objective was to determine and compare the percentages of patients meeting LDL goal using each of these two methods.
Design:
Retrospective chart review.
Setting:
Kansas City Veterans Affairs Medical Center.
Subjects:
Patients aged 18 years or older and whose laboratory results reflected a complete lipid profile for 1 year.
Measurement And Main Results:
Calculated LDL level (C-LDL) was derived using the Friedewald formula and was compared with Wako method-derived direct LDL level (D-LDL) to ascertain whether a positive correlation existed. The absolute difference between the methods for each sample was determined and compared overall and for various subgroups. The number of patient samples achieving National Cholesterol Education Program-defined LDL goal was determined and compared for both methods. A total of 20,224 lipid profiles were generated and 19,343 were included in the analysis. A strong correlation was found between D-LDL and C-LDL (r = 0.94). The absolute difference between the two methods demonstrated an underestimation of C-LDL of 19.5 +/- 11.8 mg/dl. The degree of underestimation increased as the triglyceride level increased (p < 0.05). Age within the fifth and sixth decades resulted in significantly higher differences compared with age in the eighth decade or greater (p < 0.05). Female sex and elevated body mass index also resulted in increased discrepancies between the two methods (p < 0.05 for both). Seventy-six percent of the lipid profiles were derived from patients with coronary heart disease (CHD) or a CHD risk equivalent. Approximately one half of these patients met their LDL goal when LDL level was measured versus calculated (p < 0.0001).
Conclusion:
When compared with D-LDL, an underestimation of approximately 20 mg/dl was found with C-LDL, resulting in a loss of LDL goal attainment for half of the patients with CHD or a CHD risk equivalent.

Related Concept Videos
 01:25
Blood Studies for Cardiovascular System III: Serum Lipid Profile
Serum lipids are fats and fatty substances in the blood and are crucial for various bodily functions, including energy storage, cellular structure, and hormone production. Serum lipids consist of cholesterol, triglycerides, and phospholipids.
Cholesterol is a soft, fat-like substance found in all body cells. It is crucial for producing hormones, vitamin D, and substances that aid...
 01:16
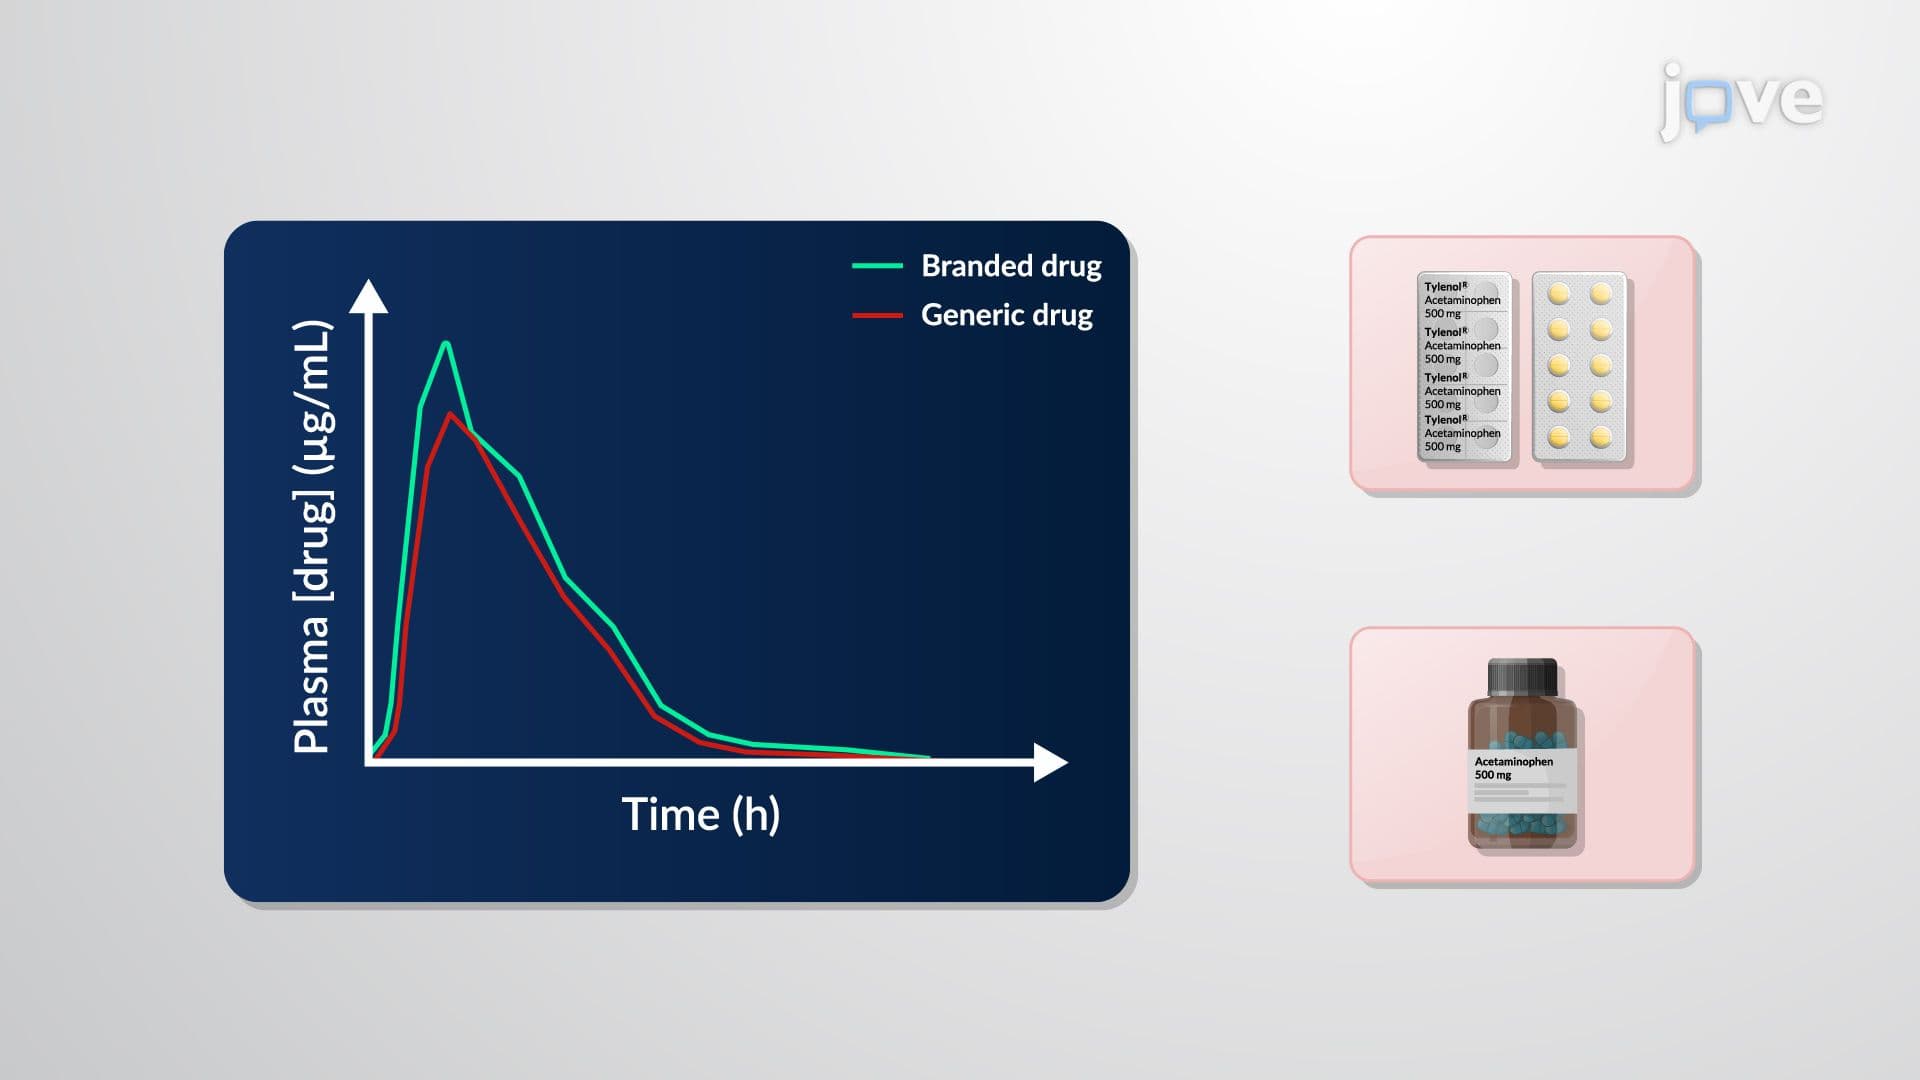
Bioequivalence Data: Statistical Interpretation
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...
 01:29
Cholesterol: Significance and Regulation
Considering cholesterol and...