Related Experiment Video
Updated: Aug 25, 2026
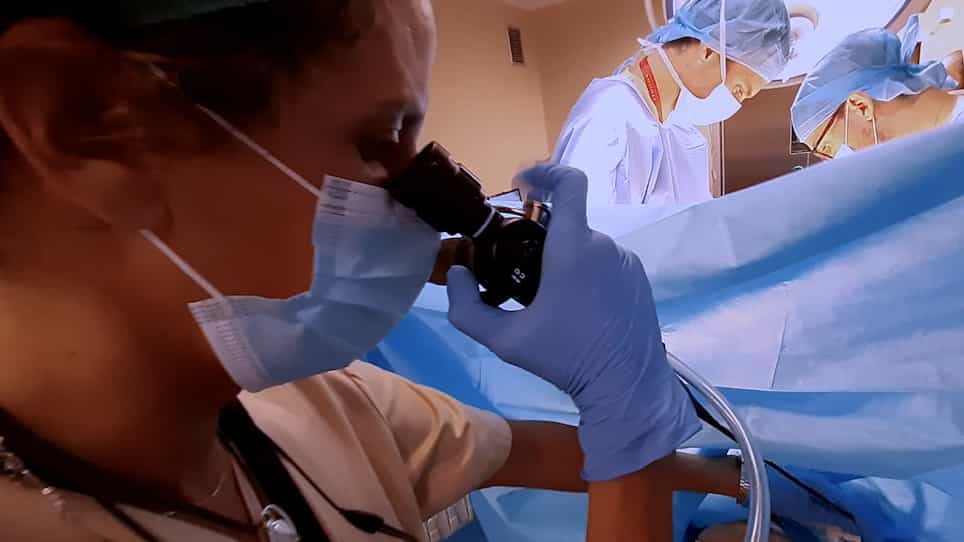
Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
Outcome of lung transplant patients admitted to the medical ICU
Denis Hadjiliadis1, Mark P Steele, Joseph A Govert
1Toronto Lung Transplant Program, Toronto, ON, Canada. Denis.Hadjiliadis@utoronto.ca

Introduction:
Lung transplantation is an acceptable treatment option for end-stage lung disease. Short-term survival has improved, but lung transplant recipients remain at high risk for a variety of complications that can necessitate care in an ICU. Little is known about the epidemiology, clinical outcomes, and risk factors for survival among lung transplant recipients admitted to the ICU.
Methods:
All lung transplant recipients at a single institution discharged from the hospital after their transplant and subsequently admitted to the medical ICU (MICU) between March 1, 1999, and February 28, 2001, were included. Patients were followed until death or February 28, 2002. Demographic data collected included transplant type and date, APACHE (acute physiology and chronic health evaluation) III scores, last preadmission and best posttransplant FEV(1) in liters, admitting diagnosis, use of mechanical ventilation, and previous MICU admission.
Results:
There were 51 patients admitted to the MICU during the study period (73 total admissions). Their demographic data, pretransplant diagnoses, and type of transplant were similar to those of the rest of Duke University Medical Center lung transplant patients. Fifty-three percent (27 of 51 patients) required mechanical ventilation during their first MICU admission. Thirty-seven percent (19 of 51 patients) died during their first MICU admission. Fifty-nine percent (16 of 27 patients) receiving mechanical ventilation died. Patients who died had lower FEV(1) to posttransplant best FEV(1) ratio prior to MICU admission, and also had higher APACHE III scores on MICU admission compared to survivors: FEV(1), 51.3 +/- 21.9% (n = 14) vs 75.5 +/- 20.4% (n = 30) [p = 0.001]; APACHE III score, 77.7 +/- 21.4 (n = 19) vs 60.1 +/- 16.5 (n = 32) [p = 0.002]. Survival rates by Kaplan-Meier analysis at 1 year and 2 years after initial MICU admission were 43.1% and 40.9%, respectively. The longest survivor is currently alive 1,087 days after initial MICU admission.
Conclusion:
Admission to the MICU is common in lung transplant recipients. MICU care, including mechanical ventilation, is associated with a poor prognosis in lung transplant recipients, but is appropriate for selected patients with good allograft function.
Related Concept Videos
 01:16
Kidney Transplant III: Nursing Management
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure