Related Experiment Video
Updated: Aug 25, 2026
Detrusor Underactivity Model in Rats by Conus Medullaris Transection
Published on: August 28, 2020
Mixed incontinence
Charlotte Chaliha1, Vik Khullar
1Department of Urogynaecology, St. Mary's Hospital, Imperial College, London, United Kingdom.

Abstract:
The epidemiology and treatment of mixed incontinence has received relatively little attention. However, mixed incontinence--defined as the combination of stress and urge incontinence--accounts for approximately 33% of all cases of incontinence in women. The condition often responds poorly to treatment, either pharmacologic or surgical. Potential pharmacologic approaches for mixed incontinence include antimuscarinic agents, estrogen replacement therapy (for postmenopausal women), and dopamine, serotonin, or norepinephrine reuptake inhibitors. In a large-scale, multinational, placebo-controlled, clinical trial, the antimuscarinic agent tolterodine significantly reduced incontinence episodes in women with mixed symptoms. The benefits of tolterodine continued to increase during the 8 weeks of the trial and extended to additional end points, including frequency, urgency, and urge incontinence. A limited number of studies have examined the use of estrogen for mixed incontinence and have produced conflicting results. Duloxetine oxalate, a combined serotonin/norepinephrine reuptake inhibitor, has shown great promise in animal studies, as well as in phase 2 and 3 clinical trials. This agent is the first to demonstrate efficacy as a sole therapy for stress incontinence and has exhibited favorable effects on bladder capacity, suggesting possible benefits in mixed incontinence. Only 5 studies (2 of which were conducted during the 1980s) have specifically examined the use of surgery for the treatment of mixed incontinence; the cure rates reported have varied. The current body of information supports use of an antimuscarinic agent as initial therapy for mixed incontinence, although long-term trials are needed to shed more light on the duration of benefit.
Related Concept Videos
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:23
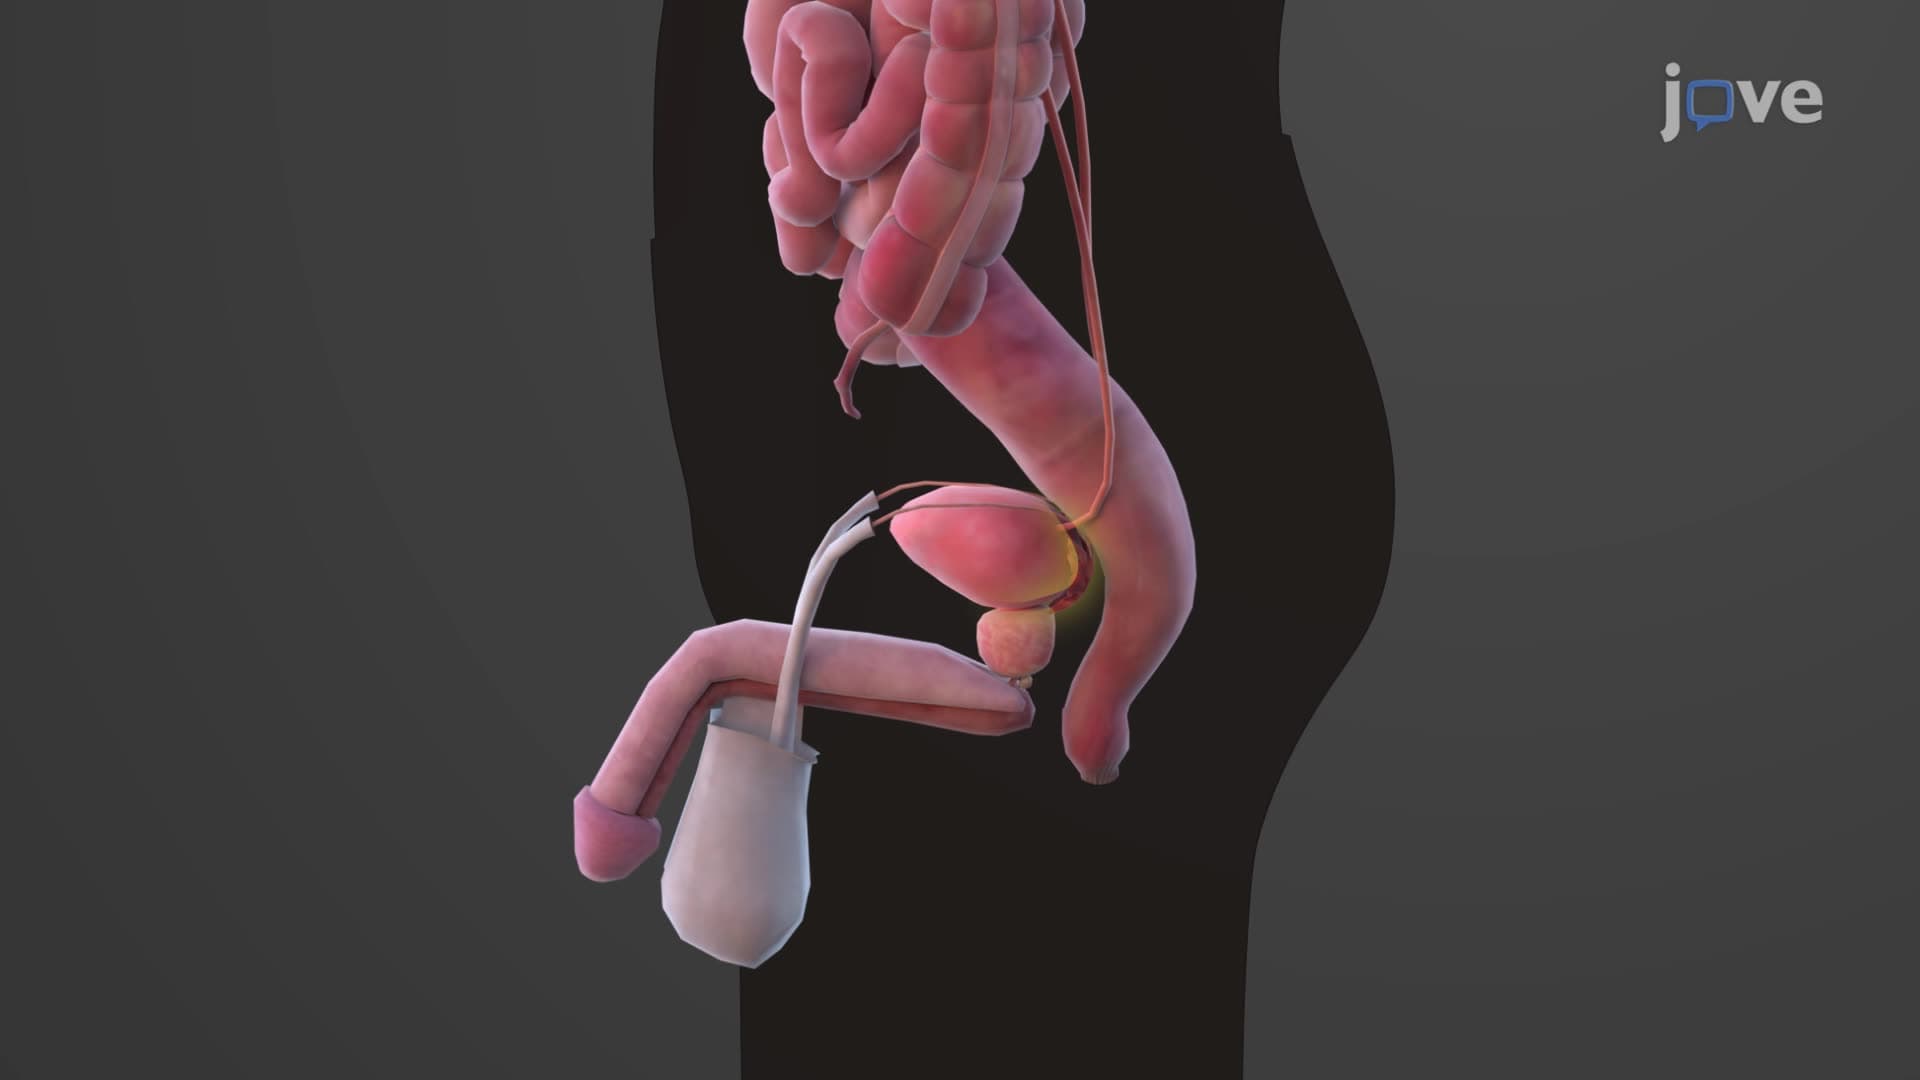
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:19
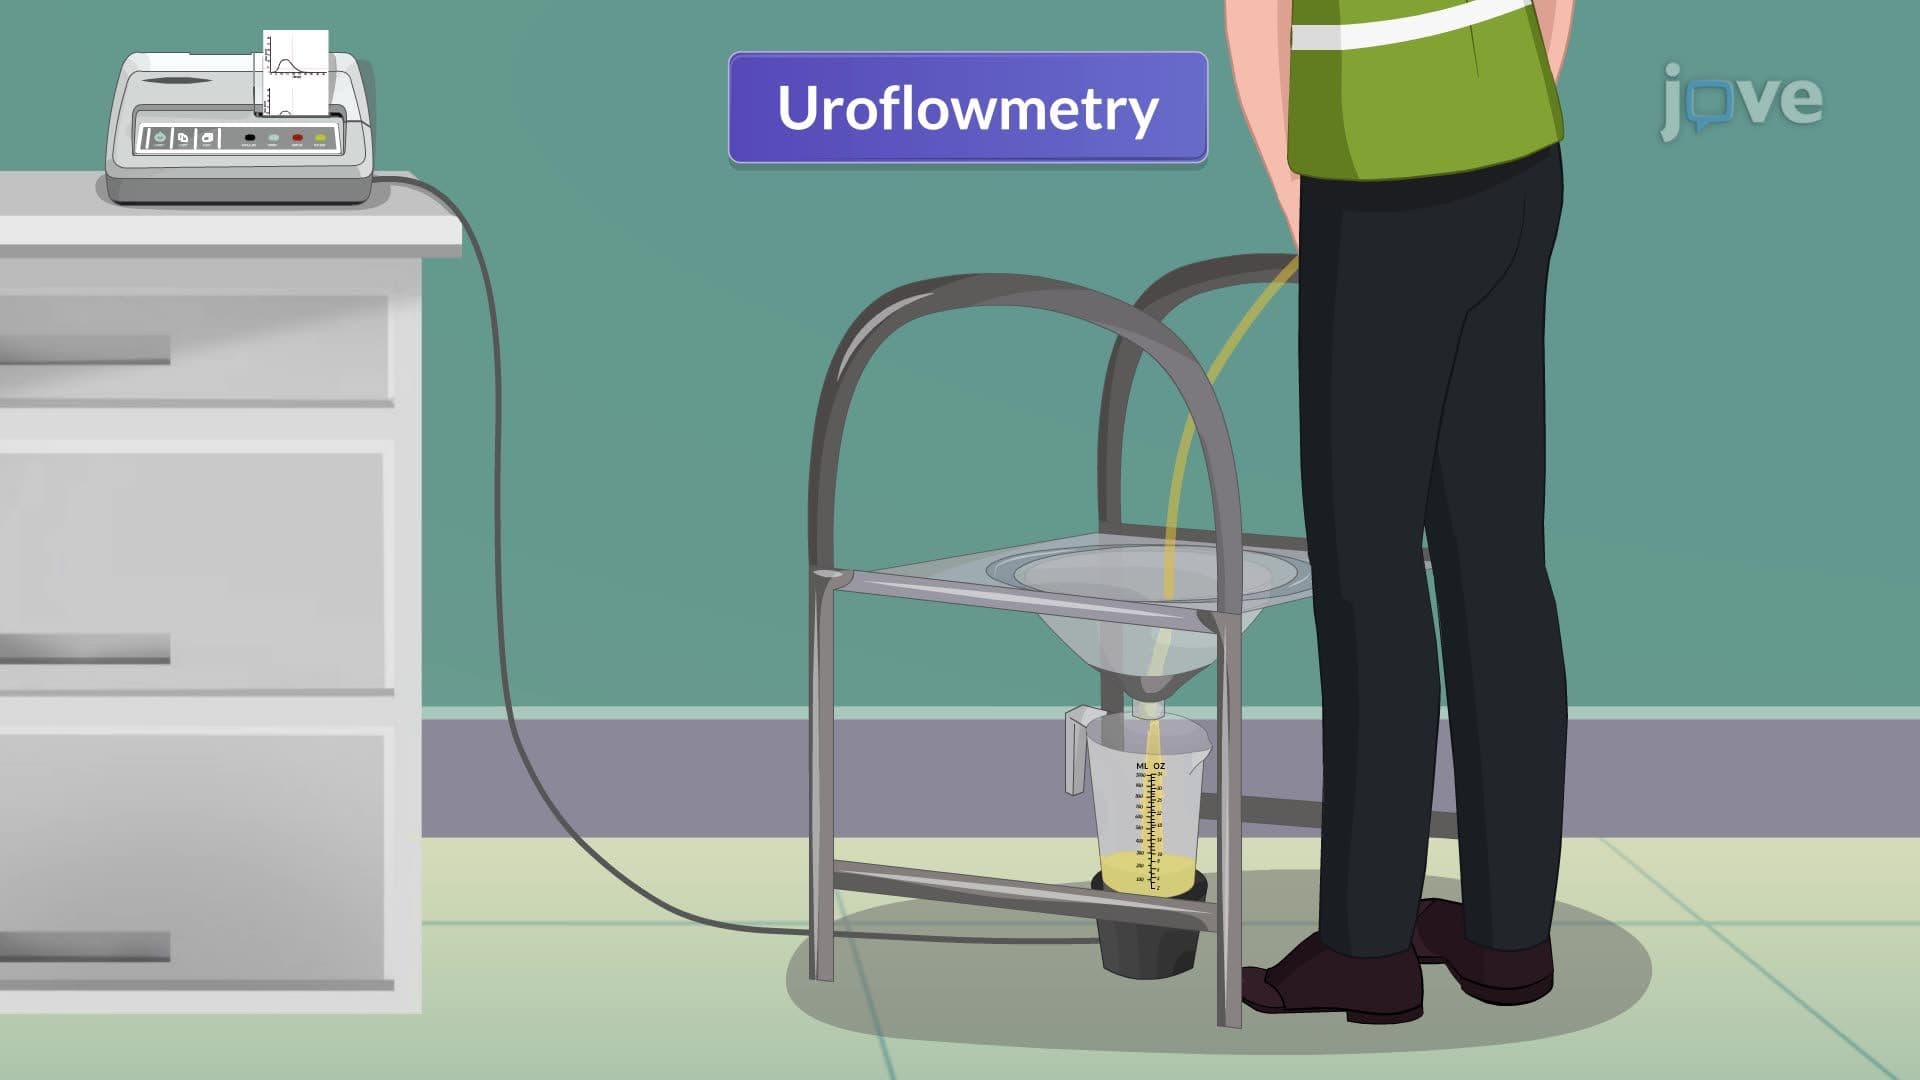
Urodynamic Studies: Uroflowmetry
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:17
Urinary Tract Infection IV: Nursing Management