Related Experiment Video
Updated: Aug 25, 2026
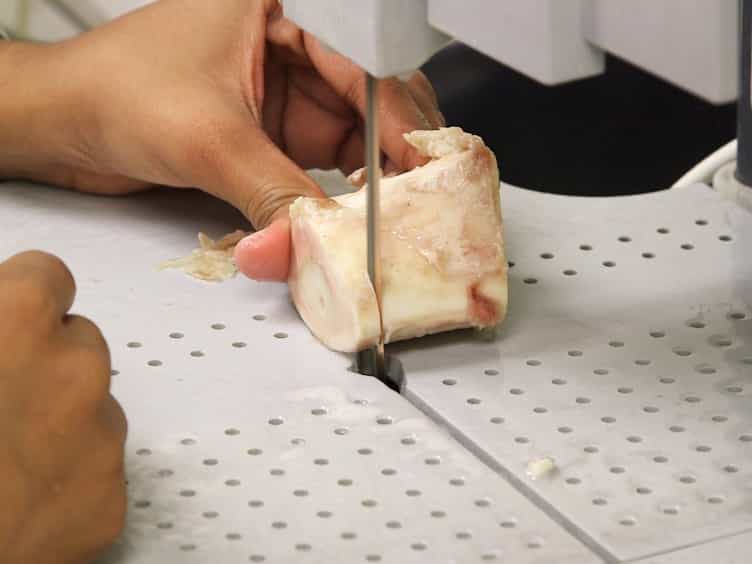

Fragility Assessment of Bovine Cortical Bone Using Scratch Tests
Published on: November 30, 2017
Stratification of bone fracture risk in patients with celiac disease
Mara L Moreno1, Horacio Vazquez, Roberto Mazure
1Small Intestine Section, Department of Medicine, Hospital de Gastroenterologa Dr. Carlos Bonorino Udaondo, Buenos Aires, and School of Medicine, Universidad del Salvador, Buenos Aires, Argentina.

Background And Aims:
Our objective in this cross-sectional, case-control study was to gain insight into celiac osteopathy by examining a well-defined cohort of patients with a wide clinical spectrum of the disease.
Methods:
We studied 148 unselected celiac patients and 296 (1:2) age- and sex-matched controls diagnosed with functional gastrointestinal disorders. Based on the clinical history, 53% were classically symptomatic, 36% had subclinical celiac disease, and 11% were silent, detected by screening. The fracture information was obtained through an in-person interview using a pre-designed questionnaire.
Results:
Classically symptomatic patients had an increased number of fractures in the peripheral skeleton (47%) compared with age- and sex-matched controls (15%; odds ratio, 5.2; 95% confidence interval, 2.8-9.8). However, fractures in subclinical/silent celiac cases (20%) were no different from those in controls (14%; odds ratio, 1.7, 0.7-4.4). Compared with the subclinical/silent group, a significantly greater prevalence of fractures was detected in classically symptomatic patients (odds ratio, 3.6, 1.7-7.5). Compared with controls, celiac disease patients had significantly more fractures produced by mild trauma (P < 0.01), but there were no differences in the severity of trauma events that induced fractures. Mean bone density femoral neck z score was higher for subclinical/silent cases compared with classically symptomatic patients (P < 0.05).
Conclusions:
Celiac patients show a very wide variation in fracture risk, with increased risk in classically symptomatic patients. Diagnostic and therapeutic strategies to prevent bone loss and fracture should be preferentially used in the subgroup of patients with classic clinical disease.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...