Related Experiment Video
Updated: Aug 18, 2026


Ultrasound-guided Transthoracic Intramyocardial Injection in Mice
Published on: August 5, 2014
Intravenous versus intramuscular atropine in ECT
B A Kramer1, A Afrasiabi, V E Pollock
1Department of Psychiatry, University of Southern California School of Medicine, Los Angeles.

Twelve patients receiving ECT consented to random assignment to either intravenous or intramuscular administration of atropine for a total of 48 ECTs. There were no statistically significant differences between routes of administration in heart rate, blood pressures, or sialorrhea, but intravenous administration eliminated one injection per treatment and the development of dry mouth and tachycardia between the intramuscular injection and ECT. The authors recommend that atropine for ECT be administered intravenously.
Twelve patients receiving ECT consented to random assignment to either intravenous or intramuscular administration of atropine for a total of 48 ECTs. There were no statistically significant differences between routes of administration in heart rate, blood pressures, or sialorrhea, but intravenous administration eliminated one injection per treatment and the development of dry mouth and tachycardia between the intramuscular injection and ECT. The authors recommend that atropine for ECT be administered intravenously.

Related Concept Videos
 01:30
Indirect-Acting Cholinergic Agonists: Pharmacological Actions
At the neuromuscular junction, these agents work by inhibiting the breakdown of acetylcholine, allowing it to remain bound to the receptor and bind to nearby receptors. This process leads to repetitive firing of the endplate, causing muscle...
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:29
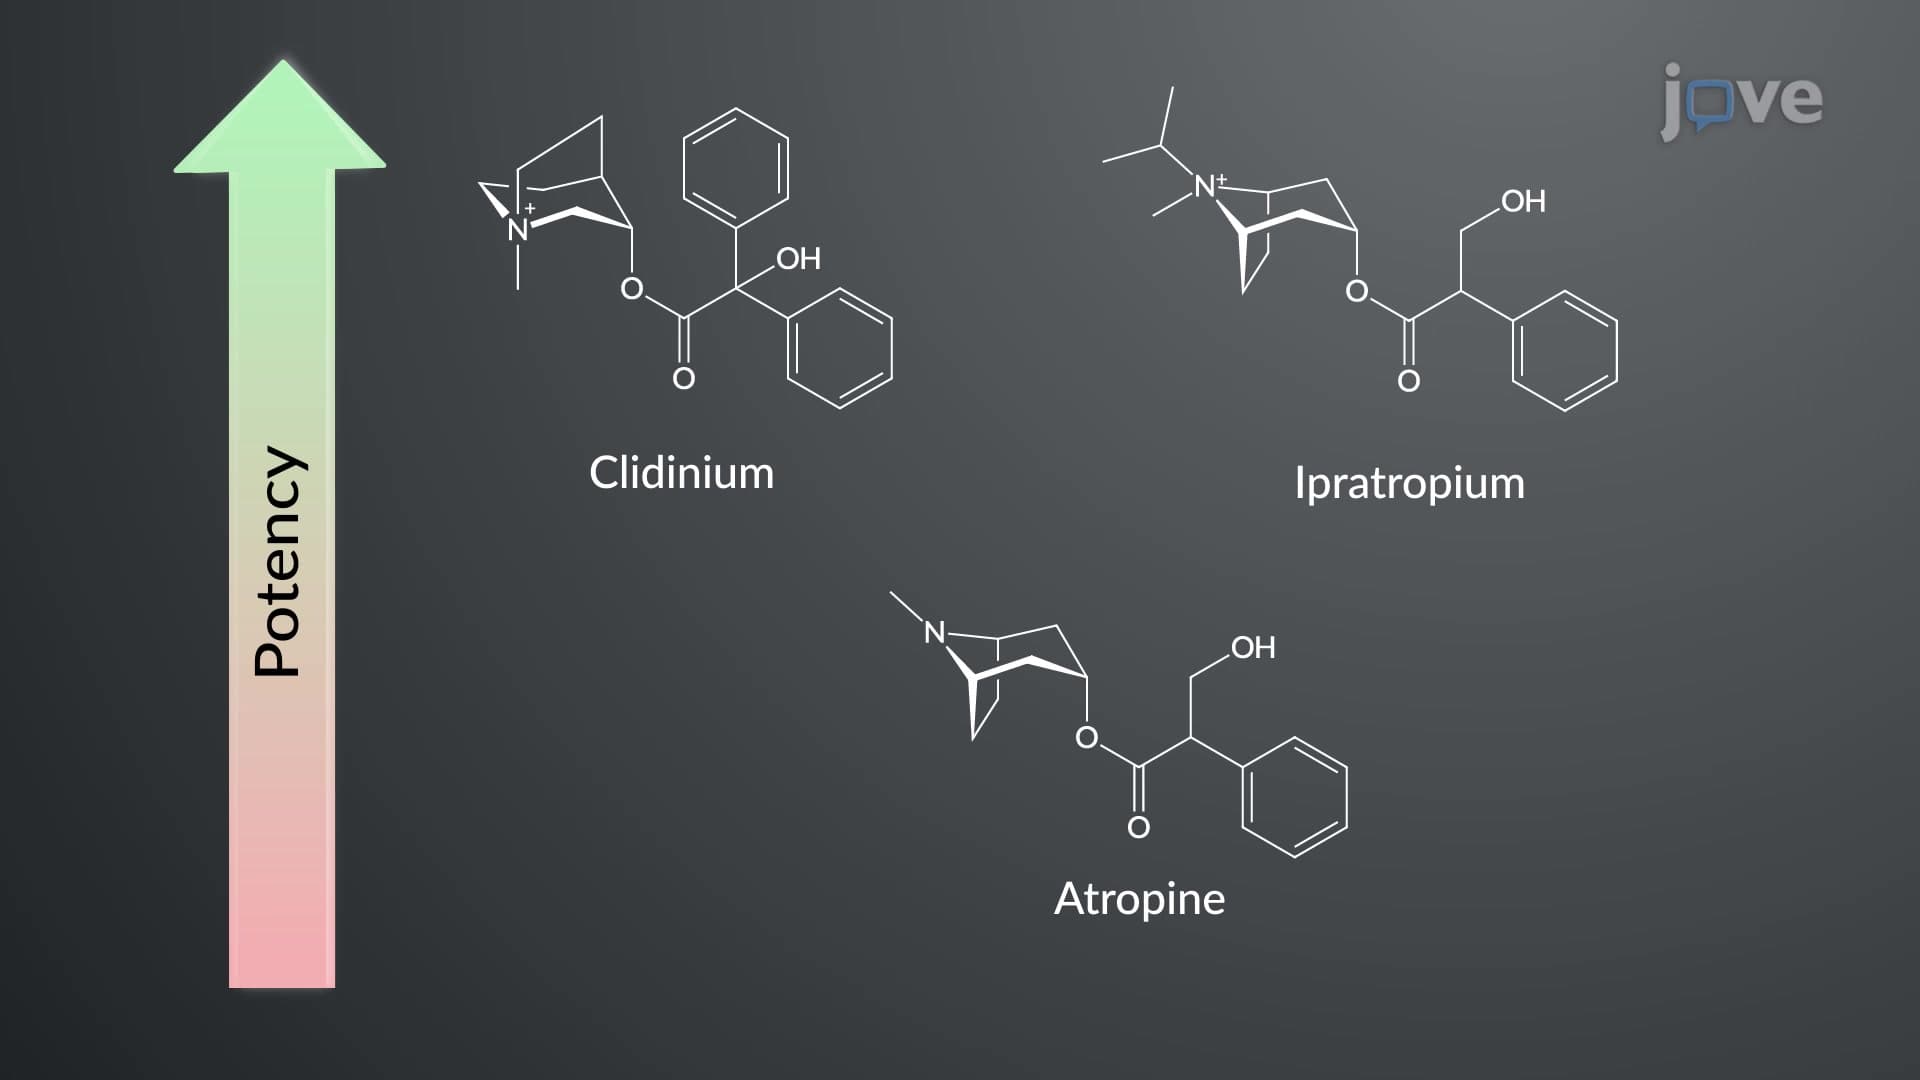
Cholinergic Antagonists: Chemistry and Structure-Activity Relationship
 01:24
Cholinergic Antagonists: Pharmacokinetics
 01:11
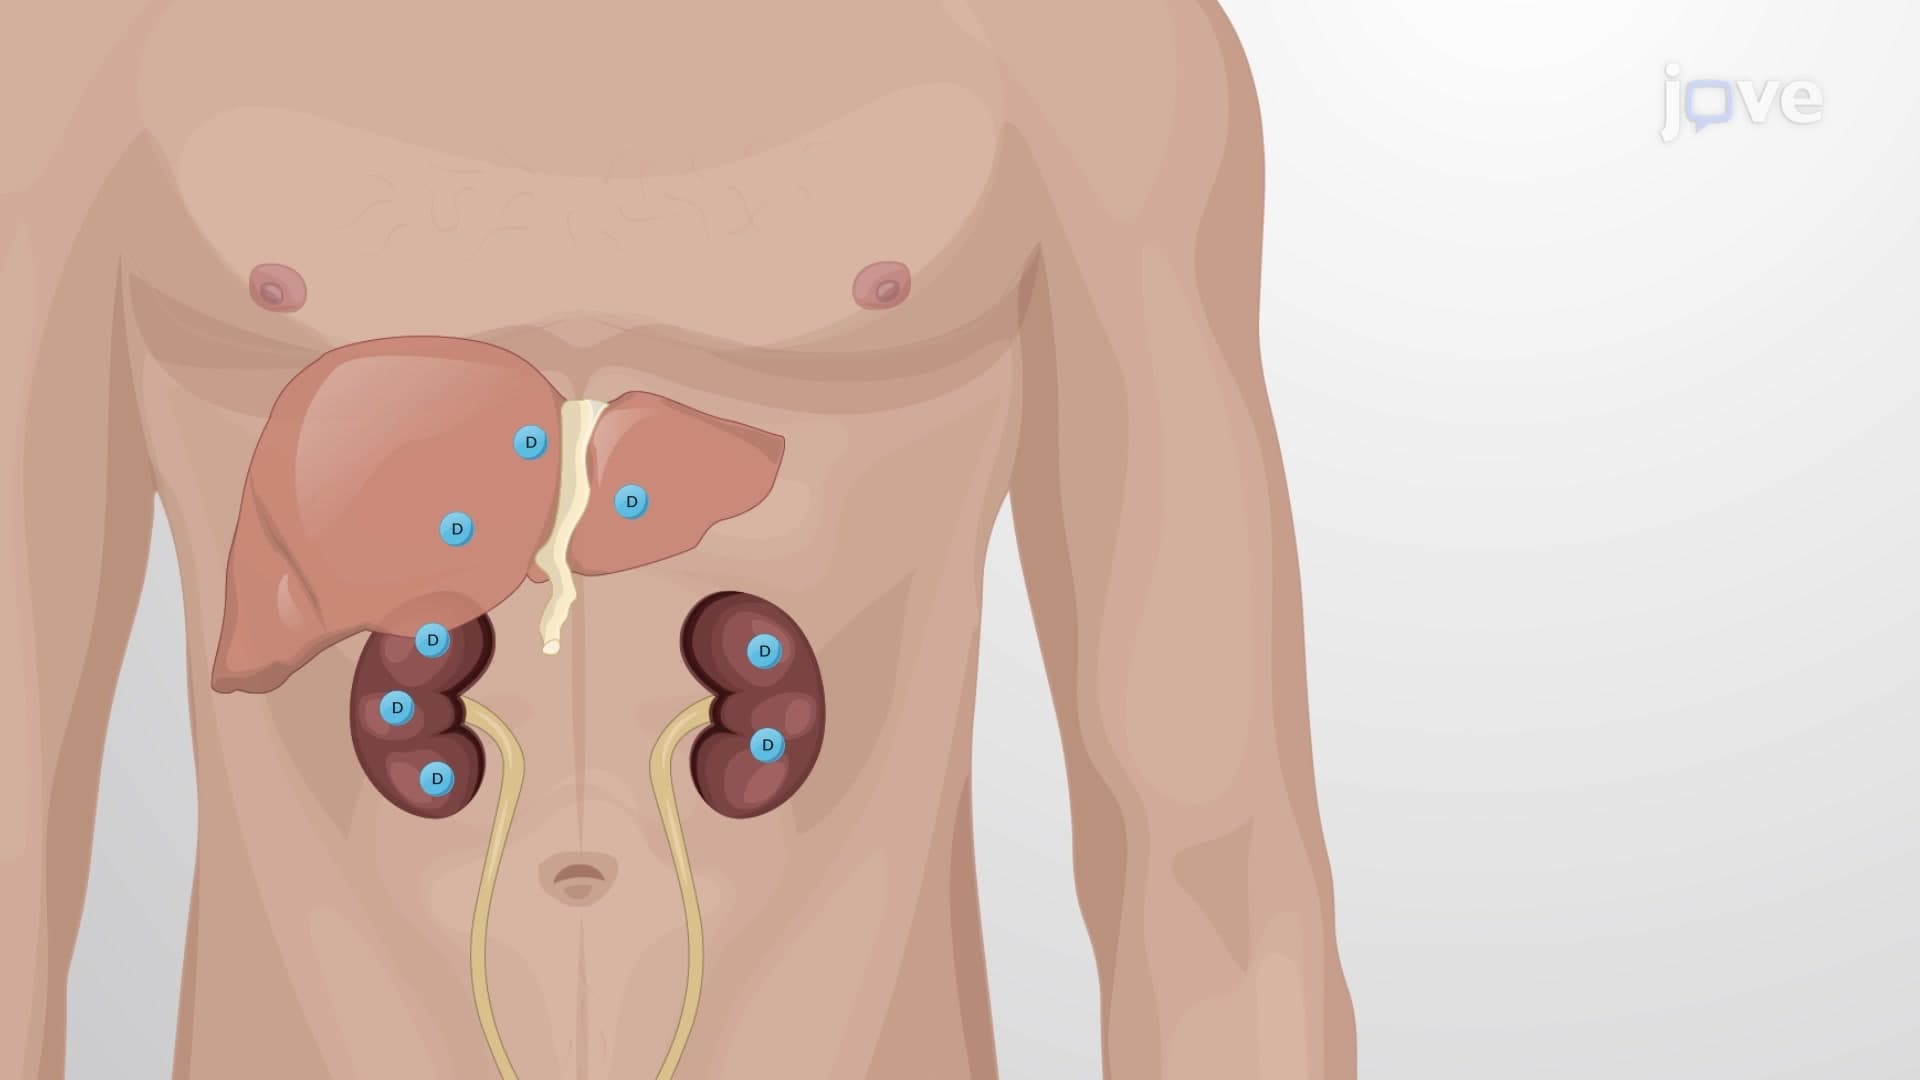
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:19
Depolarizing Blockers: Pharmocokinetics