Related Experiment Video
Updated: Aug 15, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Cyclosporine renal dysfunction
1Transplant Center, Department of Nephrology, Institute for Clinical and Experimental Medicine, Prague, Czech Republic. stefan.vitko@medicon.cz

Abstract:
Cyclosporine (CsA), introduced as an immunosuppressive agent in the 1980s, quickly become the first-line treatment in organ transplantation. However, these improvements were associated with an increased incidence of renal dysfunction. CsA causes histopathological changes in renal transplants that are often difficult to distinguish from other processes, especially chronic allograft nephropathy. Enhanced angiotensin II, transforming growth factor-beta, and vascular endothelial growth factor expression together with down-regulation of nitric oxide synthesis may play roles in chronic CsA nephropathy. Efforts have recently focused upon protocols that minimize the risk of CsA nephrotoxicity while preserving low rates of acute rejection. Four types of CsA-sparing studies have emerged from recent clinical experience: (1) conversion studies in which a nonnephrotoxic drug is substituted to allow CsA reduction, (2) minimal CsA exposure studies in which reduced CsA doses are combined with nonnephrotoxic drugs, (3) withdrawal studies in which CsA is completely discontinued at some time after transplantation, and (4) CsA-free studies in which the drug is completely avoided from the time of transplantation. Monitoring of CsA immunosuppression according to C2 blood levels, which better correlate with the area under the time-concentration curve than trough concentrations, should reduce the risk for toxicity; however, the most appropriate target range has not yet been clearly established. Because of interindividual differences in CsA absorption and susceptibility to renal dysfunction, the current therapeutic drug monitoring should be supplemented with pharmacogenetic information on genetic variability of relevant genes for pharmacokinetic parameters and therapeutic targets. This approach may guide choices for immunosuppressants for particular patients, with low toxicity. Thus, despite of 20 years of its history, CsA renal dysfunction remains an important clinical challenge.

Related Concept Videos
 01:15
Renal Drug Excretion: Overview
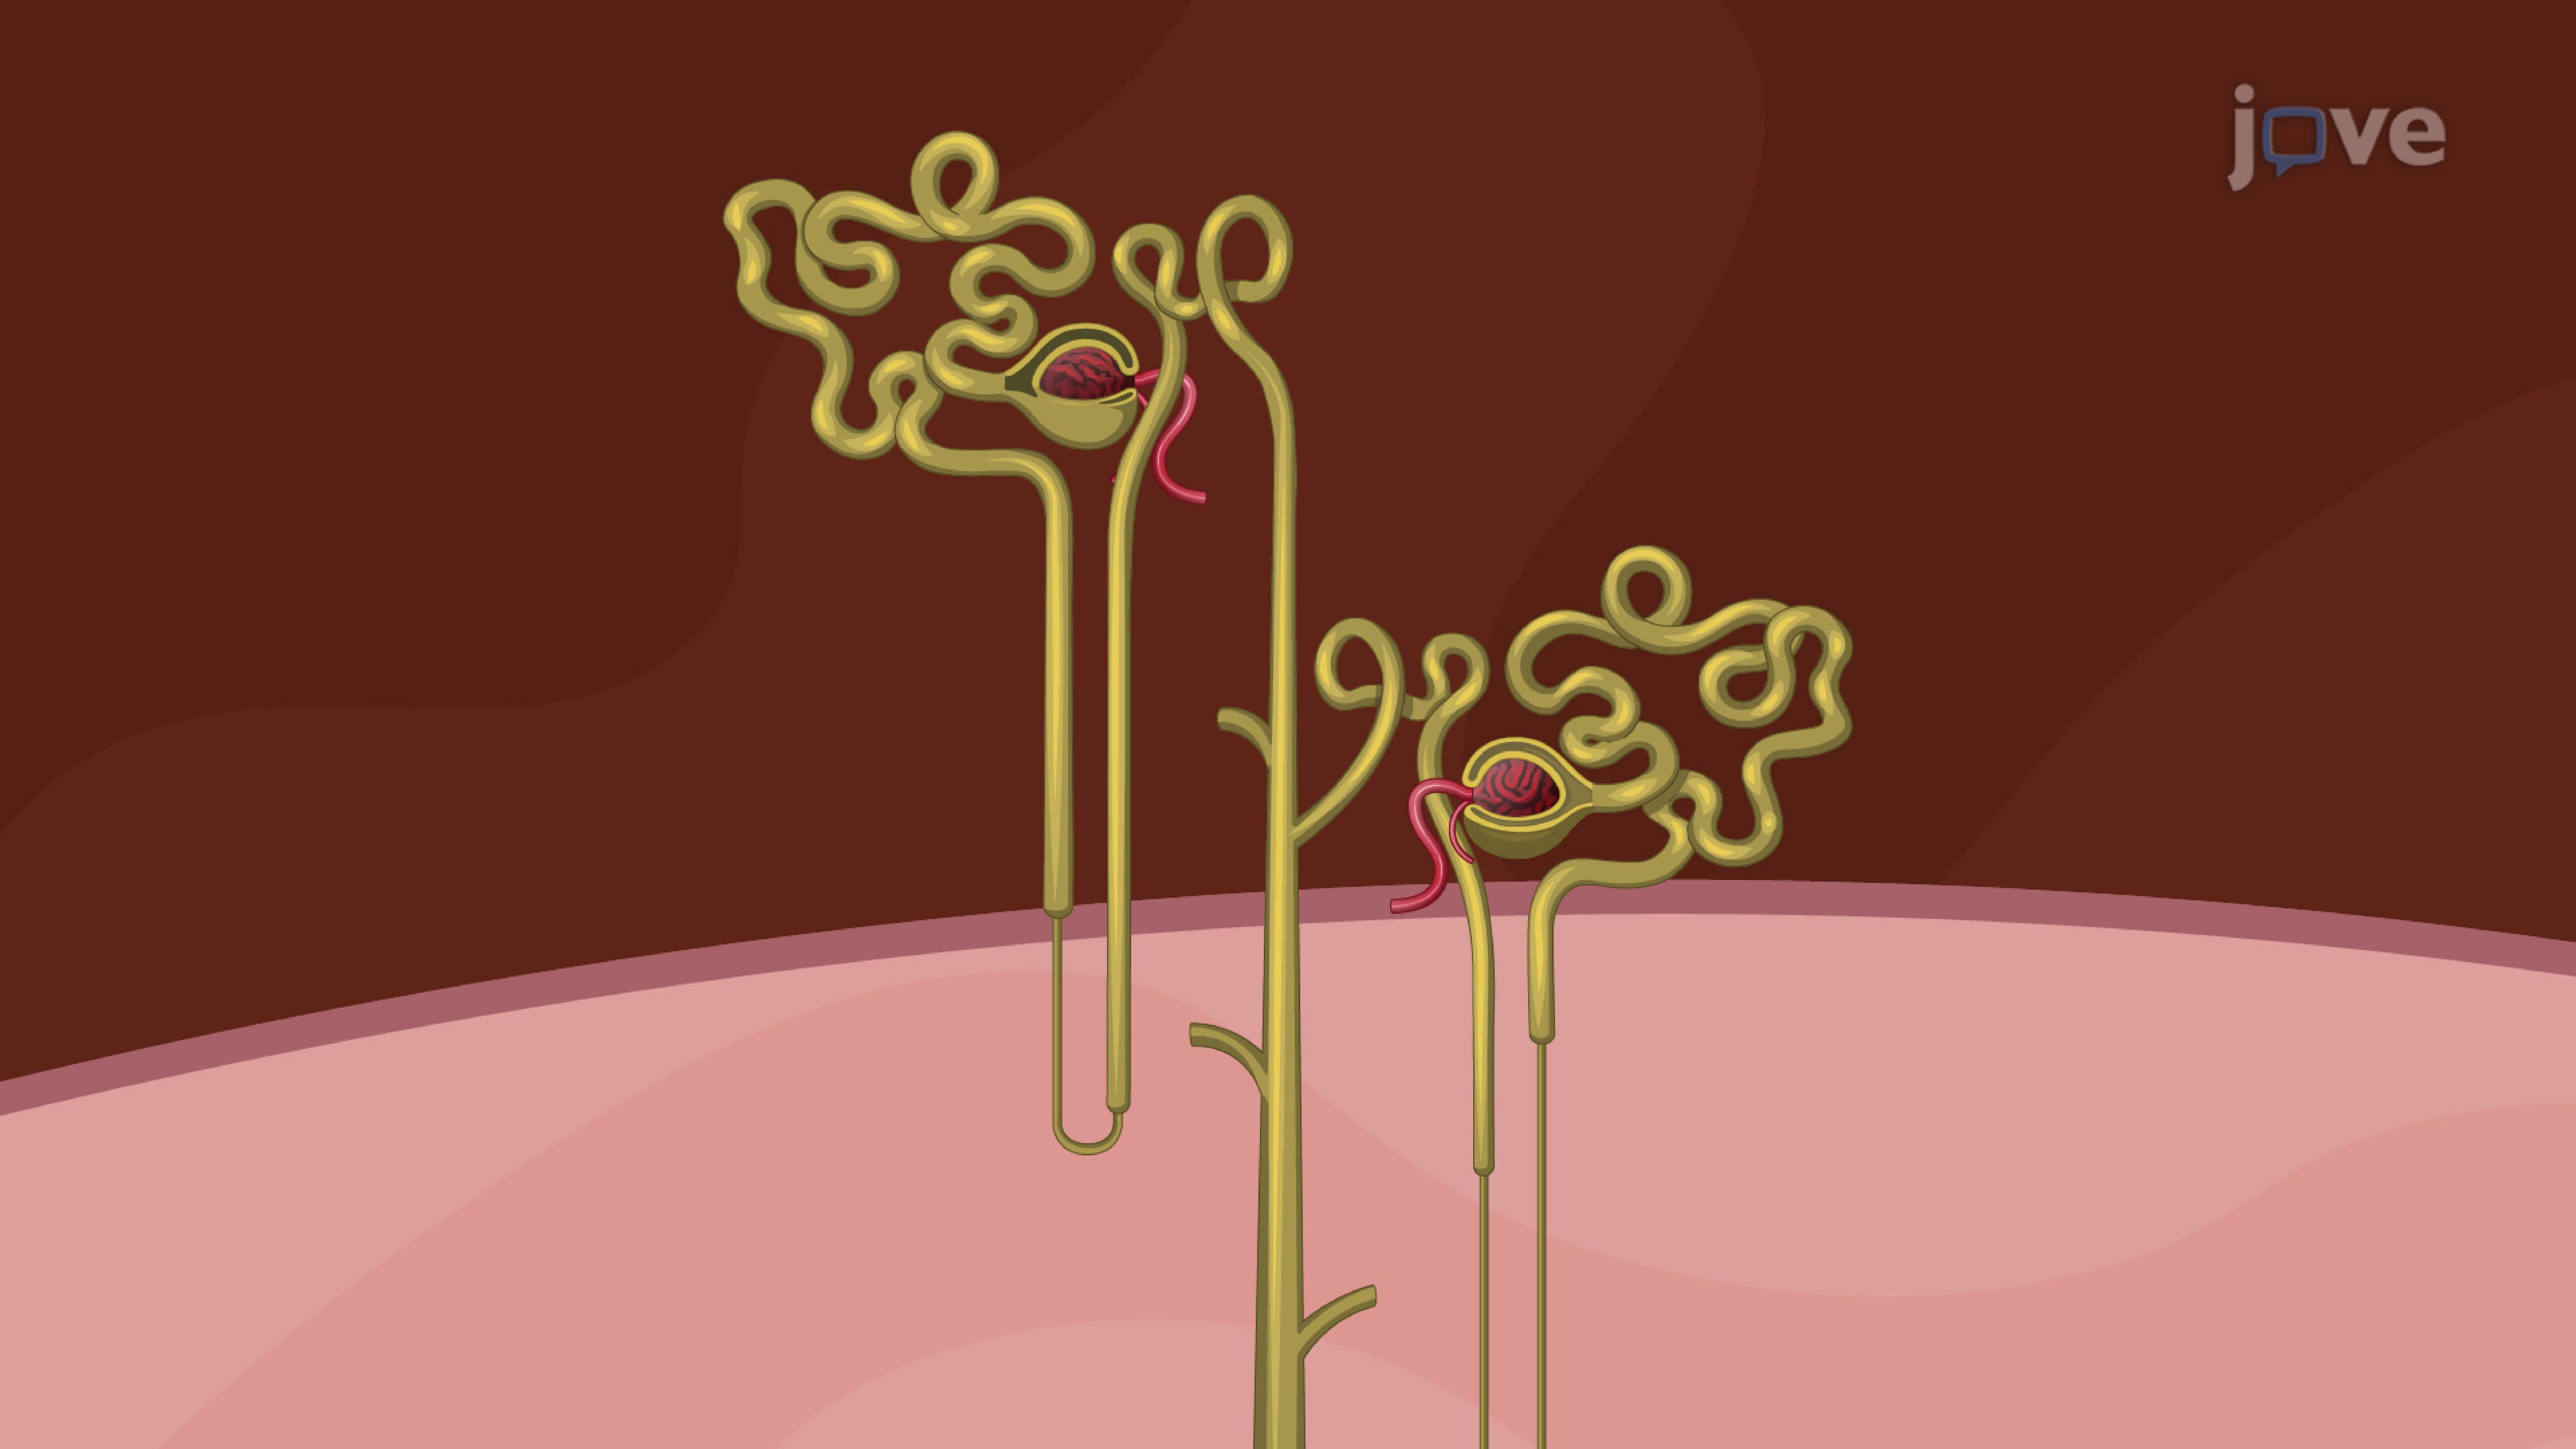
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:02
Renal Drug Excretion: Glomerular Filtration
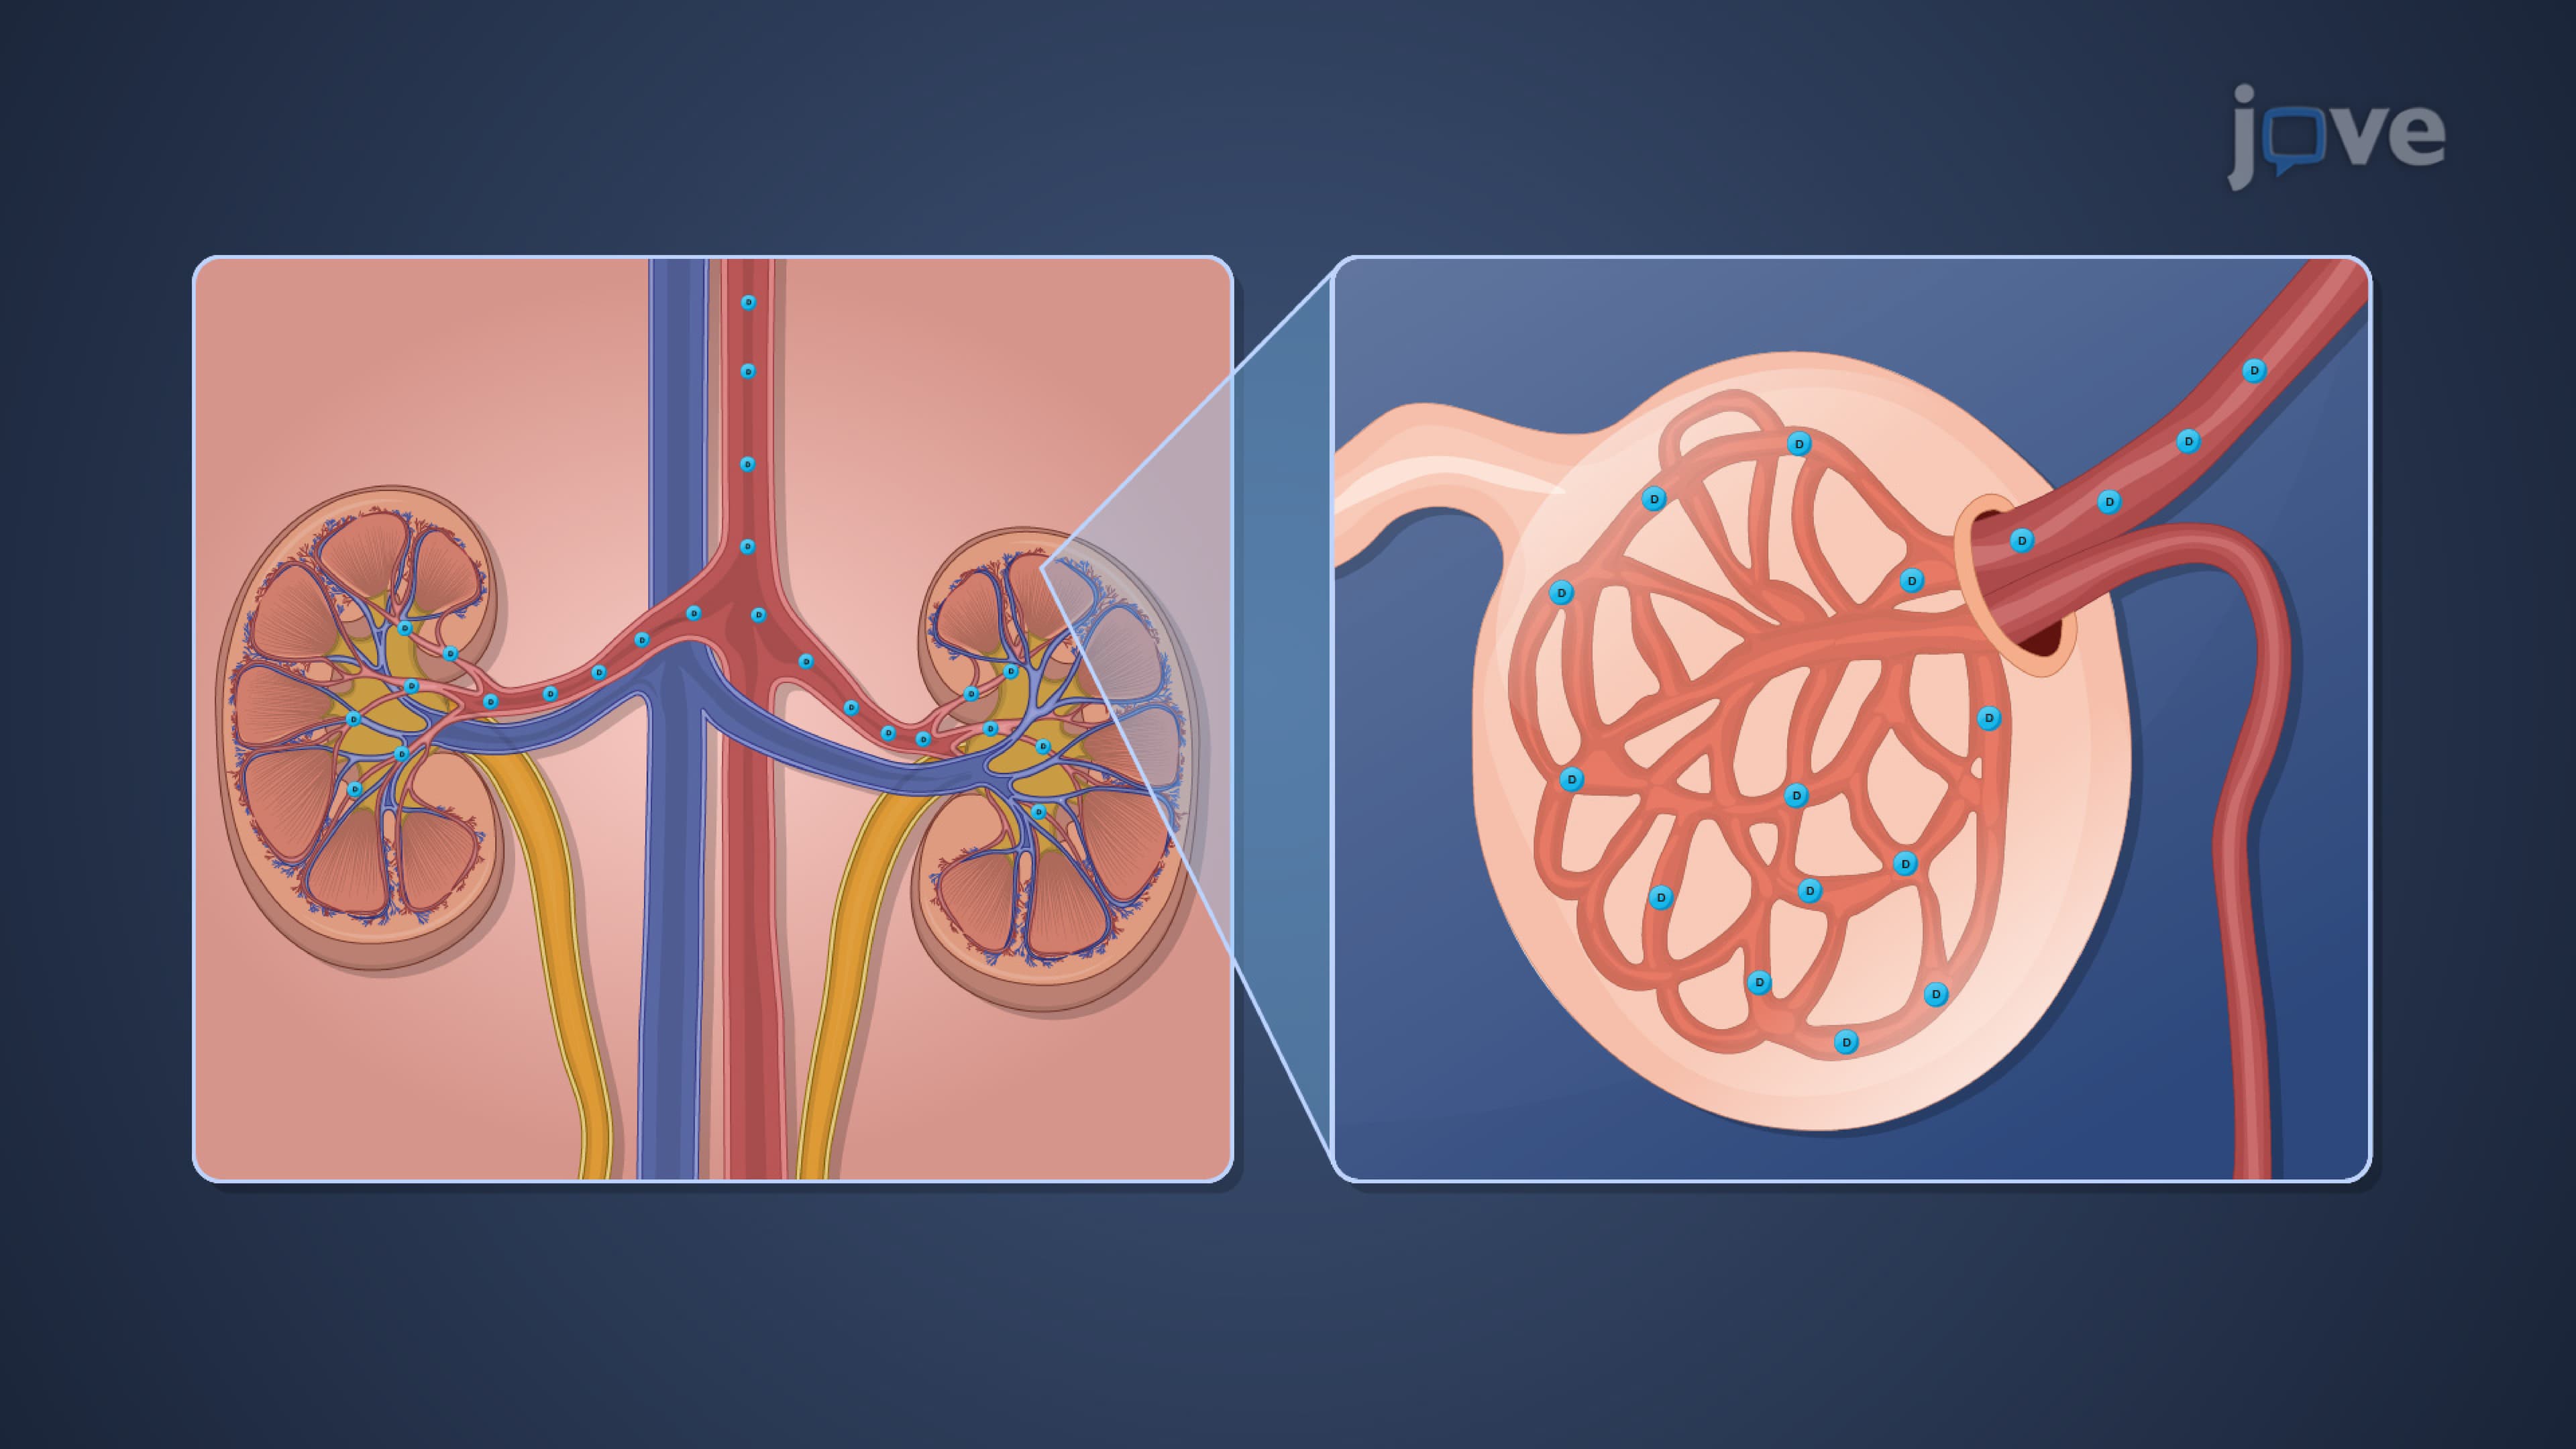
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles.
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:06
Renal Drug Clearance: Overview
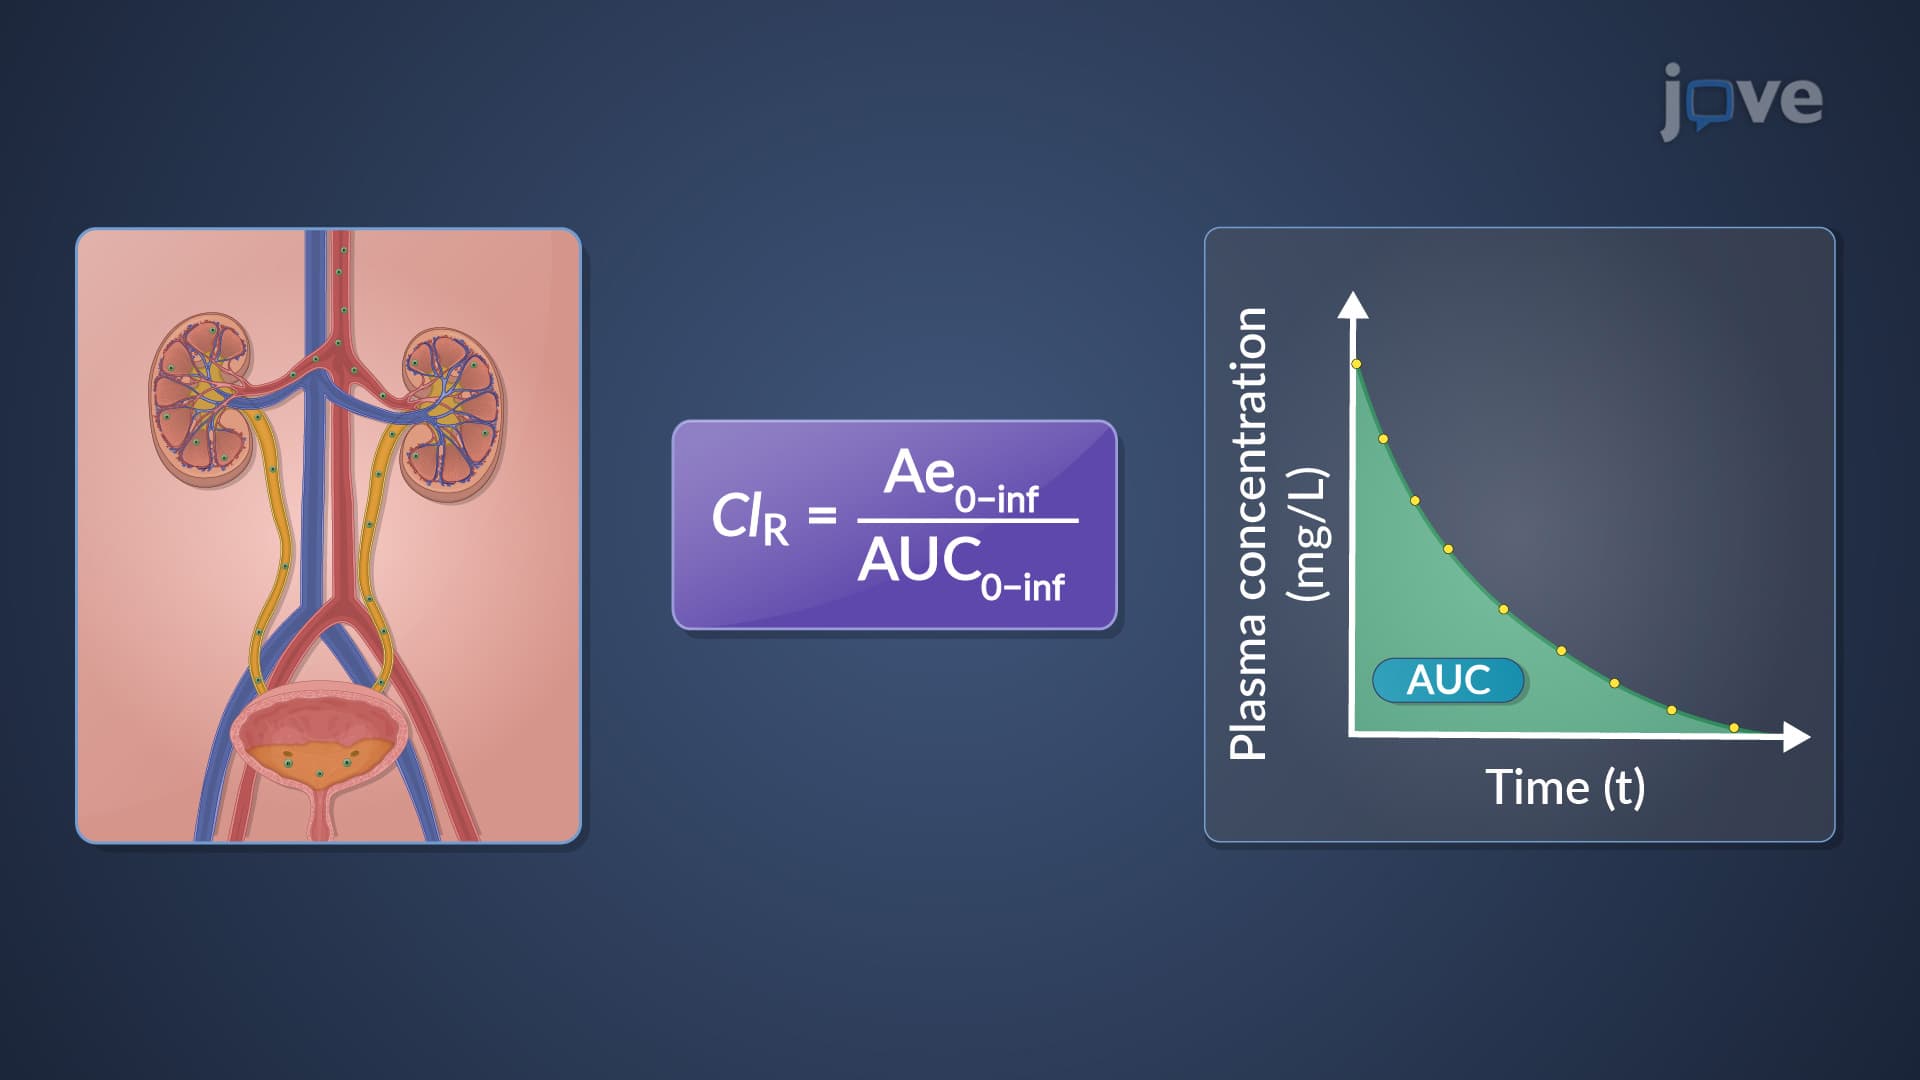
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...