Laparoscopy alone is superior to peritoneal cytology in staging gastric and esophageal carcinoma
Related Experiment Video
Updated: Jul 14, 2026
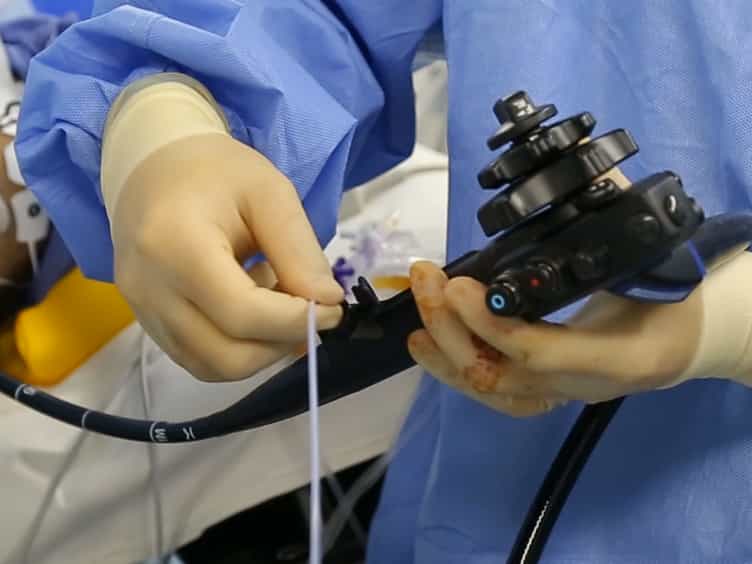
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
M B Wilkiemeyer1, S C Bieligk, R Ashfaq
1Department of Surgery, University of Texas Southwestern, Dallas, TX 75390, USA.

Background:
Laparoscopy identifies metastatic disease in patients with upper gastrointestinal malignancies; however, it has been suggested that cytological examination of peritoneal washings may increase the diagnostic yield. We hypothesize that the addition of cytologic washings to a standardized staging laparoscopy is unnecessary for the identification of intraabdominal metastasis in patients with gastric/esophageal cancer.
Methods:
Forty patients with gastric/esophageal cancer were prospectively evaluated. Patients successfully underwent a diagnostic laparoscopy protocol (with biopsies) during which peritoneal washings were obtained and processed for cytologic analysis. Laparoscopic versus cytologic identification of intraabdominal metastasis were compared.
Results:
Forty patients successfully completed laparoscopy with collection of peritoneal washings. Laparoscopic examination of the peritoneal cavity upstaged 21 (52.5%) patients. Laparoscopic examination consistently identified a statistically significant higher number of positive patients than cytologic examination of peritoneal washings (p = 0.001) and examination of cytologic washings alone failed to identify 45% of patients with positive findings and laparoscopy. The addition of cytologic examination added no additional stage IV patients to the laparoscopy-negative group.
Conclusion:
A standardized laparoscopic examination alone is sufficient for the identification of intraabdominal metastatic disease in patients with gastric and esophageal cancer.