Related Experiment Video
Updated: Aug 25, 2026


In Vivo Imaging of Liver Spheroids Engrafted in the Anterior Chamber of the Mouse Eye
Published on: March 29, 2024
Liver
Víctor M Piñeiro-Carrero1, Eric O Piñeiro
1Alfred I. duPont Hospital for Children, Wilmington, Delaware 19899, USA. vpineiro@nemours.org

Abstract:
The liver's unique metabolism and relationship to the gastrointestinal tract make it an important target of the toxicity of drugs and xenobiotics. The developmental changes that occur in the liver's metabolic activity from birth to adolescence contribute to the varied sensitivity to toxins seen in the pediatric population. Hepatic drug metabolism, often with an imbalance between the generation of toxic metabolites and detoxification processes, can influence the degree of hepatotoxicity. The decreased capacity of the neonatal liver to metabolize, detoxify, and excrete xenobiotics explains the prolonged action of drugs such as phenobarbital, theophyline, and phenytoin. The reduced capacity of glucuronide conjugation in the neonate not only predisposes them to physiologic jaundice but also is probably responsible for the chloramphenicol-induced gray infant syndrome. Age-related sensitivity to drugs is attributable in part to differences in metabolic activity. For example, young children are more resistant to acetaminophen hepatotoxicity when compared with adults, whereas children are more susceptible to valproic acid-induced toxicity. The resistance to acetaminophen toxicity is attributable to biochemical differences in young children. In children, sulfation predominates over glucuronidation, leading to decreased formation of toxic intermediates. In addition, infants have a greater capacity to synthesize glutathione, thereby inactivating toxic metabolites of acetaminophen more effectively. Hepatic toxicity as a result of drugs and environmental toxins presents a wide spectrum of clinical disease. Hepatitis is the most common presentation, but every major type of liver pathology can occur. Most drug reactions are attributable to idiosyncratic hepatotoxins; therefore, liver injury occurs rarely. The diagnosis of toxin-induced liver disease requires a high index of suspicion and often entails the exclusion of other causes of liver disease in children. Drug or environmental xenobiotic-induced hepatotoxicity should be considered in the setting of identified exposure or when other causes of childhood liver disease are excluded. Children who take medications that are known to be hepatotoxic, such as anticonvulsants and antineoplastic drugs, need frequent monitoring for evidence of hepatic toxicity. The treatment is often nonspecific; the most important intervention is the prompt discontinuation of the drug or removal of the environmental toxin. A specific antidote is available only for acetaminophen intoxication. In cases of severe toxicity, the patient may develop liver failure. Liver transplantation may be necessary for patients whose liver failure does not resolve.
Insights
Pediatric liver toxicity from drugs and environmental toxins varies with age due to developmental changes in metabolism. Understanding these differences is key to diagnosing and managing hepatotoxicity in children.
Area of Science:
- Hepatology
- Pediatric Toxicology
- Pharmacology
Background:
- The liver is a primary target for drug and xenobiotic toxicity due to its metabolic functions.
- Pediatric populations exhibit varied sensitivity to toxins, influenced by developmental changes in liver metabolism from birth to adolescence.
Purpose of the Study:
- To explore the impact of developmental changes in hepatic metabolism on pediatric drug toxicity.
- To elucidate age-related differences in susceptibility and resistance to specific hepatotoxins in children.
Main Methods:
- Review of existing literature on pediatric hepatotoxicity, drug metabolism, and xenobiotic interactions.
- Analysis of age-specific metabolic pathways, including glucuronidation, sulfation, and glutathione synthesis.
Main Results:
- Neonatal livers have reduced capacity for xenobiotic metabolism and excretion, leading to prolonged drug action and increased risk of syndromes like gray infant syndrome.
- Children show differential susceptibility: resistance to acetaminophen hepatotoxicity (due to sulfation predominance and higher glutathione synthesis) versus increased susceptibility to valproic acid toxicity.
- Drug-induced liver injury (hepatotoxicity) can manifest as various liver pathologies, with hepatitis being most common, often requiring exclusion of other causes for diagnosis.
Conclusions:
- Age-related metabolic differences significantly influence pediatric drug and xenobiotic toxicity.
- Prompt identification of exposure and discontinuation of the offending agent are crucial for managing drug-induced liver injury in children.
- Liver transplantation may be required in cases of severe, unresolved liver failure due to toxicity.


Related Concept Videos
 01:17
Gross Anatomy of the Liver
Located under the diaphragm, the liver is almost entirely ensconced within the rib cage, providing it with substantial protection. Except for the superior most bare area, the liver's surface is covered...
 01:27
Liver Histology
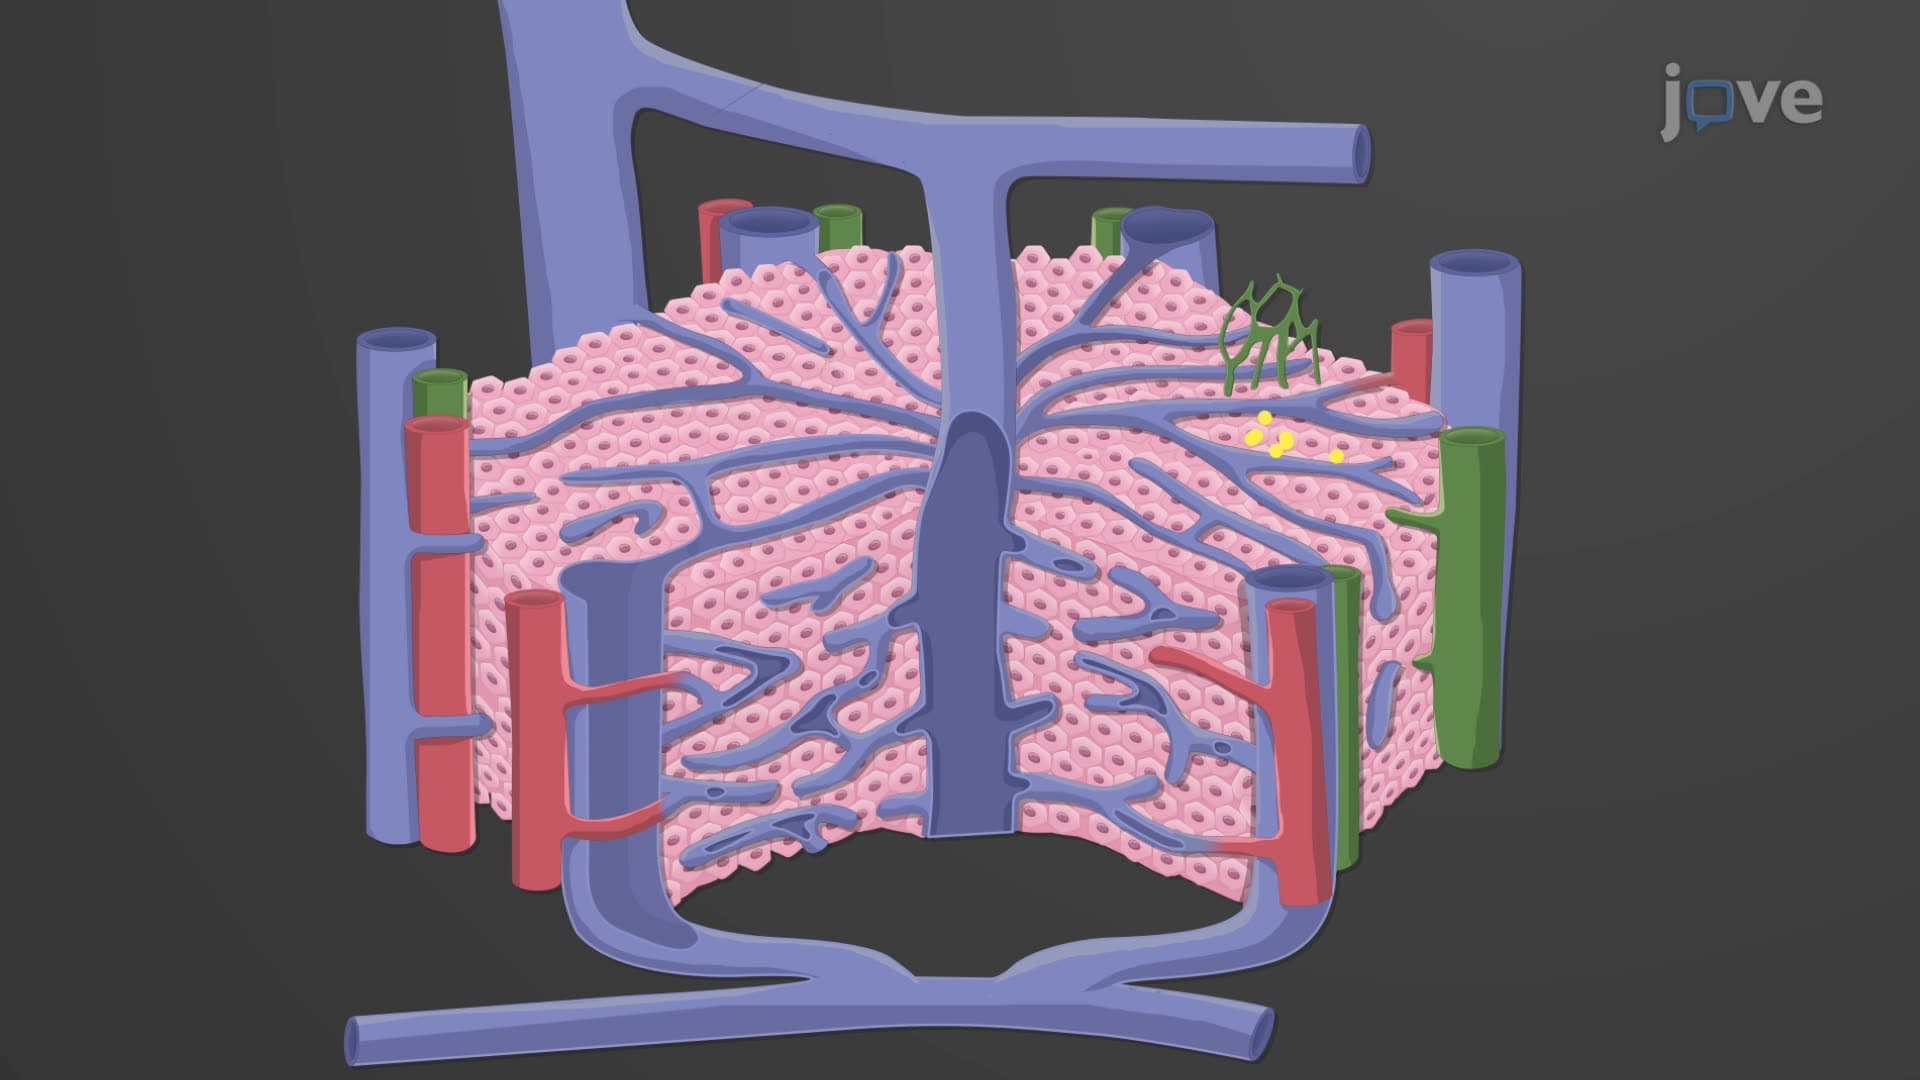
Hepatocytes perform a variety of essential functions. They secrete...
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can also...
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are large...
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is responsible...