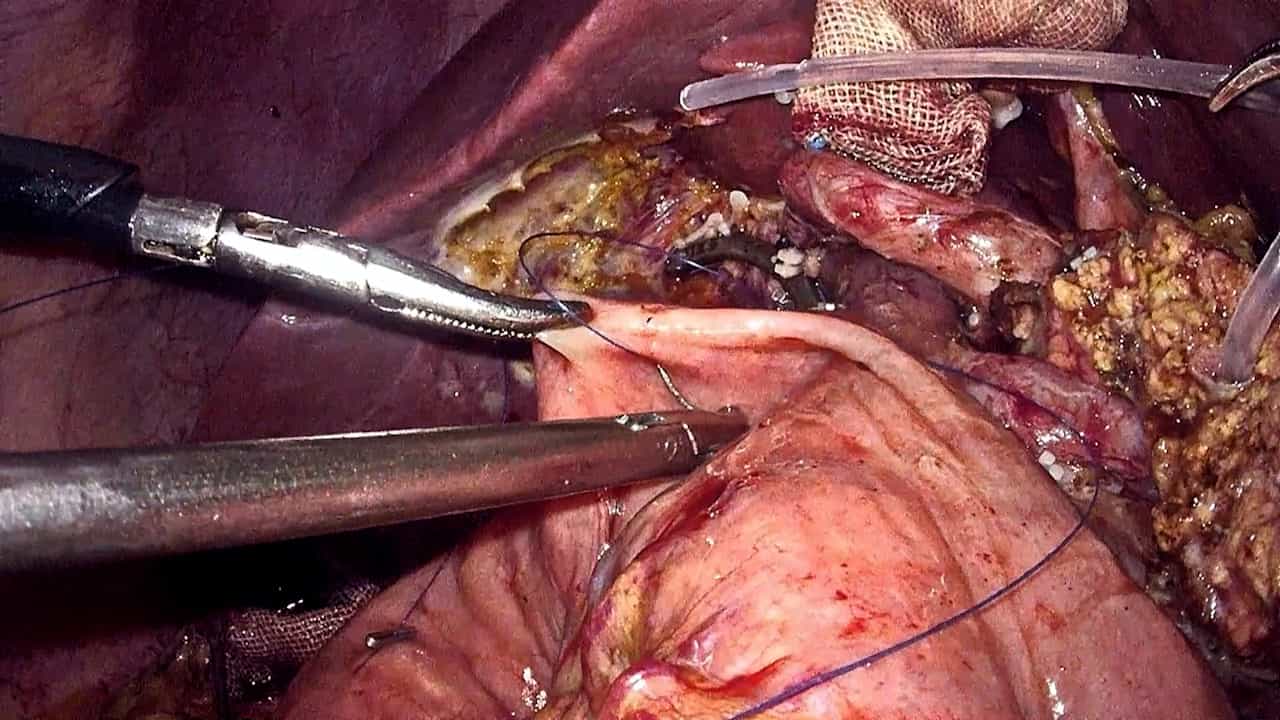

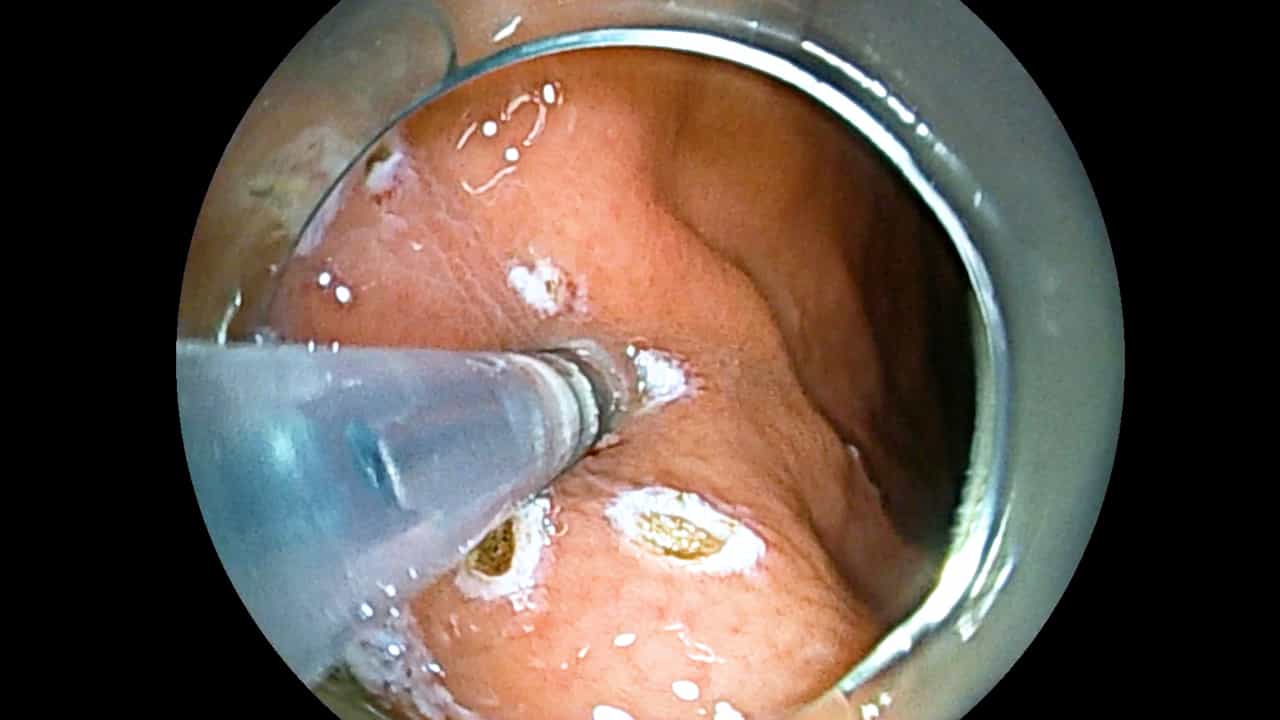
[Duodenal ulcers that do not heal for a long time]

Abstract:
The investigations of 43 duodenal ulcer cases in the patients whose ulcers failed to cicatrize after a 8-week treatment with almagel and vicalin or cimetidine monotherapy revealed the role of the hereditary load, smoking intensity, initial ulcer dimensions, the presence of antral erosions and a pronounced periulcerous duodenitis in the phenomenon of slow healing duodenal ulcer. There was no statistical difference between the values of the basal and pentagastrin-stimulated levels of hydrochloric acid secretion in the morning, partial alkaline gastric secretion, gastrinemia, the rate of evacuation of the gastric contents into the duodenum, the outcome of pancreatic bicarbonates in the sample with exogenic secretin in those whose ulcers cicatrized after a 6-week therapy and those who failed to be cured after being exposed to the same therapy during 8 weeks. The production of hydrochloric acid in the evening and the incidence of manifest duodenal reflux were significantly higher in the patients with slowly healing ulcer. They also had a decreased sensitivity to the intraduodenal inflow of the hydrochloric acid that resulted in the increase of endogenic secretin (stimulating the production of pancreatic bicarbonates and their transport into the duodenum). In case the combination treatment with almagel and vicalin failed, the therapy with gastrocepin or sucralfate was employed. A supplementary course of sucralfate helped to reach a complete healing of noncomplicated ulcers even in the patients in whom the preceding cimetidine treatment failed.
Related Concept Videos
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:27
Peptic Ulcer
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications