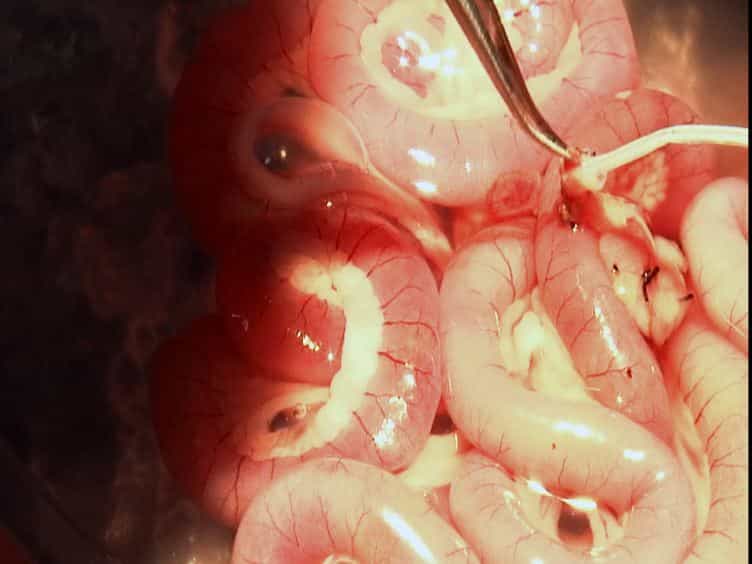
Related Experiment Video
Updated: Aug 24, 2026


Small Bowel Transplantation In Mice
Published on: August 20, 2007
New perspectives for children with microvillous inclusion disease: early small bowel transplantation
Frank M Ruemmele1, Dominique Jan, Florence Lacaille
1Combined Program of Liver and Intestinal Transplantation, Hôpital Necker-Enfants Malades, Paris, France. frank.ruemmele@nck.ap-hop-paris.fr.

Insights
Small bowel transplantation (SbTx) offers a life-saving option for children with microvillous inclusion disease (MVID), a congenital intestinal disorder. Combined liver-SbTx and associated colon grafting significantly improve survival and quality of life.
Area of Science:
- Gastroenterology
- Pediatric Surgery
- Transplantation Medicine
Background:
- Microvillous inclusion disease (MVID) is a rare congenital disorder causing lifelong intestinal failure.
- Patients with MVID face reduced life expectancy due to complications from total parenteral nutrition and liver failure.
Purpose of the Study:
- To evaluate the efficacy of small bowel transplantation (SbTx) in children with early-onset MVID.
- To assess the impact of combined liver-SbTx and associated colon grafting on patient outcomes.
Main Methods:
- Retrospective evaluation of 12 early-onset MVID patients between 1995 and 2002.
- Analysis of outcomes for patients undergoing SbTx, combined liver-SbTx, and those not transplanted.
Main Results:
- Seven of 12 patients underwent transplantation (3 SbTx, 4 liver-SbTx).
- Actuarial survival rates were 100% for SbTx and 75% for liver-SbTx, compared to 40% for non-transplanted patients.
- All transplanted patients were weaned from parenteral nutrition; those with colon grafts achieved autonomy faster.
Conclusions:
- SbTx, alone or with liver transplantation, is highly successful for MVID patients.
- Associated colon grafting significantly improves outcomes and quality of life in MVID patients post-SbTx.
Background:
Microvillous inclusion disease (MVID) is a congenital intestinal epithelial cell disorder leading to lifelong intestinal failure. Despite long-term total parenteral nutrition, life expectancy is extremely reduced because of metabolic or septic complications or liver failure.
Methods:
Twelve patients with early-onset MVID were evaluated between 1995 and 2002 for the possibility of small bowel transplantation (SbTx). Three patients died before they could be placed on the waiting list for SbTx, and one patient is still awaiting SbTx. SbTx was contraindicated in one patient.
Results:
Seven of 12 patients (six boys and one girl) underwent transplantation (three SbTxs and four combined liver-SbTxs). Actuarial survival rates were 100% and 75% in the SbTx and combined liver-SbTx groups, respectively, with a mean follow-up of 3 years (1.1-8.5 years). In contrast, the survival rate was only 40% in the subgroup of five patients who did not undergo transplantation. After transplantation, all patients were weaned from parenteral nutrition: the five patients with an additional colon graft were weaned within 36 days as opposed to the others without colonic transplant who obtained full intestinal autonomy several months after transplantation. The only two surviving patients who did not undergo SbTx remain highly dependent on total parenteral nutrition, which is complicated by repeated episodes of metabolic decompensation.
Conclusions:
SbTx alone or in combination with the liver is highly successful in children with MVID, offering them a long-term perspective for the first time. Associated colon grafting markedly improves the outcome and quality of life after SbTx in patients with MVID.