Related Experiment Video
Updated: Aug 24, 2026
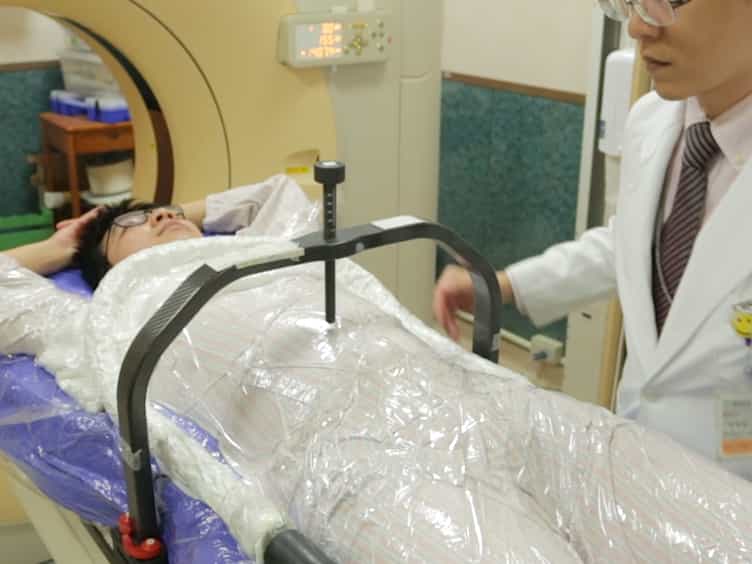
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Dosimetric effect of respiratory motion in external beam radiotherapy of the lung
James Mechalakos1, Ellen Yorke, Gikas S Mageras
1Department of Medical Physics, Memorial Sloan Kettering Cancer Center, 1275 York Ave., New York, NY 10021, USA.

Background And Purpose:
To study the effect of breathing motion on gross tumor volume (GTV) coverage for lung tumors using dose-volume histograms and relevant dosimetric indices.
Patients And Methods:
Treatment plans were chosen for 12 patients treated at our institution for lung carcinoma. GTV volumes of these patients ranged from 1.2 to 97.3 cm(3). A margin of 1-2 cm was used to generate the planning target volume (PTV). Additional margins of 0.6-1.0 cm were added to the PTV when designing treatment portals. For the purposes of TCP calculation, the prescription dose was assumed to be 70 Gy to remove the effects of prescription differences. Setup error was incorporated into the evaluation of treatment plans with a systematic component of sigma(RL) = 0.2 cm, sigma(AP) = 0.2 cm, and sigma(SI) = 0.3 cm and a random component of sigma(RL) = 0.3 cm, sigma(AP) = 0.3 cm, and sigma(SI) = 0.3 cm. Breathing motion was incorporated into these plans based on an independent analysis of fluoroscopic movies of the diaphragm for 7 patients. The systematic component of breathing motion (sigma(RL) = 0.3 cm, sigma(AP) = 0.2 cm, and sigma(SI) = 0.6 cm) was incorporated into the treatment plans on a slice by slice basis. The intrafractional component of breathing motion (sigma(RL) = 0.3 cm, sigma(AP) = 0.2 cm, and sigma(SI) = 0.6 cm) was incorporated by averaging the dose calculation over all displacements of the breathing cycle. Each patient was simulated 500 times to discern the range of possible outcomes. The simulations were repeated for a worst case scenario which used only breathing data with a large diaphragmatic excursion, both with and without intrafractional breathing motion.
Results:
Dose to 95% of the GTV (D95), volume of the GTV receiving 95% of the prescription dose (V95) and TCP changed an average of -1.4+/-4.2, -1.0+/-3.3, and -1.4+/-3.8%, respectively, with the incorporation of normal breathing effects. In the worst case scenario (heavy breathers), D95 and V95 changed an average of -9.8+/-10.1 and -8.3+/-11.3%, respectively, and TCP changed by -8.1+/-9.1%. GTVs with volumes greater than 60 cm(3) showed stronger sensitivity to breathing especially if the shape was non-ellipsoidal. In the normal breathing case, the probability of a decrease in D95, V95, or TCP of a magnitude greater than 10% is less than 4%, and in the worse case scenario this probability is approximately 30-40% with intrafractional breathing motion included, and less than 10% with intrafractional breathing motion not included.
Conclusions:
With the PTV margins routinely used at our center, the effects of normal breathing on coverage are small on the average, with a less than 4% chance of a 10% or greater decrease in D95, V95, or TCP. However, in patients with large respiration-induced motion, the effect can be significant and efforts to identify such patients are important.
More Related Videos
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 02:59
Biological Effects of Radiation