Related Experiment Video
Updated: Jul 28, 2026
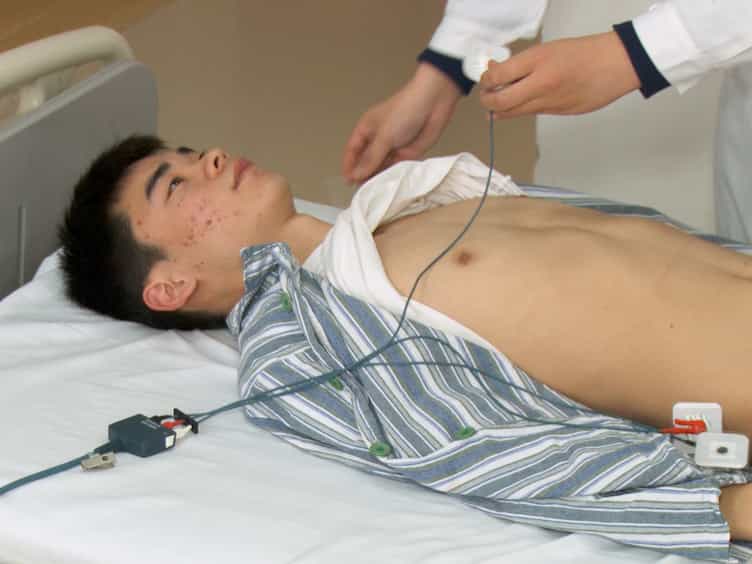

Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
Hypertension guideline 2003 update

Insights
Treating hypertension effectively lowers risks of stroke and heart failure. Target blood pressure (BP) is generally below 140/90 mmHg, with gradual reduction for the elderly and severe cases.
Area of Science:
- Cardiology
- Hypertension Management
Background:
- Extensive data confirm the benefits of hypertension treatment.
- Optimal blood pressure (BP) targets are systolic < 140 mmHg and diastolic < 90 mmHg, aiming for minimal side effects.
Framework:
- Cardiovascular risk factor evaluation is crucial for personalized management strategies.
- Lifestyle modifications and patient education are essential components of hypertension management.
Implementation:
- First-line therapy includes low-dose thiazide-like diuretics.
- Second-line options include reserpine, beta-blockers, ACE inhibitors, or calcium channel blockers.
- Third-line therapy involves adding another second-line agent, hydralazine, or an alpha-blocker.
Implications:
- Hypertension management reduces the risk of stroke, cardiac failure, and renal insufficiency.
- Guidelines address specific situations like hypertensive emergencies, severe hypertension with target organ damage, and hypertension in diabetes mellitus.
Outcomes:
Extensive data from many randomised controlled trials have shown the benefit of treating hypertension. The target blood pressure (BP) for antihypertensive management should be systolic BP < 140 mmHg, diastolic < 90 mmHg, with minimal or no drug side-effects. However, a lesser reduction will elicit benefit although this is not optimal. The reduction of BP in the elderly and in those with severe hypertension should be achieved gradually over 6 months. Stricter BP control is required for patients with end organ damage, co-existing risk factors and co-morbidity, e.g. diabetes mellitus. Co-existent risk factors should also be controlled.
Benefits:
Reduction in risk of stroke, cardiac failure, renal insufficiency and probably coronary artery disease. The major precautions and contraindications to each antihypertensive drug recommended are listed.
Recommendations:
Correct BP measurement procedure is described. Evaluation of cardiovascular risk factors and recommendations for antihypertensive therapy are stipulated. The total cardiovascular disease risk profile should be determined for all patients and this should inform management strategies. Lifestyle modification and patient education plays an essential role in the management strategy. Drug therapy: First line--low dose thiazide-like diuretics; second line--add one of the following: reserpine, or beta-blockers or ACE inhibitors or calcium channel blockers; third line--add another second line drug or hydralazine or alpha-blocker. The guideline includes management of specific situations, i.e. hypertensive emergency and urgency, severe hypertension with target organ damage and refractory hypertension (BP > 160/95 mmHg on triple therapy), hypertension in diabetes mellitus, etc.
Validity:
Developed by the Working Groups established by the Executive Committee of the Southern African Hypertension Society with broader consensus meeting endorsement. The 2001 version was endorsed by the South African Medical Association Guideline Committee. The 2003 revisions were endorsed by the Executive Committee and a wider Working Group.

Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Hypertension I: Introduction
 01:29
Hypertension II: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:23
Hypertension V: Nursing Management