Related Experiment Video
Updated: Aug 24, 2026
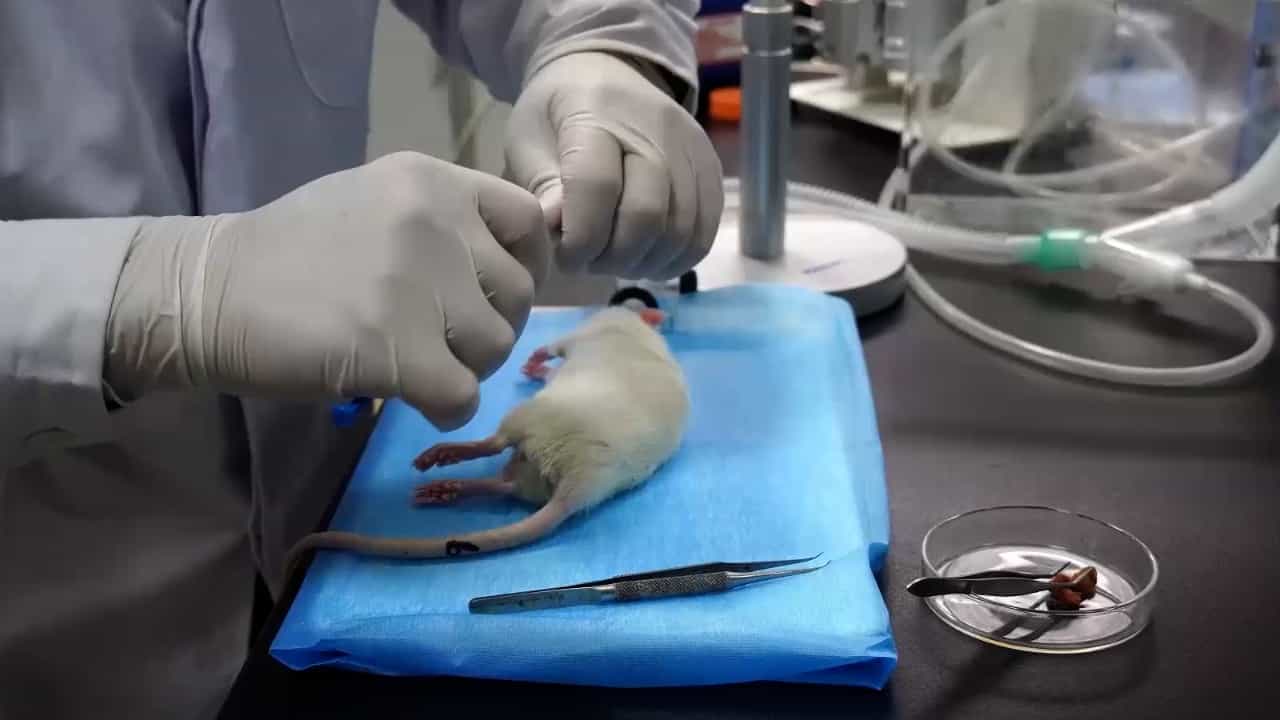

A Modified Method for Intrathecal Catheterization in Rats
Published on: February 14, 2025
Intrathecal amikacin for the treatment of pseudomonal meningitis
Kimberly A Corpus1, Kathryn B Weber, Christopher R Zimmerman
1Department of Pharmacy Services, Henry Ford Hospital, 2799 W. Grand Boulevard, Detroit, MI 48202-2689, USA. kcorpus1@hfhs.org

Objective:
To report a case of gram-negative bacillary meningitis (GNBM) secondary to multidrug-resistant Pseudomonas aeruginosa that was treated with intravenous meropenem and intrathecal and intravenous amikacin.
Case Summary:
A 76-year-old Arabic woman with previous placement of an extraventricular device developed meningitis secondary to P. aeruginosa as a result of a previous pneumonia. The patient was treated with intravenous meropenem and amikacin, with the addition of intrathecal amikacin, until cerebrospinal cultures remained negative for 18 days. She did not experience any adverse effects as a result of the administration of the intrathecal amikacin. Although the meningitis subsequently resolved, the patient eventually died due to Candida glabrata fungemia.
Discussion:
Dual therapy is recommended for patients with P. aeruginosa meningitis. In our patient, the increasing resistance to imipenem and resistance to all other potential antibiotics resulted in the use of an alternative administration technique that has not been well documented in recent literature.
Conclusions:
In patients who have GNBM due to P. aeruginosa, the combination of intrathecal and intravenous amikacin may be an option for therapy, especially when clinical options are limited by resistance, severity of illness, and location of the infection. More information is required and further study is needed on this topic.
Insights
This case study highlights successful treatment of multidrug-resistant Pseudomonas aeruginosa meningitis using intravenous and intrathecal amikacin. This combination therapy offers a viable option when conventional antibiotics fail, particularly in severe infections.
Area of Science:
- Infectious Diseases
- Neuroscience
- Pharmacology
Background:
- Gram-negative bacillary meningitis (GNBM) poses significant treatment challenges, especially with multidrug-resistant pathogens.
- Pseudomonas aeruginosa is a common cause of healthcare-associated infections, including meningitis, often exhibiting resistance to multiple antibiotics.
Observation:
- A case of a 76-year-old woman with GNBM caused by multidrug-resistant Pseudomonas aeruginosa, secondary to pneumonia and complicated by an extraventricular device.
- The patient received dual therapy with intravenous meropenem and both intravenous and intrathecal amikacin.
- Cerebrospinal fluid cultures turned negative after 18 days of treatment, with no adverse effects reported from intrathecal amikacin administration.
Findings:
- Intravenous and intrathecal amikacin, combined with meropenem, effectively treated multidrug-resistant Pseudomonas aeruginosa meningitis.
- The patient's meningitis resolved, although she later succumbed to Candida glabrata fungemia.
Implications:
- Intrathecal and intravenous amikacin combination therapy is a potential treatment option for P. aeruginosa meningitis, especially in cases with limited antibiotic choices due to resistance.
- This approach may be crucial for severe infections or when standard treatment protocols are insufficient.
- Further research is needed to establish the efficacy and safety of this dual-route amikacin administration in treating P. aeruginosa meningitis.

Related Concept Videos
 01:27
Cryptococcal Meningitis
 01:22
Bacterial Meningitis I: Introduction
 01:26
Brain Abscess l: Introduction
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia