Related Experiment Video
Updated: Aug 24, 2026
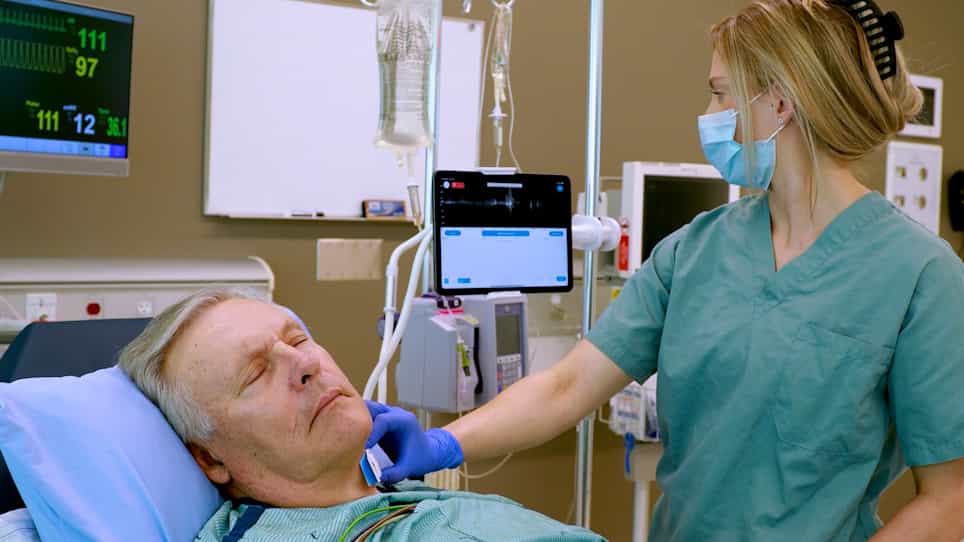

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Preload-dependent variation of the propagation velocity in patients with congestive heart failure
Yoshihiro Seo1, Toshiyuki Ishimitsu, Tomoko Ishizu
1Department of Internal Medicine, Ibaraki Seinan Medical Center Hospital, Sakai, Ibaraki, Japan. seo@bf6.so-net.ne.jp

Insights
Propagation velocity (Vp) in congestive heart failure (CHF) patients decreases as pulmonary capillary wedge pressure lowers with treatment. This preload-dependent variation in Vp should be considered during CHF patient assessments.
Area of Science:
- Cardiology
- Echocardiography
- Hemodynamics
Background:
- Color Doppler M-mode propagation velocity (Vp) is generally considered preload-independent.
- However, its variation with dynamic preload changes in clinical settings, particularly in congestive heart failure (CHF) patients, remains unevaluated.
- Left ventricular filling pressure significantly fluctuates during CHF treatment.
Purpose of the Study:
- To investigate the hypothesis that preload-dependent variations in Vp occur during the treatment of CHF.
- To evaluate the relationship between changes in Vp and hemodynamic parameters, specifically pulmonary capillary wedge pressure, in CHF patients undergoing therapy.
Main Methods:
- Doppler echocardiography and hemodynamic evaluations were conducted in 24 CHF patients.
- Data were collected at baseline presentation and after improvement with therapy (second study).
- Stepwise linear regression analysis was used to identify predictors of Vp change.
Main Results:
- Vp significantly decreased from 41 ± 5 cm/s at baseline to 28 ± 5 cm/s in the second study (P <.0001).
- The change in pulmonary capillary wedge pressure (-8.3 ± 3.3 mm Hg) was the sole independent predictor of the change in Vp (-12.5 ± 5.9 cm/s) (r = 0.68, P =.0002).
- The interval between studies was 48.6 ± 21.5 hours.
Conclusions:
- Vp significantly decreases with reductions in pulmonary capillary wedge pressure during CHF treatment.
- The observed preload-dependent variation in Vp necessitates consideration in clinical assessments of CHF patients.
- These findings highlight the dynamic nature of Vp in response to hemodynamic changes in heart failure.
Background:
Although color Doppler M-mode propagation velocity (Vp) is preload-independent, the variation in Vp with the temporal variation of preload in the clinical setting has not been evaluated. Because left ventricular filling pressure changes dramatically with treatment of congestive heart failure (CHF), we hypothesized that preload-dependent variations in Vp occur with treatment of CHF.
Methods:
We performed Doppler echocardiographic and hemodynamic evaluation in 24 patients with CHF (15 men, 62 +/- 10 years) at initial presentation (baseline study) and after CHF had improved with therapy (second study).
Results:
The interval between the baseline and the second study was 48.6 +/- 21.5 hours. Vp decreased between the baseline study (41 +/- 5 cm/s) and the second study (28 +/- 5 cm/s, P <.0001). Only the change in pulmonary capillary wedge pressure (-8.3 +/- 3.3 mm Hg) between the baseline and second study was an independent predictor of the change in Vp (-12.5 +/- 5.9 cm/s) by stepwise linear regression (r = 0.68, P =.0002).
Conclusions:
Vp decreases significantly with decreases in pulmonary capillary wedge pressure with the treatment of CHF. The preload-dependent variation should be taken into account in the assessment of Vp in patients with CHF.


Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Heart Failure II: Pathophysiology
 01:19
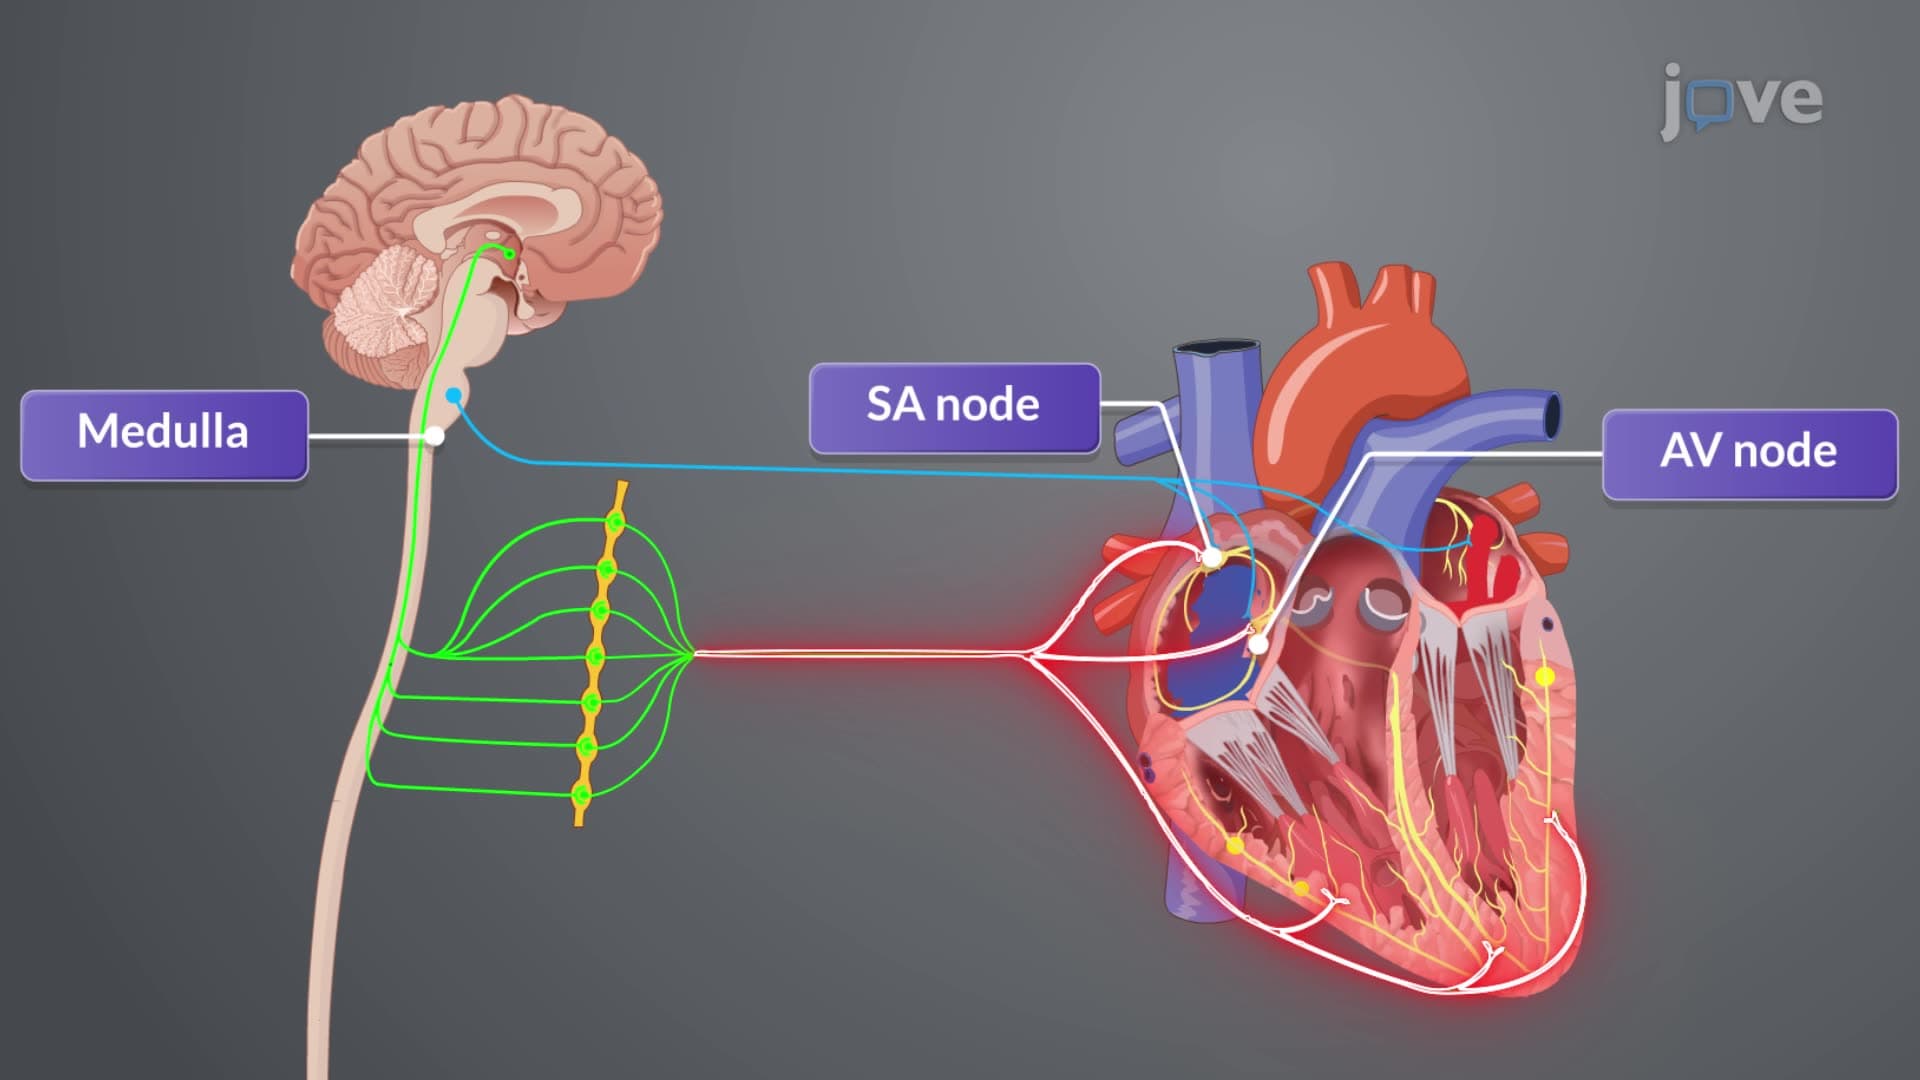
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:17
Pathophysiology of Heart Failure
 01:26
Heart Failure III: Clinical Manifestations
 01:26
Heart Failure Drugs: Inotropic Agents