Related Experiment Video
Updated: Aug 8, 2026

Synthesis of a Borylated Ibuprofen Derivative Through Suzuki Cross-Coupling and Alkene Boracarboxylation Reactions
Published on: November 30, 2022
Drug switching patterns among patients with rheumatoid arthritis and osteoarthritis using COX-2 specific inhibitors
Sean Z Zhao1, Chuck Wentworth, Thomas A Burke
1Pharmacia Global Health Outcomes, Peapack, NJ, USA.

Purpose:
To compare RA and OA patients' time-to-switch after newly initiating treatment with three most commonly used non-specific (NS)-NSAIDs and two COX-2 inhibitors, celecoxib and rofecoxib.
Methods:
Managed care enrollees newly prescribed celecoxib, rofecoxib, ibuprofen, naproxen or diclofenac were identified. Time to switch to a different NS-NSAID or COX-2 specific inhibitor was determined using time-to-event analysis and Cox proportional hazards models were used to estimate the odds ratio (OR) after controlling for potential confounders.
Results:
The time to 25% of the cohort switching was longer for rofecoxib and celecoxib (159 and 205 days respectively) compared to the three NS-NSAIDs (49-78 days). Patients were at the highest risk of switching within the first 100 days of therapy. After adjusting for potential confounding factors, the OR for switching to another NS-NSAID or COX-2 specific inhibitor ranged from 1.74 to 2.35 for the three NS-NSAIDs compared to celecoxib (all comparisons, p < 0.01). Similar findings were obtained when comparing rofecoxib to each of the three NS-NSAIDS (all comparisons, p < 0.01). When COX-2 inhibitors combined were compared to NS-NSAIDS combined, the OR for switching was 1.53 (95% confidence interval = 1.42-1.65; p < 0.01) after adjusting for potential confounders.
Conclusions:
Patients on the COX-2 specific inhibitors (celecoxib and rofecoxib) were significantly less likely to switch their therapy than patients on NS-NSAIDS (ibuprofen, naproxen and diclofenac). These results suggest that COX-2 specific inhibitors may be a more effective treatment option when compared with NS-NSAIDs in usual clinical practice.
Insights
Patients initiating non-specific NSAIDs switched medications more often than those on COX-2 inhibitors like celecoxib and rofecoxib. This suggests COX-2 inhibitors may offer more stable treatment for arthritis in clinical practice.
Area of Science:
- Pharmacology
- Rheumatology
- Clinical Practice
Background:
- Non-specific NSAIDs (NS-NSAIDs) and COX-2 inhibitors are commonly used for arthritis pain.
- Understanding patient adherence and treatment switching is crucial for optimizing arthritis management.
Purpose of the Study:
- To compare the time to medication switch between non-specific NSAIDs and COX-2 inhibitors in patients with rheumatoid arthritis (RA) and osteoarthritis (OA).
Main Methods:
- Retrospective analysis of managed care enrollees newly prescribed celecoxib, rofecoxib, ibuprofen, naproxen, or diclofenac.
- Time-to-event analysis and Cox proportional hazards models were used to assess switching risk.
Main Results:
- Patients on COX-2 inhibitors (celecoxib, rofecoxib) had significantly longer time-to-switch (159-205 days) compared to NS-NSAIDs (49-78 days).
- The risk of switching was highest within the first 100 days of therapy.
- Adjusted odds ratios indicated a 1.74-2.35 times higher risk of switching from NS-NSAIDs compared to celecoxib.
Conclusions:
- COX-2 inhibitors (celecoxib, rofecoxib) demonstrated greater treatment stability than NS-NSAIDs.
- These findings suggest that COX-2 inhibitors may be a more effective therapeutic option in routine clinical practice for arthritis management.


Related Concept Videos
 01:30
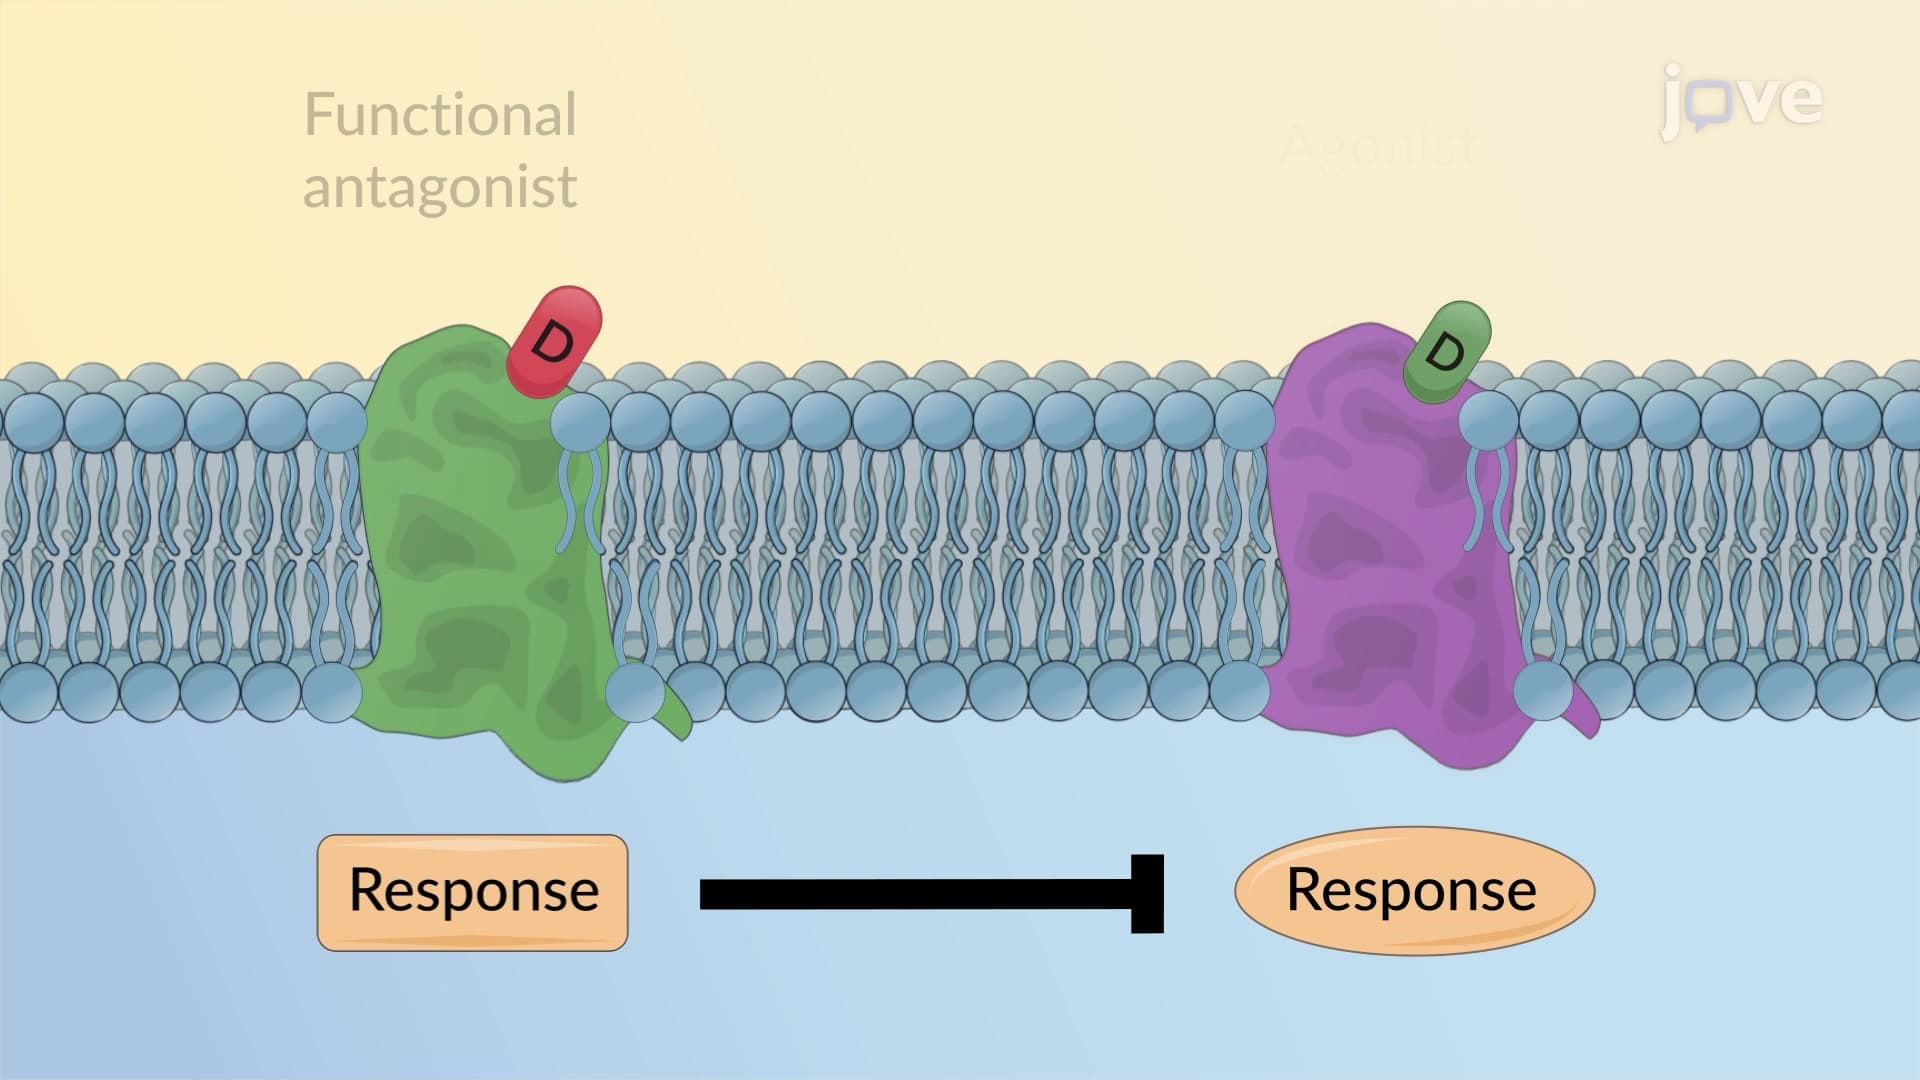
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:24
Drugs for Treatment of Crohn's Disease in IBD Using Biologic Agents: Anti-TNF
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:09
Bioequivalence of Drugs: Drugs with Multiple Indications