Related Experiment Video
Updated: Aug 24, 2026
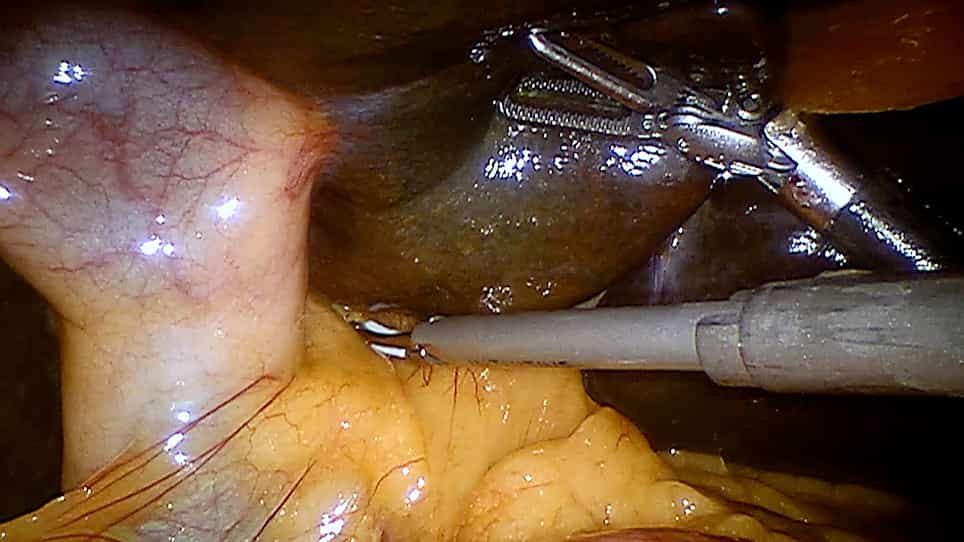

Robotic Taj Mahal Hepatectomy for Hilar Cholangiocarcinoma
Published on: July 14, 2022
Major hepatic resection for hilar cholangiocarcinoma: analysis of 46 patients
David J Rea1, Manuel Munoz-Juarez, Michael B Farnell
1Department of Surgery, Division of Gastroenterologic and General Surgery, Mayo Clinic College of Medicine, Rochester, MN 55905, USA.

Hypothesis:
Major hepatectomy, bile duct resection, and regional lymphadenectomy for hilar cholangiocarcinoma are associated with actual long-term (>5 years) survival.
Design:
Retrospective outcome study.
Setting:
Single tertiary referral institution.
Patients:
Between 1979 and 1997, 46 consecutive patients had resection of hilar cholangiocarcinoma by major hepatectomy, bile duct resection, and regional lymphadenectomy.
Main Outcome Measures:
Overall survival and tumor recurrence were correlated to clinicopathological factors, operative morbidity, and mortality.
Results:
Twenty-five patients underwent left hepatectomy, 17 underwent right hepatectomy, and 4 had extended right hepatectomy. Eighteen patients underwent resection of segment 1. Negative (R0) resection margins were achieved in 37 patients (80%). The operative mortality rate was 9%, and the surgical morbidity rate was 52%. Actual 1-year, 3-year, and 5-year survival rates were 80%, 39%, and 26%, respectively. Factors adversely associated with patient survival rates included: male sex, lymph node metastases, tumor grade 3 or 4, elevated direct serum bilirubin level at diagnosis, elevated preoperative activated partial thromboplastin time, and more than 4 U of red blood cells transfused perioperatively. Tumor size and R0 resection approached significance for survival. Factors associated with tumor recurrence included: male sex, tumor grade 3 or 4, a low hemoglobin level both at diagnosis and preoperatively, and a low preoperative prothrombin time and low alkaline phosphatase level at diagnosis and preoperatively. Median time to recurrence was 3.6 years. Tumor recurrence was predominantly local and regional.
Conclusions:
The actual 5-year survival rate of 26% justifies major partial hepatectomy, bile duct resection, and regional lymphadenectomy for hilar cholangiocarcinoma. The high frequency of local and regional recurrence warrants investigation of adjuvant therapy.