Related Experiment Video
Updated: Aug 24, 2026

Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Effect of caffeine intake on myocardial hyperemic flow induced by adenosine triphosphate and dipyridamole
Shigeto Kubo1, Eiji Tadamura, Hiroshi Toyoda
1Department of Nuclear Medicine and Diagnostic Imaging, Kyoto University Graduate School of Medicine, Kyoto, Japan. kub@kuhp.kyoto-u.ac.jp

Unlabelled:
The aims of this study were (a). to compare absolute myocardial blood flow (MBF) during adenosine triphosphate (ATP) infusion with that after dipyridamole administration without caffeine intake and (b). to evaluate the effect of caffeine intake on the hyperemic flow induced by these coronary vasodilator agents.
Methods:
MBF was quantified with (15)O-labeled water and PET at rest, during ATP infusion (0.16 mg/kg/min for 9 min), and after dipyridamole administration (0.56 mg/kg over 4 min) after a 24-h abstinence from caffeine (baseline evaluation) in 10 healthy volunteers. Within 2 wk, the same PET studies were repeated after caffeine intake to evaluate the effect of caffeine on the hyperemic flow induced by these pharmacologic agents (caffeine study). Myocardial flow reserve (MFR), defined as the ratio of hyperemic to resting blood flow, was also evaluated.
Results:
Resting MBF in baseline and caffeine studies did not differ significantly (0.79 +/- 0.29 vs. 0.75 +/- 0.31 mL/min/g, P = 0.88). Without caffeine intake, MBF during ATP infusion was significantly higher than that after dipyridamole administration (3.70 +/- 0.67 vs. 3.00 +/- 0.79 mL/min/g, P = 0.003), whereas there was no significant difference in MFR between ATP and dipyridamole stress (5.15 +/- 1.64 vs. 4.11 +/- 1.44, P = 0.07). After caffeine intake, the hyperemic flows induced by ATP and dipyridamole were not significantly different (1.68 +/- 0.37 vs. 1.52 +/- 0.40 mL/min/g, P = 0.50). MFR estimated by ATP and dipyridamole also did not differ significantly in the caffeine studies (2.44 +/- 0.88 vs. 2.25 +/- 0.94, P = 0.73). MBF during ATP infusion and after dipyridamole administration were significantly lower in the caffeine studies than that in the baseline evaluation (1.68 +/- 0.37 vs. 3.70 +/- 0.67 mL/min/g, P < 0.0001, and 1.52 +/- 0.40 vs. 3.00 +/- 0.79 mL/min/g, P < 0.0001, respectively).
Conclusion:
This study demonstrates that ATP has the potential to induce greater hyperemia than dipyridamole, whereas hyperemic responses to ATP and dipyridamole are similarly attenuated after caffeine intake. These findings suggest that abstinence from caffeine before ATP stress testing may be needed.
More Related Videos
 10:28
Interventional Diagnostic Procedure: A Practical Guide for the Assessment of Coronary Vascular Function
Published on: March 15, 2022
 08:51
Intra-cardiac Side-Firing Light Catheter for Monitoring Cellular Metabolism using Transmural Absorbance Spectroscopy of Perfused Mammalian Hearts
Published on: May 12, 2019
Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Adrenergic Agonists: Indirect-Acting Agents
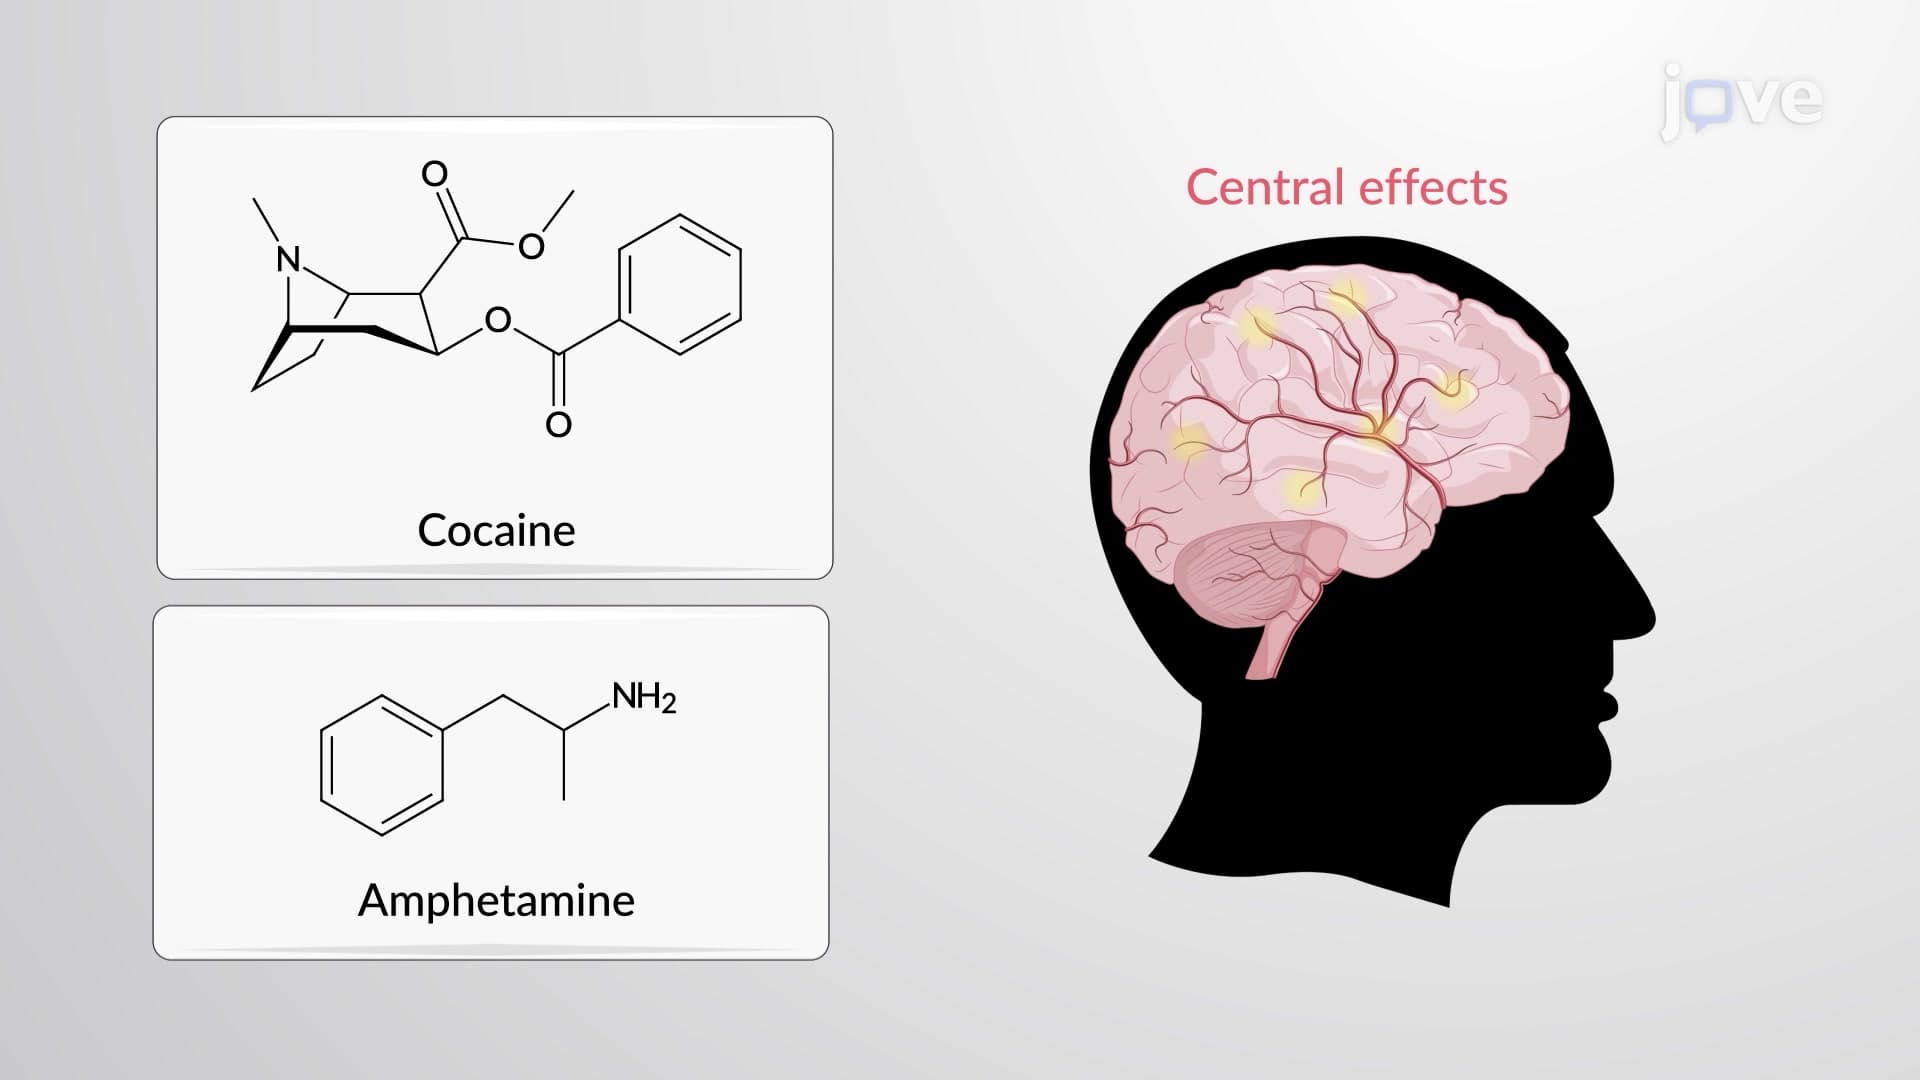
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...