Related Experiment Video
Updated: Aug 10, 2026


Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
The influence of physiotherapy and suction on respiratory deadspace in ventilated children
1Centre for Nursing and Allied Health Professionals Research and Physiotherapy Department, Institute of Child Health, 7th Floor, Old Building, Great Ormond Street Hospital for Children NHS Trust, Great Ormond Street, London WCIN 3JH, UK. maine@gosh.nhs.uk

Insights
Respiratory physiotherapy significantly increased physiological and alveolar deadspace in ventilated children, unlike suction. These deadspace measures may better reflect gas exchange changes than carbon dioxide levels.
Area of Science:
- Pediatric critical care medicine
- Respiratory physiology
- Mechanical ventilation
Background:
- Ventilated infants and children often require airway clearance techniques.
- Respiratory physiotherapy and suction are common interventions, but their comparative effects on gas exchange are not fully understood.
Purpose of the Study:
- To compare the effects of respiratory physiotherapy and suction on deadspace volumes.
- To assess impacts on carbon dioxide elimination (VCO(2)), end-tidal CO(2) (ETCO(2)), and arterial partial pressure of CO(2) (PaCO(2)) in ventilated pediatric patients.
Main Methods:
- A randomized crossover study involving 81 fully ventilated children.
- Participants received both respiratory physiotherapy and suction with a washout period.
- Gas exchange parameters, including deadspace volumes, were measured using a respiratory monitor.
Main Results:
- Respiratory physiotherapy led to significant increases in physiological deadspace (VD(phys))/kg and alveolar deadspace (VD(alv))/kg.
- Suction did not produce significant changes in these deadspace measures.
- Significant differences were observed between the two interventions in VD(phys)/kg, VD(alv)/kg, expired tidal volumes (V(TE)), mixed expired CO(2) (PeCO(2)), and ETCO(2).
Conclusions:
- Differences in technique likely explain the distinct effects of physiotherapy and suction on deadspace.
- Physiological and alveolar deadspace may be more sensitive indicators of subtle gas exchange and ventilation changes than VCO(2) or PaCO(2).
- Interpreting deadspace changes requires concurrent analysis of related parameters.
Objective:
To assess and compare the effects of respiratory physiotherapy and suction on deadspace volumes, carbon dioxide elimination (VCO(2)), end tidal CO(2) (ETCO(2)), and arterial partial pressure of carbon dioxide (PaCO(2)) in ventilated infants and children.
Design:
Randomised crossover study. Participants received both treatments with a washout interval of more than 90 min.
Setting:
Intensive tertiary care units, Great Ormond Street Hospital, London.
Patients:
Eighty-seven fully ventilated children, requiring physiotherapy, with arterial lines in situ. Paired measurements were obtained in 81 patients, of whom 6 were excluded because of tracheal tube leak greater than 20%.
Interventions:
Respiratory physiotherapy and suction.
Measurements And Results:
Data were collected April 1998-March 2000. The "CO(2)SMO Plus" respiratory monitor was used to calculate parameters before and 30 min after both interventions. Physiotherapy lasted longer and required more saline and catheters per treatment ( p<0.005). There were significant increases in physiological deadspace (VD(phys))/kg ( p<0.0001), alveolar deadspace (VD(alv))/kg ( p<0.0001) and VD(phys)/tidal volume (V(T)) ( p<0.05) following physiotherapy that were not observed following suction. There were no significant changes following either treatment with respect to airway deadspace (VD(airway)), VCO(2) or PaCO(2). Comparison of the mean differences following treatments indicated significant differences between physiotherapy and suction in terms of VD(phys)/kg ( p<0.005), VD(alv)/kg ( p<0.005), expired tidal volumes (V(TE)) ( p<0.05), mixed expired CO(2) (PeCO(2)) ( p<0.04) and ETCO(2) ( p<0.03).
Conclusions:
Differences between physiotherapy and suction techniques probably accounted for their statistically distinguishable effects on deadspace. VD(phys) and VD(alv) may be more sensitive indicators of subtle changes in gas exchange and regional ventilation than VCO(2) or PaCO(2). However, interpretation of these outcomes is dependent on concurrent examination of the parameters from which they are derived.
More Related Videos


Related Concept Videos
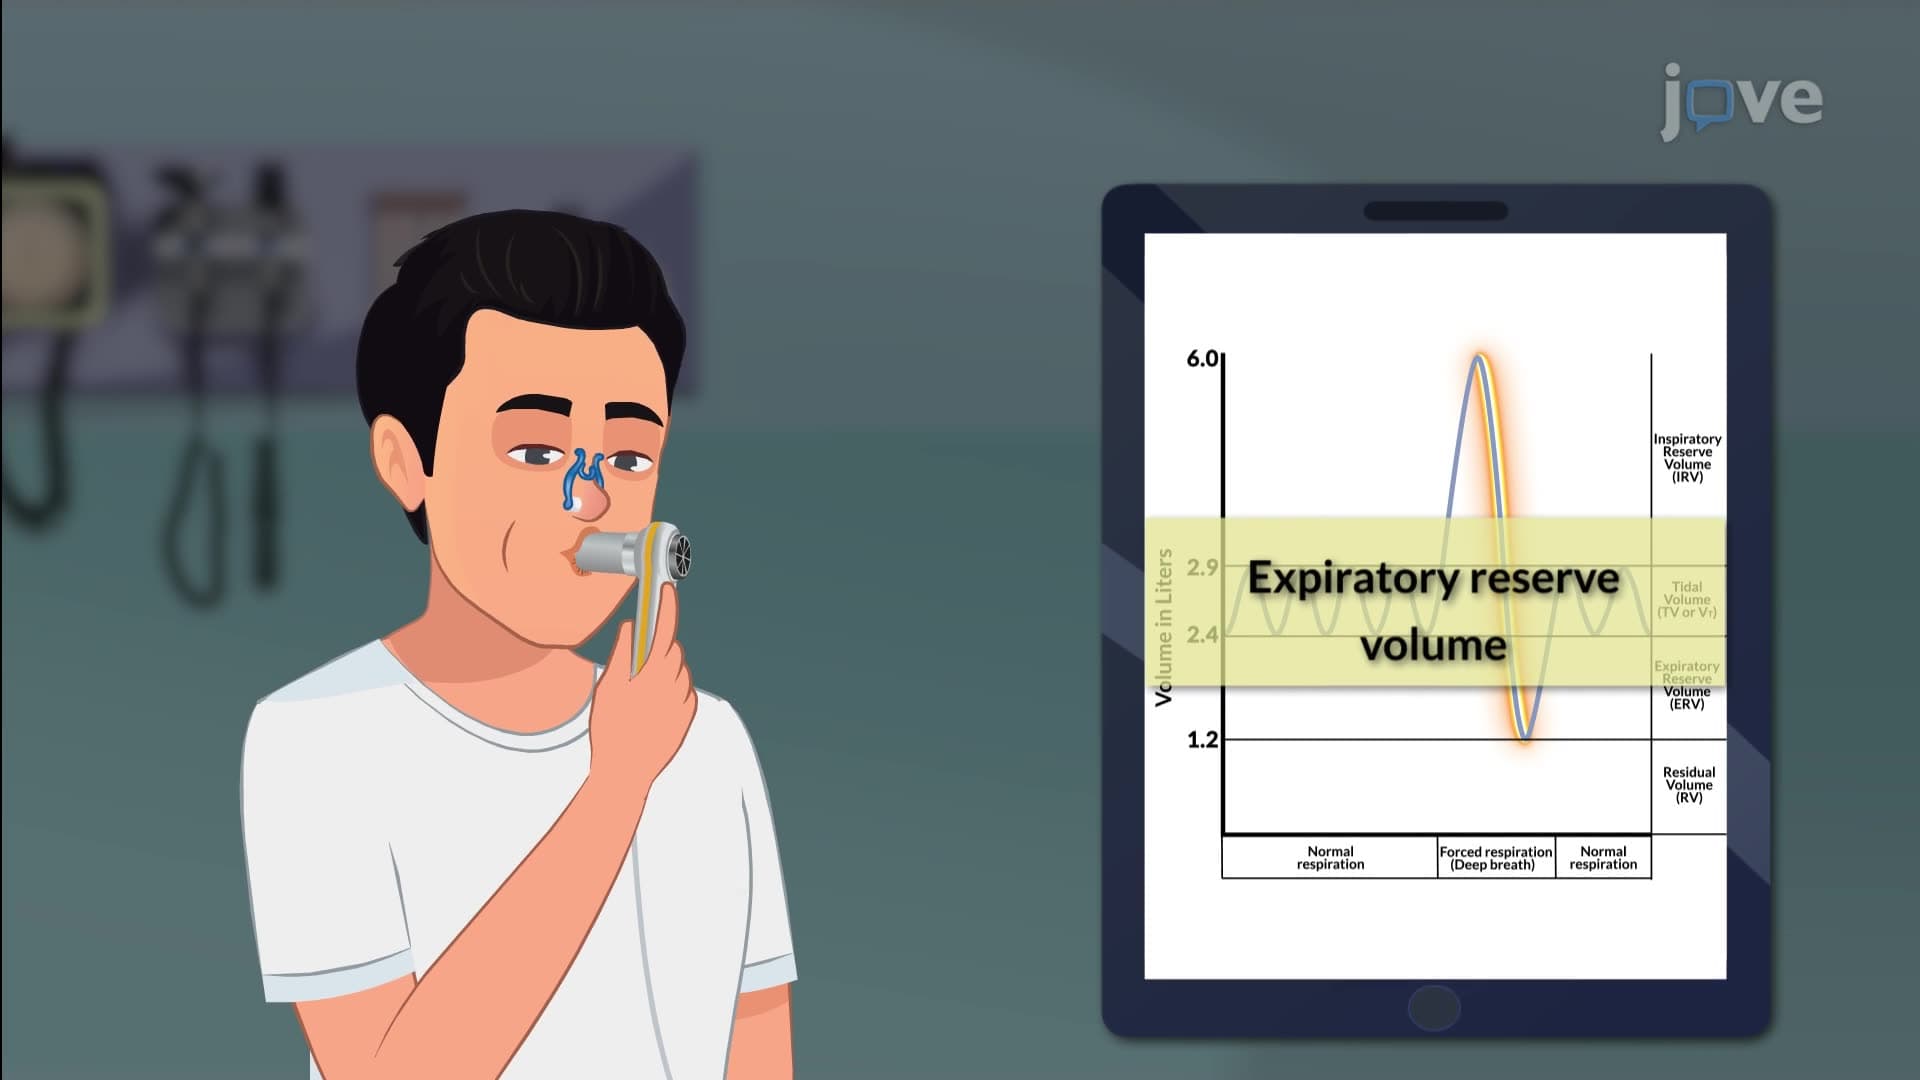 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
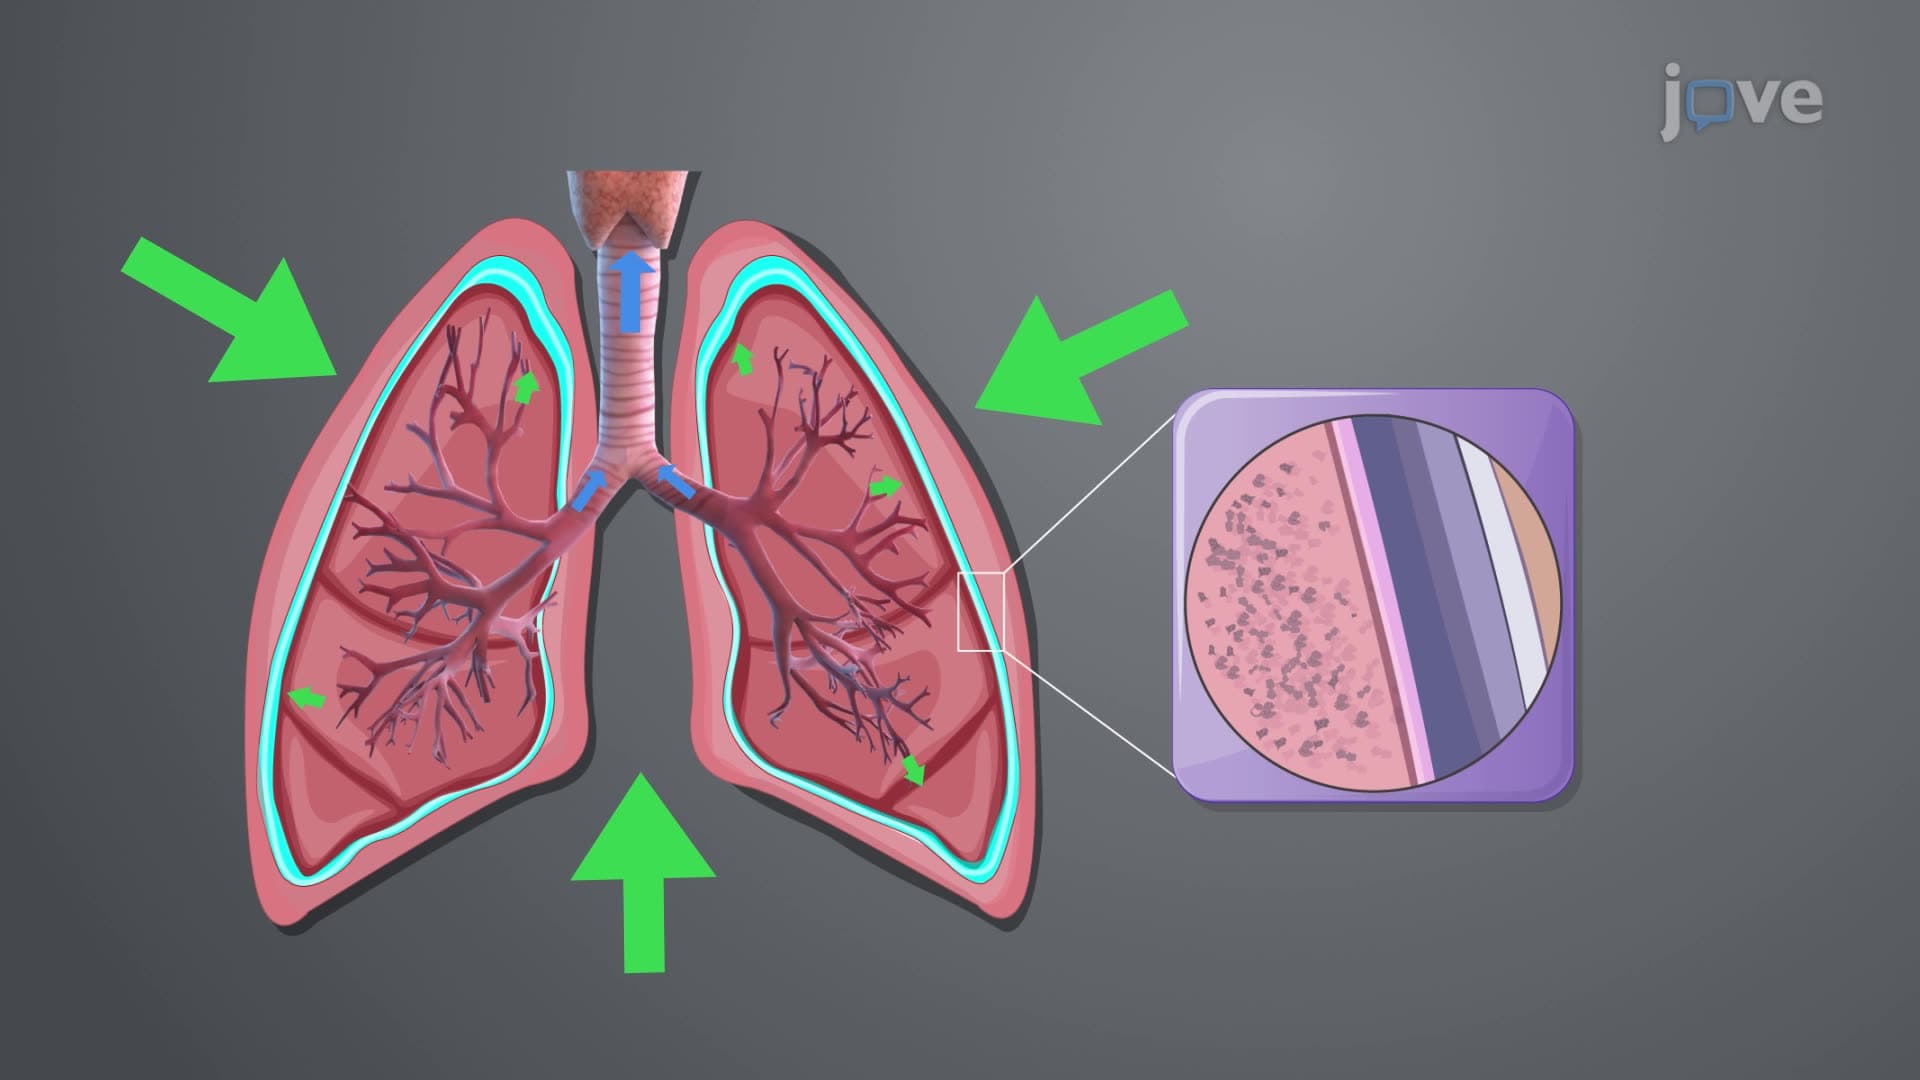 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...