Related Experiment Video
Updated: Aug 24, 2026
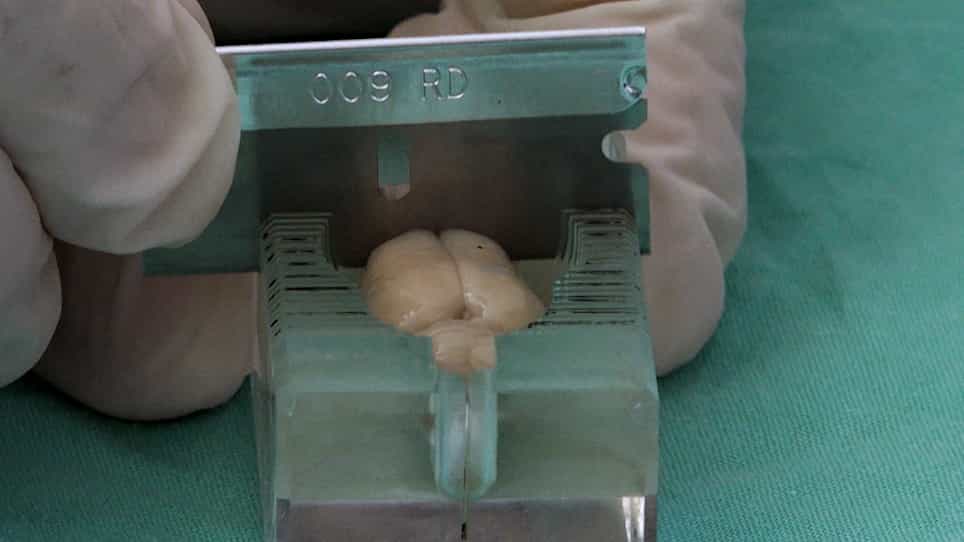

Measuring Post-Stroke Cerebral Edema, Infarct Zone and Blood-Brain Barrier Breakdown in a Single Set of Rodent Brain Samples
Published on: October 23, 2020
[EBM of cerebral infarction: message from mega-studies]
1Department of Neurology, Neurological Institute, Tokyo Women's Medical University.

Insights
Antiplatelet therapy, particularly low-dose aspirin, effectively reduces vascular events in high-risk patients. Warfarin and aspirin show varying efficacy for stroke prevention in non-valvular atrial fibrillation, with individualized recommendations based on risk factors.
Area of Science:
- Cardiovascular Medicine
- Neurology
- Pharmacology
Background:
- Antiplatelet therapy significantly reduces vascular events in high-risk patients with obstructive vascular disease.
- Low-dose aspirin (75-150 mg) is most effective; doses below 75 mg lack proven efficacy.
- Cilostazol shows efficacy in preventing recurrent ischemic stroke, particularly in Japanese patients with lacunar stroke.
Purpose of the Study:
- To review the efficacy of antiplatelet agents and anticoagulants in preventing vascular events and stroke.
- To compare warfarin with aspirin and other agents in specific patient populations, including non-valvular atrial fibrillation (NVAF).
- To evaluate the role of anticoagulation in stroke patients with patent foramen ovale (PFO).
Main Methods:
- Meta-analysis of antiplatelet therapy by the Antithrombotic Trialists' Collaboration.
- Review of large randomized controlled trials (RCTs) like MATCH, ACTIVE, and CHARISMA.
- Analysis of studies comparing anticoagulants (warfarin, ximelagatran) and antiplatelets (aspirin) in NVAF and ischemic stroke patients.
Main Results:
- Antiplatelet therapy significantly reduces stroke, myocardial infarction (MI), and vascular death in high-risk individuals.
- Warfarin is recommended for NVAF patients over 75 or with specific risk factors; aspirin is an alternative for lower-risk patients.
- Warfarin showed no efficacy over aspirin in most ischemic stroke subtypes without NVAF, and in stroke patients with PFO.
Conclusions:
- Low-dose aspirin is a cornerstone for preventing vascular events in high-risk populations.
- Anticoagulation strategies for NVAF require careful patient selection based on stroke risk factors and age.
- The role of warfarin in stroke prevention is limited to specific conditions like NVAF and PFO with deep vein thrombosis.
Abstract:
A meta-analysis by the Antithrombotic Trialists' Collaboration showed significant reduction of vascular events including stroke. MI, and vascular death by antiplatelet therapy in high risk patients with obstructive vascular disease. Low dose aspirin of 75 to 150 mg was most effective and its very low dose below 75 mg was not proven effective. Cilostazol significantly reduced the risk of recurrence in Japanese patients with ischemic stroke, mostly lacunar stroke. Large randomized controlled trials (RCTs) such as MATCH, ACTIVE, and CHARISMA are ongoing to see an effect of aspirin plus clopidogrel. Among patients with non-valvular atrial fibrillation (NVAF), warfarin is recommended in patients at age over 75 years, and those with history of stroke or TIA, hypertension, congestive heart failure, diabetes or coronary heart disease, while aspirin can be alternative in patients without any of these risk factors of stroke. Target INR of 2.0 to 3.0 is recommended in these NVAF patients, although lower INR of 1.6 to 2.5 is recommended to avoid hemorrhagic stroke in elderly patients with NVAF. SPORTIF was conducted to compare ximelagatran, an oral thrombin inhibitor, with warfarin in NVAF patients with risk factors, and the result showed a comparable efficacy and safety of ximelagatran. WARSS did not show any efficacy of warfarin over aspirin in any subtypes of ischemic stroke patients without NVAF, acute MI, left ventricular thrombi, or prosthetic heart valve. PICSS, a substudy of WARSS, also did not show any efficacy of warfarin over aspirin in stroke patients with patent foramen ovale (PFO), although warfarin might be recommended in PFO patients with deep vein thrombosis.
More Related Videos

Related Concept Videos
 01:22
Cerebral Edema ll: Pathophysiology
 01:15
Ischemic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction