Related Experiment Video
Updated: Jul 16, 2026

Surgical Placement of Catheters for Long-term Cardiovascular Exercise Testing in Swine
Published on: February 9, 2016
The variability of cardiopulmonary adaptation to pregnancy at rest and during exercise
L Spätling1, F Fallenstein, A Huch
1Department of Obstetrics, University of Zurich, Switzerland.

Objective:
To examine the cardiopulmonary adaptation to normal pregnancy in sitting women during rest and bicycle exercise.
Design:
A longitudinal study beginning early in pregnancy and ending 8-12 months after delivery.
Setting:
University Hospital, Zurich, Switzerland.
Subjects:
20 women were monitored every second week during pregnancy from 8 to 14 weeks gestation, twice in the puerperium and twice 6-8 weeks and twice 8-12 months after delivery. All the women finished the study, but not all of them participated in every visit.
Measurements And Main Results:
The results obtained 8-12 months after delivery are considered the non-pregnant data and are presented first so that any change in pregnancy will be more obvious. Values given below refer to the median except when stated otherwise. At rest: 1. Oxygen consumption increased significantly from a median of 182 ml/min in the non-pregnant state to 256 ml/min by 8-11 weeks gestation, and peaked at 300 ml/min at 32 weeks. At 6-8 weeks after delivery the value was 225 ml/min. 2. Oxygen consumption per kg increased significantly from 3.0 ml/min in the non-pregnant state to 4.3 ml/min by 8-11 weeks gestation and peaked at 5.0 ml/min soon after delivery. At 6-8 weeks after delivery the value was 3.4 ml/min. 3. Carbon dioxide production generally showed changes similar to those of oxygen consumption. 4. Respiratory quotient did not show any significant changes. 5. Ventilation increased from a median of 9.4 l/min in the non-pregnant state to 10.5 l/min by 8-11 weeks and then slowly increased to 12.6 l/min in late pregnancy. 6. Respiratory rate did not change significantly. 7. Tidal volume showed a median of 563 ml in the non-pregnant women and rose significantly to 632 ml in early pregnancy, peaking at 715 ml in late pregnancy. 8. Alveolar ventilation increased significantly from a non-pregnant value of 3.4 l/min to 6.2 l/min in early pregnancy, peaking at 6.7 l/min at term; 6-8 weeks after delivery the value was 4.5 l/min. 9. Ventilation equivalent for oxygen fell significantly from the median non-pregnant value of 52 to 42 in early pregnancy and remained at that level until 6-8 weeks after delivery when it was 44. 10. Ventilation equivalent for carbon dioxide showed similar changes to those for oxygen. 11. Alveolar carbon dioxide tension fell significantly from a median non-pregnant level of 4.6 kPa (34 mmHg) to 4.0 kPa (30 mmHg) in early pregnancy. It began to increase in the puerperium and was 4.3 kPa (33 mmHg) 6-8 weeks after delivery. 12. Mixed venous carbon dioxide tension fell significantly from a median of 5.9 kPa (44 mmHg) to 5.2 kPa (39 mmHg) during pregnancy. 13. Transcutaneous carbon dioxide tension decreased significantly in early pregnancy from 8.8 kPa (66 mmHg) in the non-pregnant women, and from 20 weeks gestation remained at 6.9 kPa (52 mmHg). 14. Transcutaneous oxygen tension showed a non-significant increase from 10.0 kPa (75 mmHg) in the non-pregnant women to 11.1 kPa (83 mmHg) during pregnancy. 15. Cardiac frequency increased gradually from a non-pregnant median of 80 b.p.m. to about 90 b.p.m. in the last 2 months of pregnancy. In the puerperium the median was 75 b.p.m. 16. Cardiac output increased significantly by almost 50% from the non-pregnancy level to that at 8-11 weeks gestation. 17. Cardiac output per kg also increased significantly by 50% from the non-pregnant level to that at 8-11 weeks gestation. From mid-pregnancy there was a gradual fall until delivery. 18. Stroke volume increased significantly from a median of 31 ml in the non-pregnant state to 51 ml in early pregnancy, and remained at this level until delivery. In the puerperium the stroke volume was 63 ml. 19. Oxygen pulse increased significantly from a median of 2.2 ml in the non-pregnant women to 3.1 ml in early pregnancy and remained at that level. 20. Individual curves.(ABSTRACT TRUNCATED AT 400 WORDS)
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Related Concept Videos
 01:24
Factors Affecting Respiration
 01:29
Pathophysiology of Cardiac Performance
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:19
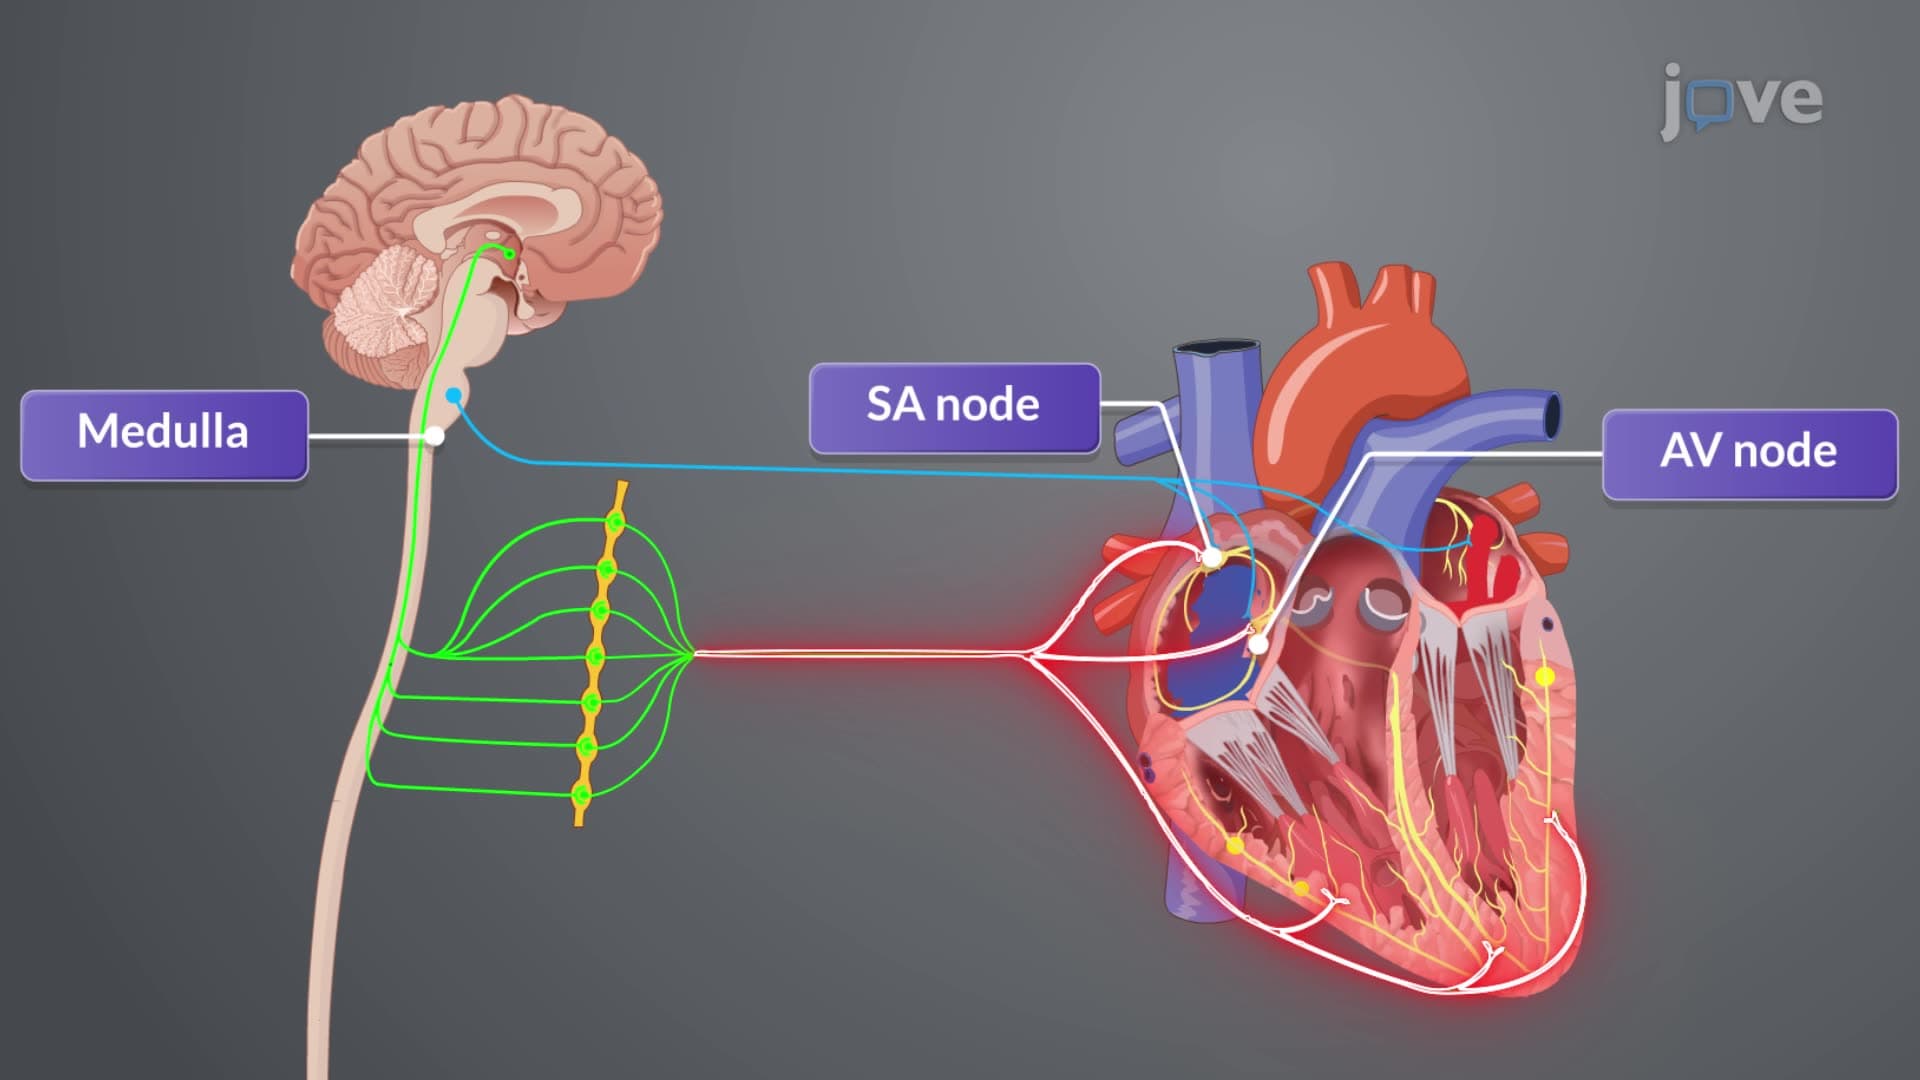
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...