Related Experiment Video
Updated: Aug 24, 2026
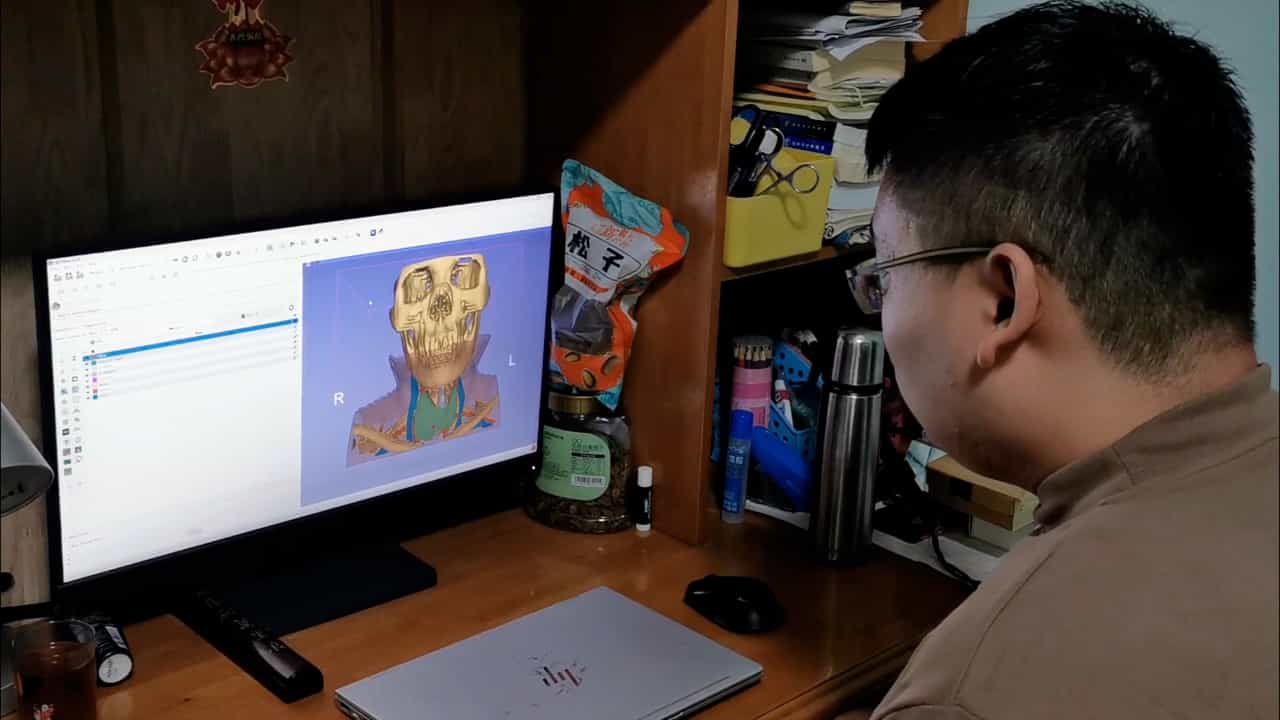

Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
Postpartum thyroiditis
1UMDNJ-New Jersey Medical School, Division of Endocrinology and Metabolism, Department of Medicine, 185 South Orange Avenue, MSB C-652, Newark, NJ 07103, USA. stagnaas@umdnj.edu

Postpartum thyroiditis (PPT) is the occurrence, in the postpartum period, of transient hyperthyroidism and/or transient hypothyroidism, with most women returning to the euthyroid state by 1 year postpartum. The prevalence of PPT varies from 1.1 to 16.7%, with a mean prevalence of 7.5%. Women with type I diabetes mellitus have a three-fold increase in the prevalence of PPT. PPT is an autoimmune disorder which is a transient form of Hashimoto's thyroiditis occurring postpartum as a consequence of the immunologic flare following the immune suppression of pregnancy. Women experience symptoms in both the hyperthyroid and hypothyroid phase, but the association between PPT and postpartum depression remains undefined. Approximately 25% of women with a history of PPT will develop permanent hypothyroidism in the ensuing 10 years. Treatment for the hyperthyroid phase, when required, is a short dose of beta-blockers. Women with a TSH greater than 10 mU/l, or between 4 and 10 mU/l with symptoms or attempting pregnancy, require thyroid hormone replacement. Whether or not to screen for PPT remains controversial.
Postpartum thyroiditis (PPT) is the occurrence, in the postpartum period, of transient hyperthyroidism and/or transient hypothyroidism, with most women returning to the euthyroid state by 1 year postpartum. The prevalence of PPT varies from 1.1 to 16.7%, with a mean prevalence of 7.5%. Women with type I diabetes mellitus have a three-fold increase in the prevalence of PPT. PPT is an autoimmune disorder which is a transient form of Hashimoto's thyroiditis occurring postpartum as a consequence of the immunologic flare following the immune suppression of pregnancy. Women experience symptoms in both the hyperthyroid and hypothyroid phase, but the association between PPT and postpartum depression remains undefined. Approximately 25% of women with a history of PPT will develop permanent hypothyroidism in the ensuing 10 years. Treatment for the hyperthyroid phase, when required, is a short dose of beta-blockers. Women with a TSH greater than 10 mU/l, or between 4 and 10 mU/l with symptoms or attempting pregnancy, require thyroid hormone replacement. Whether or not to screen for PPT remains controversial.
Related Concept Videos
 01:24
Graves Disease II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:23
Hypothyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...