Related Experiment Video
Updated: Aug 24, 2026


Basophil Activation Test for Allergy Diagnosis
Published on: May 31, 2021
Cefazolin tolerance does not predict ceftriaxone hypersensitivity: unique side chains precipitate anaphylaxis
Sara A Poston1, Heath R Jennings, Kevin L Poe
1College of Pharmacy, University of Kentucky, Lexington, Kentucky, USA.

A 48-year-old woman with a questionable history of an unspecified ceftriaxone allergy was treated with cefazolin for surgical antibiotic prophylaxis. After she tolerated cefazolin therapy for 4 days, the medical staff concluded that her allergy history was inaccurate, and she was treated with intravenous ceftriaxone for suspected nosocomial pneumonia. Approximately 10 minutes after the start of the infusion, the patient experienced anaphylaxis. Initial symptoms of oral angioedema and laryngopharyngeal constriction progressed to dyspnea, tachypnea, hypotension, and tachycardia, all of which quickly resolved after immediate treatment with hydrocortisone, diphenhydramine, and epinephrine. Skin testing with cefazolin, cefepime, and ceftriaxone revealed that the likely allergic determinant mediating the patient's hypersensitivity reaction was the unique ceftriaxone R2 side chain and not the beta-lactam ring, which initially was suspected by the physician. Immunoglobulin E-mediated hypersensitivity reactions to cephalosporins may occur due to antibody complexes with the beta-lactam ring or various cephalosporin side chains. Misconceptions regarding the nature of cephalosporin allergies complicate antibiotic selection for patients with questionable allergy histories and may lead to inappropriate drug reexposure and anaphylaxis. Detailed understanding of the antigenic determinants that mediate hypersensitivity reactions is essential for clinicians to avoid type 1 reactions in patients with a suspected allergy to cephalosporins.
A 48-year-old woman with a questionable history of an unspecified ceftriaxone allergy was treated with cefazolin for surgical antibiotic prophylaxis. After she tolerated cefazolin therapy for 4 days, the medical staff concluded that her allergy history was inaccurate, and she was treated with intravenous ceftriaxone for suspected nosocomial pneumonia. Approximately 10 minutes after the start of the infusion, the patient experienced anaphylaxis. Initial symptoms of oral angioedema and laryngopharyngeal constriction progressed to dyspnea, tachypnea, hypotension, and tachycardia, all of which quickly resolved after immediate treatment with hydrocortisone, diphenhydramine, and epinephrine. Skin testing with cefazolin, cefepime, and ceftriaxone revealed that the likely allergic determinant mediating the patient's hypersensitivity reaction was the unique ceftriaxone R2 side chain and not the beta-lactam ring, which initially was suspected by the physician. Immunoglobulin E-mediated hypersensitivity reactions to cephalosporins may occur due to antibody complexes with the beta-lactam ring or various cephalosporin side chains. Misconceptions regarding the nature of cephalosporin allergies complicate antibiotic selection for patients with questionable allergy histories and may lead to inappropriate drug reexposure and anaphylaxis. Detailed understanding of the antigenic determinants that mediate hypersensitivity reactions is essential for clinicians to avoid type 1 reactions in patients with a suspected allergy to cephalosporins.

Related Concept Videos
 01:16
Drug toxicity: Idiosyncratic Reactions
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:20
Desensitization and Tachyphylaxis
Several...
 01:28
Inhibitors of Bacterial DNA Synthesis
 01:30
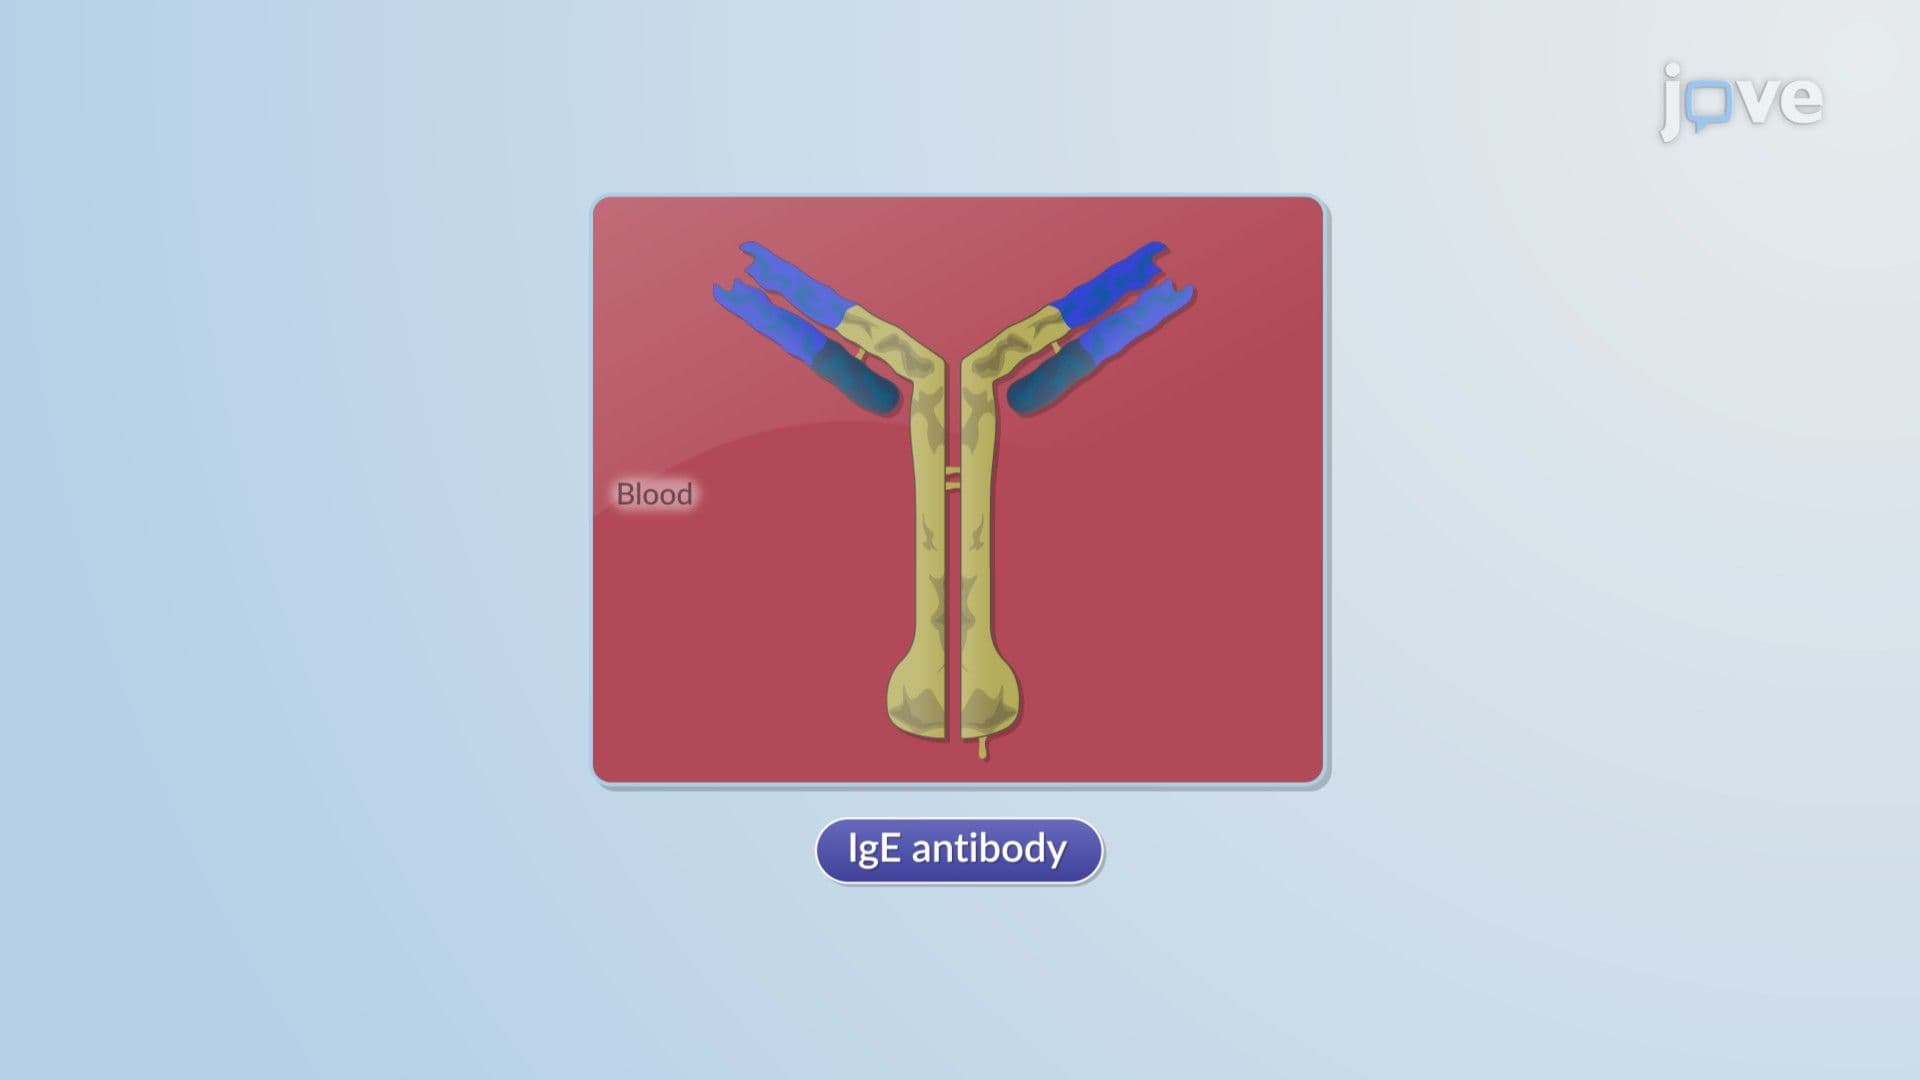
Allergic Reactions: Anaphylaxis
 01:30
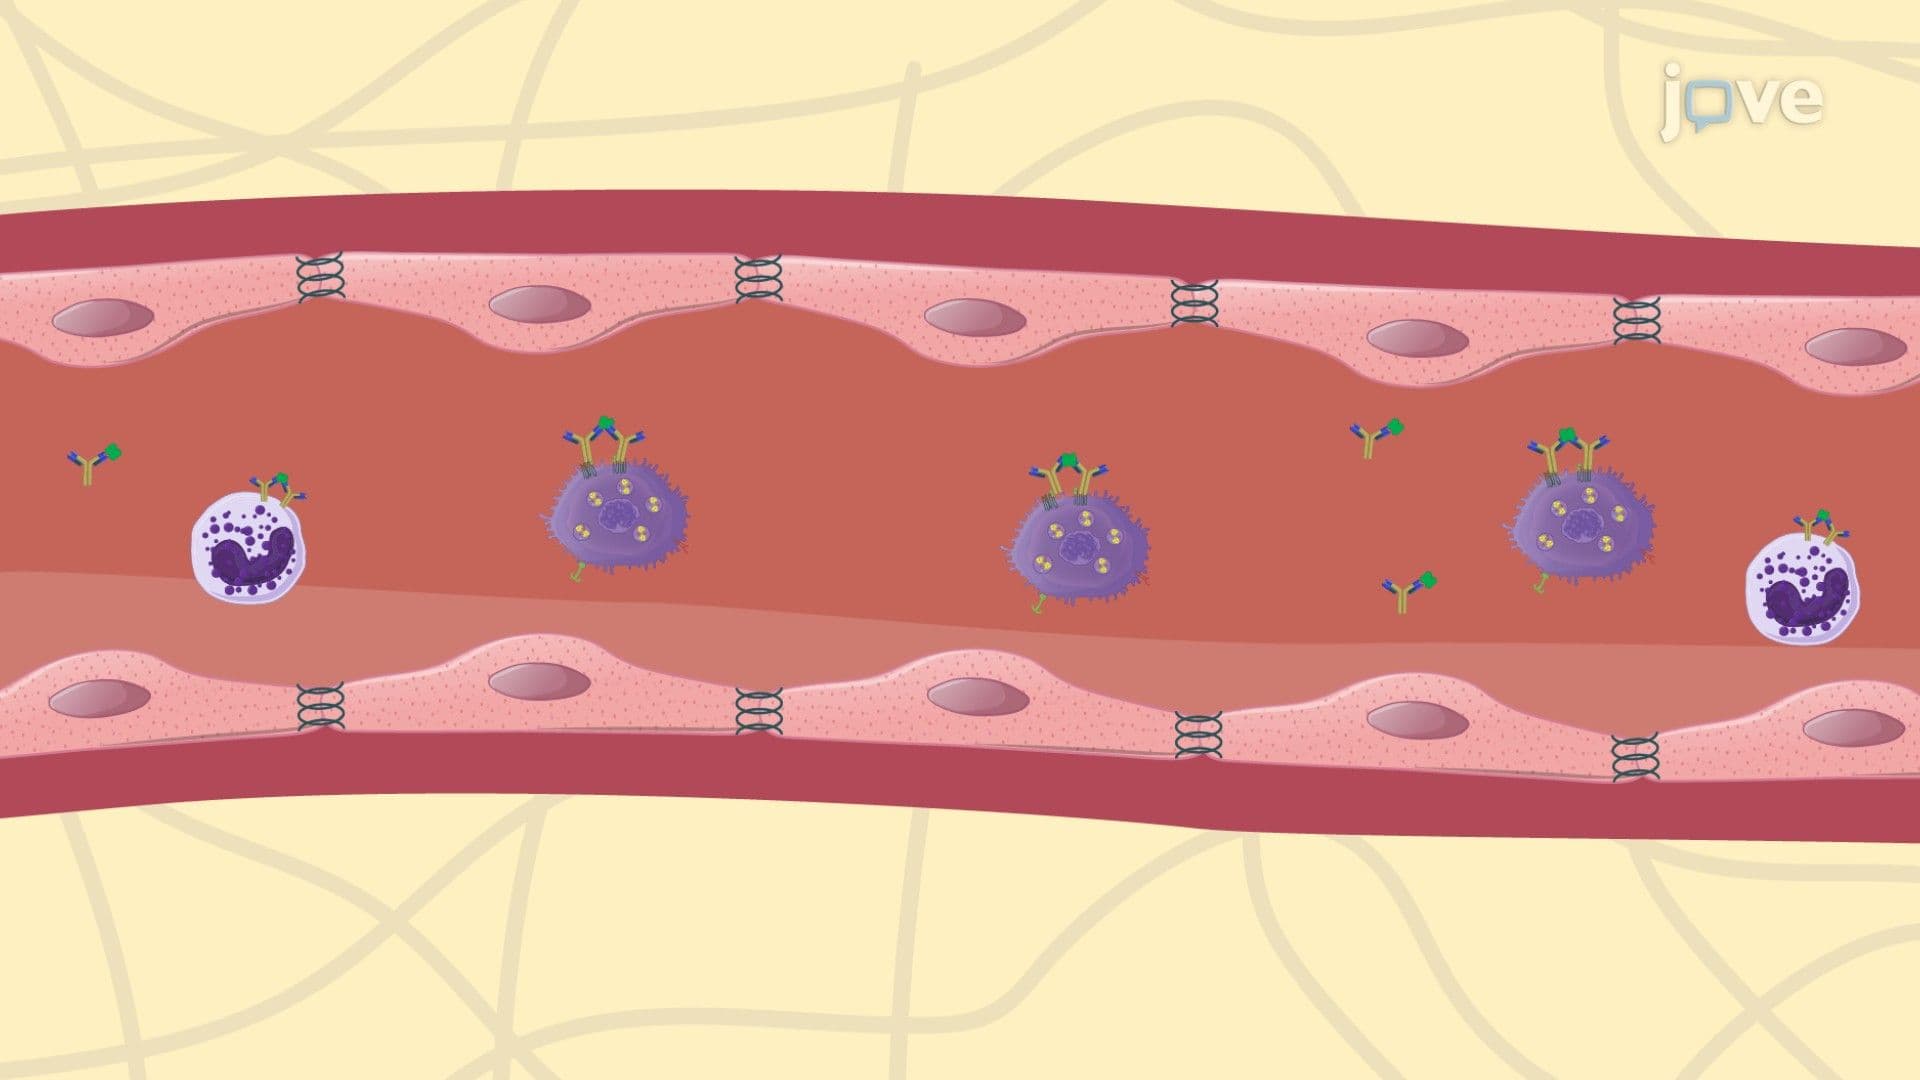
Drug Toxicity: Allergic Reactions