Related Experiment Video
Updated: Aug 24, 2026
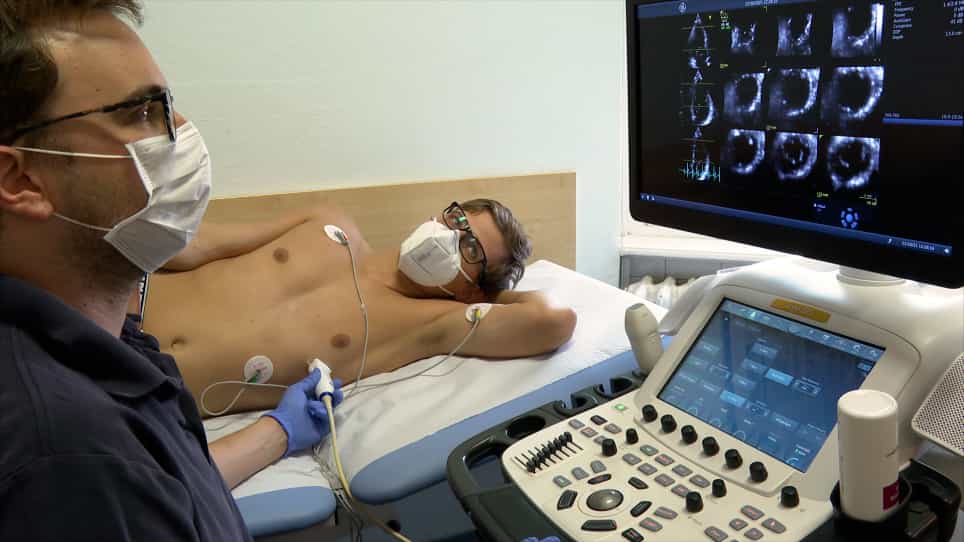

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Are there sex differences in regional systolic function and wall stress in hypertrophic obstructive cardiomyopathy? A
Jürgen Frielingsdorf1, Andreas Franke, Otto M Hess
1Cardiology, Department of Medicine, City Hospital Triemli, Zurich, Switzerland.

Insights
Women exhibit superior left ventricular (LV) systolic function in hypertrophic obstructive cardiomyopathy. However, this difference in LV systolic function disappears when adjusted for lower wall stress in women.
Area of Science:
- Cardiology
- Cardiovascular Imaging
- Echocardiography
Background:
- Sex-related differences in left ventricular (LV) systolic function are documented in aortic stenosis and hypertensive heart disease.
- Regional LV systolic function is influenced by wall thickness and wall stress.
- Comprehensive analysis of regional LV function requires advanced imaging techniques.
Purpose of the Study:
- To determine LV systolic function in male and female patients with hypertrophic obstructive cardiomyopathy.
- To investigate the relationship between LV systolic function, wall thickness, and wall stress in this patient population.
- To explore potential sex-based disparities in cardiac mechanics.
Main Methods:
- Utilized multiplane transesophageal echocardiography with 3D reconstruction of the LV in 21 patients (11 men, 10 women).
- Acquired 4 parallel short-axis cross-sections from base to apex, with 24 wall-thickness measurements per section at end-diastole and end-systole.
- Calculated wall thickening and fractional thickening to assess regional systolic function.
Main Results:
- Fractional thickening and wall stress were inversely related to end-diastolic wall thickness in both sexes.
- Women demonstrated significantly better LV systolic function compared to men (P <.001).
- After correcting for lower wall stress in women, no significant sex difference in systolic function was observed.
Conclusions:
- Regional differences in LV systolic function exist between men and women with hypertrophic obstructive cardiomyopathy.
- These differences are contingent upon regional wall thickness and associated wall stress.
- Wall stress is a critical factor in understanding sex-related variations in cardiac function.
Objectives:
Sex-related differences in left ventricular (LV) systolic function have been previously reported in patients with aortic stenosis and hypertensive heart disease. The goal of this study was to determine systolic function of the LV in male and female patients with hypertrophic obstructive cardiomyopathy and to relate it to wall thickness and wall stress, respectively.
Background:
Wall thickening, a parameter of regional systolic function, is determined by wall thickness and wall stress. A comprehensive analysis of regional LV function was performed from multiplane transesophageal echocardiography with 3-dimensional reconstruction of the LV.
Methods:
In 21 patients (11 men and 10 women) 4 parallel (2 basal and 2 apical) equidistant short-axis cross sections from base to apex were obtained from the reconstructed LV. In each short axis, 24 wall-thickness measurements were carried out in 15-degree intervals at end-diastole (ED) and end-systole. Thus, a total of 192 measurements were obtained in each patient. Wall thickening, a parameter of regional systolic function, was calculated as the difference of ED and end-systolic wall thickness, and fractional thickening as thickening divided by ED thickness.
Results:
Fractional thickening and wall stress were inversely related to ED wall thickness in both men and women. Women showed better LV systolic function when compared with men (P <.001). However, when corrected for wall stress, which was lower in women, there was no sex difference in systolic function.
Conclusions:
There are regional differences in LV systolic function in men and women that depend on regional wall thickness and wall stress.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
Heart Failure II: Pathophysiology