Related Experiment Video
Updated: Jul 13, 2026
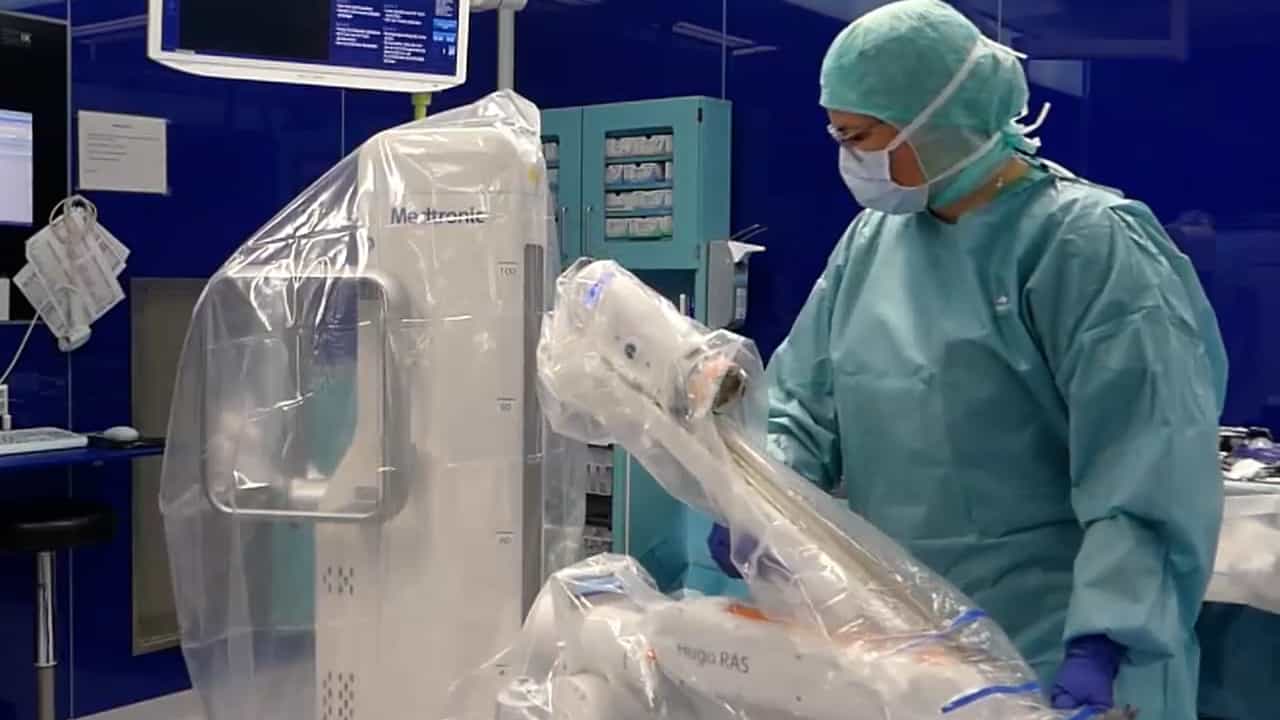

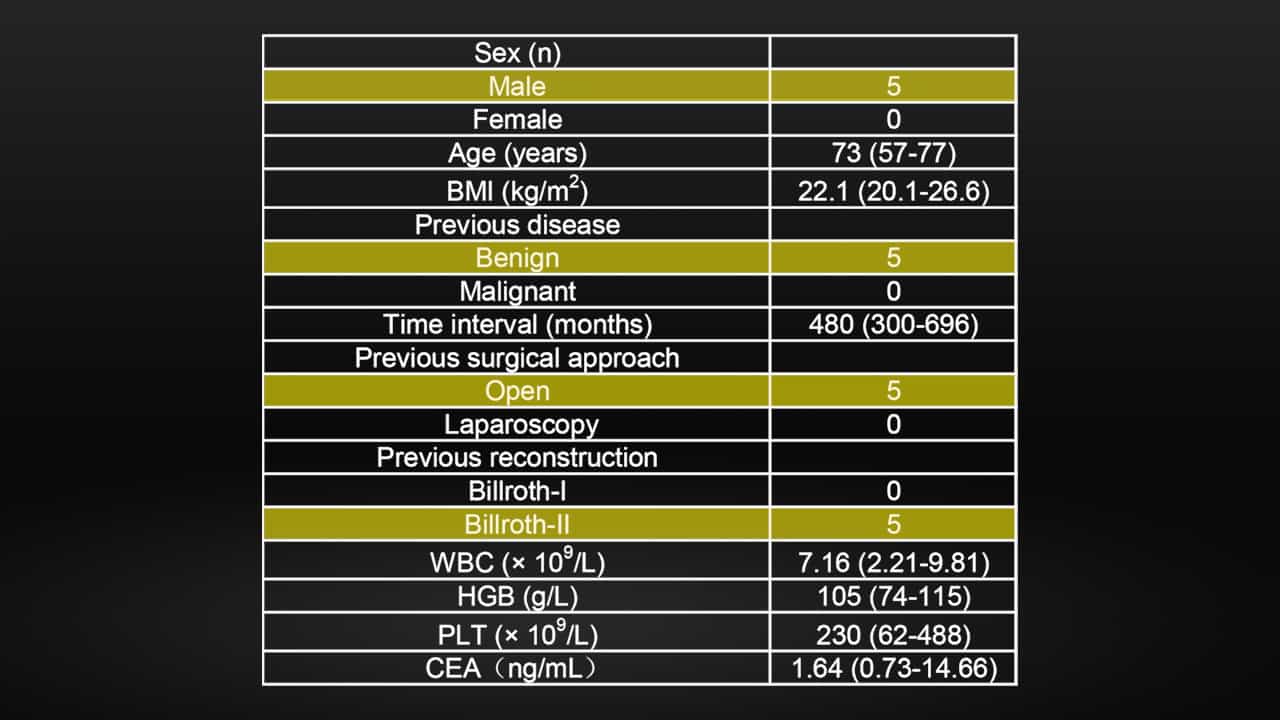
Robotics in Surgery: A Modular Robotic Platform Driven Gastric Wedge Resection
Published on: February 7, 2025
Re-organizing services for the management of upper gastrointestinal cancers: patterns of care and problems with
1Health Impact Assessment Research Unit, Department of Public Health & Epidemiology, University of Birmingham, Edgbaston, Birmingham, UK. j.m.parry@bham.ac.uk

Abstract:
The 'Calman-Hine' report (1995) recommended that cancer surgery should be limited to specialist high-volume units. National guidance from the National Health Service (NHS) Executive in 2001 stated that specialist oesophagogastric cancer centres should 'aim to draw patients from catchment areas with a population of 1-2 million.' For pancreatic cancers, the catchment areas should be between 2 and 4 million, reflecting the relatively lower incidence of disease. For the West Midlands region, these recommendations would suggest that four or five centres might be required to provide specialist surgical management for oesophagogastric cancer, and one or two centres for pancreatic disease. We used Hospital Episode Statistics to analyse trends in management patterns for these tumours within the West Midlands during the period 1992-2000. Over 20 different units were involved in the management of oesophagogastric and pancreatic disease, and we were unable to discern any clear and consistent move towards the centralisation of the upper gastrointestinal work in high-volume units since the publication of the Calman-Hine report in 1995. Although the drive for centralisation might be anticipated to increase following the publication of the NHS Executive's guidance, there is a substantial way to go before the provision of surgical services for upper gastrointestinal cancers is limited to a small number of high-volume specialist units.
Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease