Related Experiment Video
Updated: Aug 24, 2026

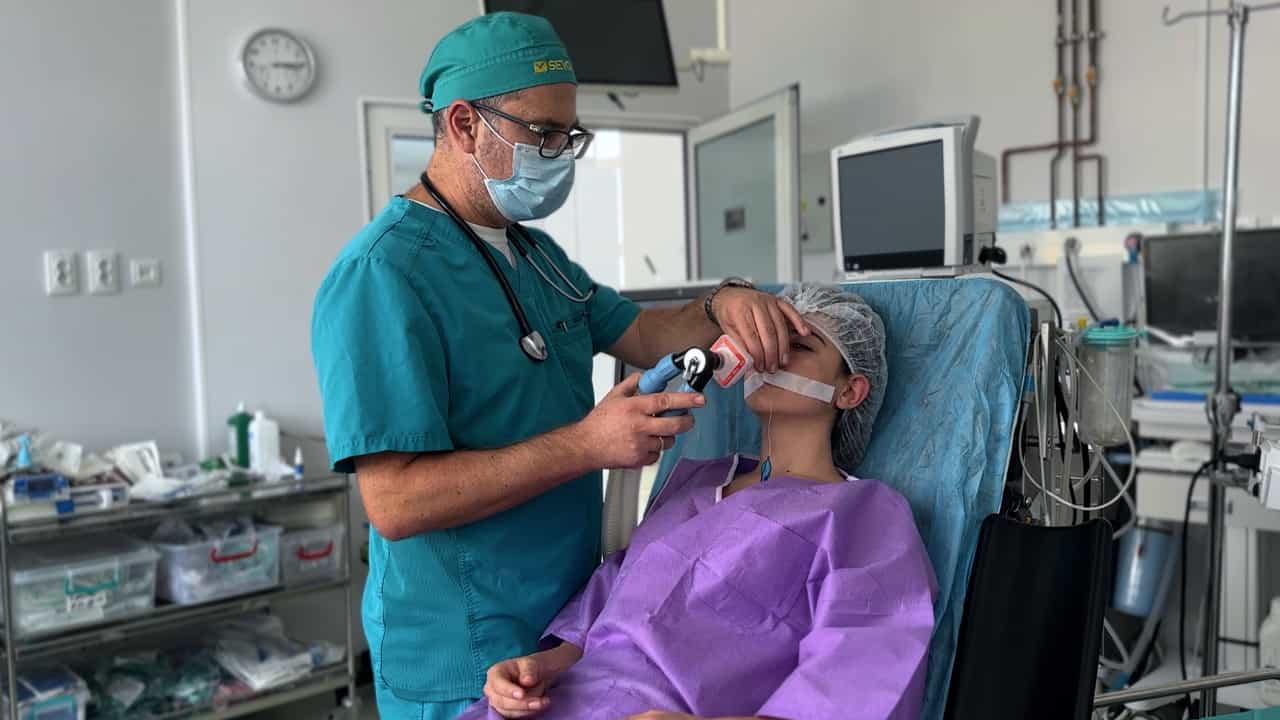
Image Acquisition using Portable Sonography for Emergency Airway Management
Published on: September 28, 2022
Intubation alone does not mandate trauma surgeon presence on patient arrival to the emergency department
David J Ciesla1, Ernest E Moore, John B Moore
1Denver Health Medical Center and the University of Colorado Health Sciences Center, Denver, Colorado, USA.

Background:
Current American College of Surgeons Committee on Trauma criteria for major resuscitation include prehospital respiratory compromise or obstruction and/or intubation and mandate an attending trauma surgeon's presence on patient's arrival to the emergency department (ED). A substantial number of trauma patients arrive intubated, with no other physiologic compromise. We hypothesized that field or ED intubation in the absence of other major criteria does not require trauma surgeon presence on patient arrival.
Methods:
Data were collected from our trauma registry on all injured patients intubated in the field or on arrival to the ED over a 30-month period ending in June 2003. Patients meeting other American College of Surgeons Committee on Trauma criteria (systolic blood pressure < 90 mm Hg; gunshot wound to the neck, chest, or abdomen; and unstable patient transfers) were excluded.
Results:
During this period, 7,645 trauma patients were admitted to the ED; 834 were intubated, of whom 489 (59%) had no other criteria for major resuscitation. One was pronounced dead, 6 were admitted to the ward, 415 (85%) were admitted to the intensive care unit, and 67 (14%) were transferred directly to the operating room. Twenty-two (4%) required nonorthopedic or nonneurosurgical procedures, 11 (2%) of which were for hemorrhage control. Twelve of 16 stab wounds (75%) required emergent operation, 7 (44%) of which were for hemorrhage control. In contrast, 8 (3%) of 244 motor vehicle crashes required emergent operation, 4 (2%) of which were for hemorrhage control.
Conclusion:
Intubated patients with central stab wounds represent a high-risk group and should mandate trauma surgeon presence on patient arrival. Excluding stab wounds, field or ED intubation alone rarely requires emergent surgical decision-making. Therefore, field or ED intubation alone should not mandate trauma surgeon presence on patient arrival.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: