Related Experiment Video
Updated: Aug 24, 2026

Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Surgical strategy for hepatocellular carcinoma originating in the caudate lobe
Takatsugu Yamamoto1, Shoji Kubo, Taichi Shuto
1Gastroenterological and Hepato-Biliary-Pancreatic Surgery, Osaka City University Graduate School of Medicine, Japan.

Background:
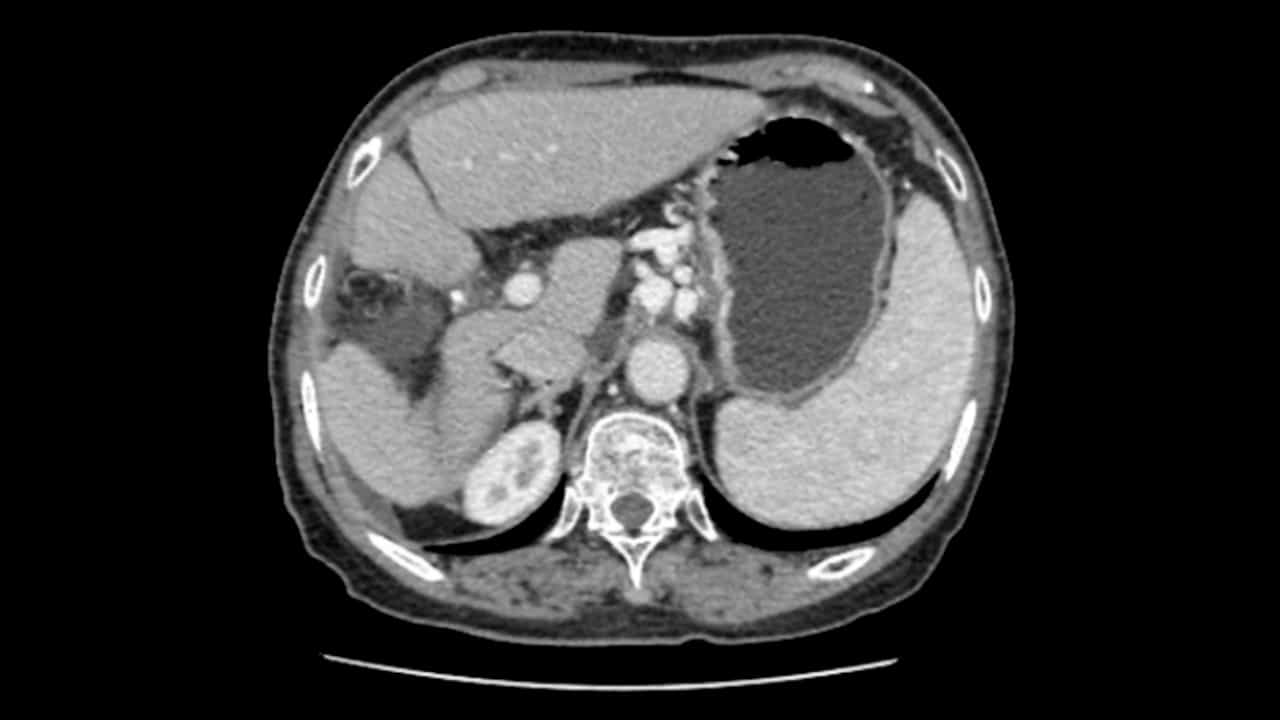
The prognosis of hepatocellular carcinoma originating in or mainly involving the caudate lobe (caudate HCC) is generally poor. We reviewed the clinicopathologic findings of patients who underwent liver resection of caudate HCC and correlated the outcome with the surgical strategy.
Methods:
Records of 402 patients who underwent liver resection for HCC were reviewed. The patients were divided into 2 groups. One group consisted of 15 patients who underwent liver resection for caudate HCC. The other group included 387 patients with HCC in a site other than the caudate lobe.
Results:
Anatomic resection of Couinaud segment I or IX (a partial caudate lobectomy), conforming to portal anatomy, was performed in 13 patients with caudate HCC, and segmentectomies of segments I and IX (a total caudate lobectomy) were performed in 2 patients with caudate HCC. The incidence of postoperative complications was similar in the caudate HCC group and HCC in other sites group, with no operative deaths in the caudate HCC group. Tumor-free survival and cumulative survival were similar in the 2 groups. However, among patients with caudate HCC, tumor-free and cumulative survival were lower in patients with than without microscopic portal venous involvement (P<.01).
Conclusions:
Partial caudate lobectomy (anatomic resection of segment I or IX) along the portal system is an appropriate procedure for caudate HCC, especially in patients with impaired liver function or a small HCC. Patients with caudate HCC who have microscopic portal venous involvement may require adjuvant therapy as early recurrence is likely.