Related Experiment Video
Updated: Aug 24, 2026

Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Posterior urethral valves in Eastern Ontario - a 30 year perspective
Jeff Warren1, John G Pike, Michael P Leonard
1Division of Pediatric Urology, Children's Hospital of Eastern Ontario, University of Ottawa, Ontario, Canada.

Insights
Posterior urethral valves (PUV) are often diagnosed prenatally, but many cases still present postnatally. Long-term bladder and kidney dysfunction are common, requiring ongoing urological and nephrological care.
Area of Science:
- Pediatric Urology
- Nephrology
- Medical Imaging
Background:
- Posterior urethral valves (PUV) represent the primary cause of obstructive uropathy in male pediatric patients.
- Antenatal ultrasound and endoscopic advancements have significantly influenced the diagnosis and management of PUV.
- This study examines the clinical evolution of PUV over three decades in Eastern Ontario/Western Quebec.
Purpose of the Study:
- To describe the presentation, management, and outcomes of patients with PUV.
- To compare cases diagnosed before and after the widespread adoption of antenatal ultrasound screening.
- To identify trends in clinical presentation and long-term outcomes.
Main Methods:
- A retrospective chart review of 53 PUV cases treated at the Children's Hospital of Eastern Ontario over 30 years.
- Patients were divided into pre- and post-antenatal ultrasound detection eras for comparative analysis.
- Data collected included initial presentation, diagnostic methods, clinical findings, management, and long-term outcomes.
Main Results:
- 32% of PUV cases were detected via prenatal ultrasound, with none prior to 1985.
- 49% of patients had documented vesicoureteral reflux (VUR), and 79% showed hydronephrosis.
- Long-term complications included bladder dysfunction (31%) and impaired renal function (23%), with 11% progressing to end-stage renal disease (ESRD).
Conclusions:
- Antenatal detection is increasingly common but not the majority of PUV diagnoses.
- Comprehensive workup requires ultrasound and voiding cystourethrogram (VCUG); VUR necessitates antibiotic prophylaxis.
- Valve ablation is the primary treatment, but long-term bladder and renal dysfunction necessitate continuous urological and nephrological follow-up.
Introduction:
Posterior urethral valves (PUV) are the most common cause of male pediatric obstructive uropathy. Recent advancements in antenatal ultrasound and endoscopy have altered the presentation and management of PUV. Herein we describe the presentation, management and outcome of PUV patients in Eastern Ontario/Western Quebec over the last 3 decades. A comparison analysis of those cases identified pre and post widespread utilization of antenatal ultrasound diagnosis was performed to discern the clinical evolution of PUV with respect to long-term outcome.
Methods:
Retrospective systematic chart review of all PUV cases diagnosed and treated at the Children's Hospital of Eastern Ontario over the last 3 decades. Charts were reviewed for initial presentation, method of diagnosis, radiological and clinical findings at diagnosis, initial management, and long-term clinical outcome. The evolution of PUV was interpreted by dividing the cohort into two groups chronologically delineated by the first case detected by antenatal ultrasound in the mid-1980s. These pre- and post- antenatal ultrasound eras were compared with respect to the parameters outlined above.
Results:
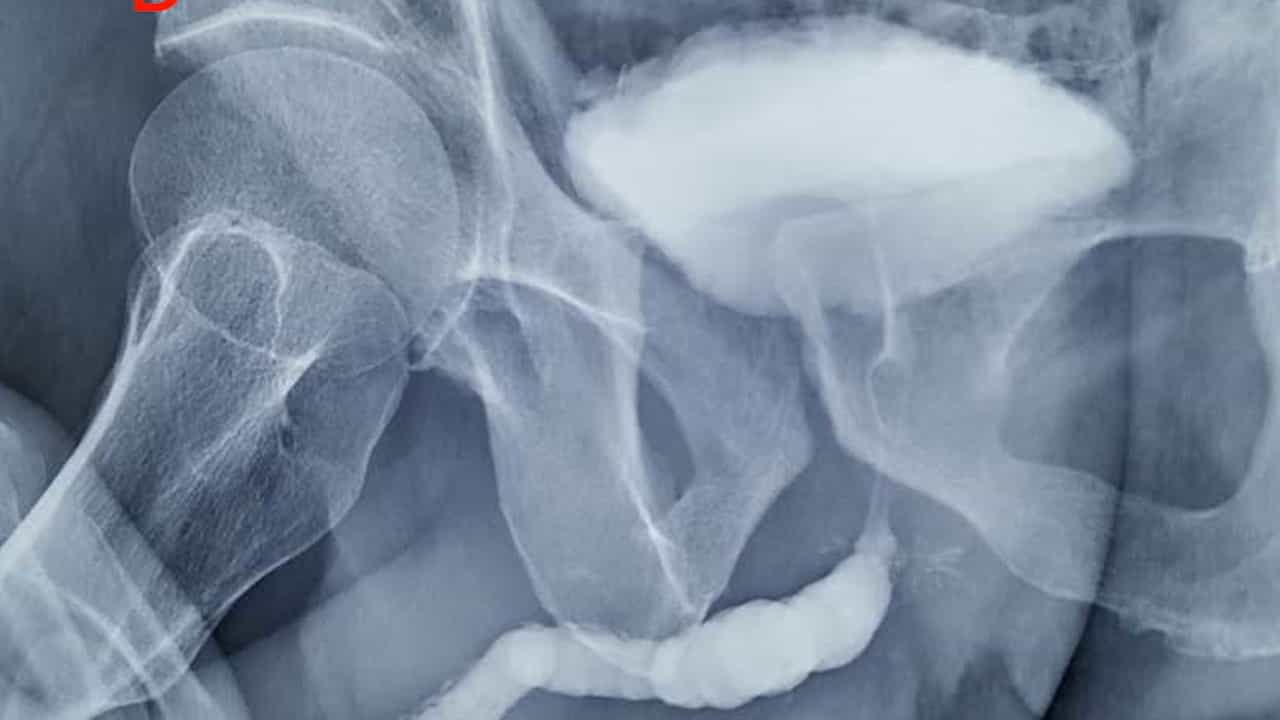
Fifty-three cases were reviewed - 21 prior to widespread antenatal ultrasound screening in the mid-1980s and 32 after. There were 13/53 cases (32%) discovered by prenatal ultrasound evidence of hydronephrosis, none prior to 1985. VCUG confirmed the diagnosis in all cases. Mean age at presentation in the remaining post-natally diagnosed patients was 33 months. Of the cases diagnosed post-natally, ultrasound investigation complemented VCUG findings in 19/40 cases (47%), whereas IVP was utilized in 14/40 (35%). IVP has not been utilized for this purpose since 1987. Overall, 26/53 cases (49%) had documented VUR - 16/26 (62%) bilateral; 42/53 (79%) had hydronephrosis on ultrasound - 37/42 (88%) bilateral; 26/53 (49%) had radiological evidence of renal parenchymal damage at diagnosis; 41/53 (77%) cases had a thickened bladder wall on ultrasound at diagnosis, and 23/53 (43%) had at least one bladder diverticulum. Techniques of initial management comprised: valve ablation 32/53, vesicostomy 11/53, and high diversion 10/53. Clinically significant bladder dysfunction was found in 31% of cases, ranging from bladder instability to myogenic failure. Globally impaired renal function, as determined by significantly elevated serum creatinine levels, reduced GFR, or both, was found in 12/53 (23%). 6/53 (11%) progressed to ESRD, of which 4 received transplants. Two patients died - one from complications related to renal failure. Of the six cases of myogenic bladder failure identified, three (50%) had concurrently significant renal impairment. Average length of follow-up was 8.3 years, varying between 1 month and 18 years.
Conclusions:
The presentation of PUV is variable, and currently antenatal detection is the most common mode. Despite this, it still does not make up the majority of diagnoses. Complete radiological work up should include abdominal and pelvic U/S in conjunction with VCUG. Concurrent VUR in 50% of boys mandates suppressive antibiotic use. Primary valve ablation remains the gold standard for treatment of PUV, with vesicostomy reserved for selected cases. Long-term bladder and renal dysfunction is common in this population, and mandates long-term urological and nephrological follow-up.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 05:09
Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
Related Concept Videos
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:28
Urinary Tract Calculi I: Introduction
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:22
Ureters
 01:28
Urinary Tract Calculi V: Nursing Management