Related Experiment Video
Updated: Aug 24, 2026
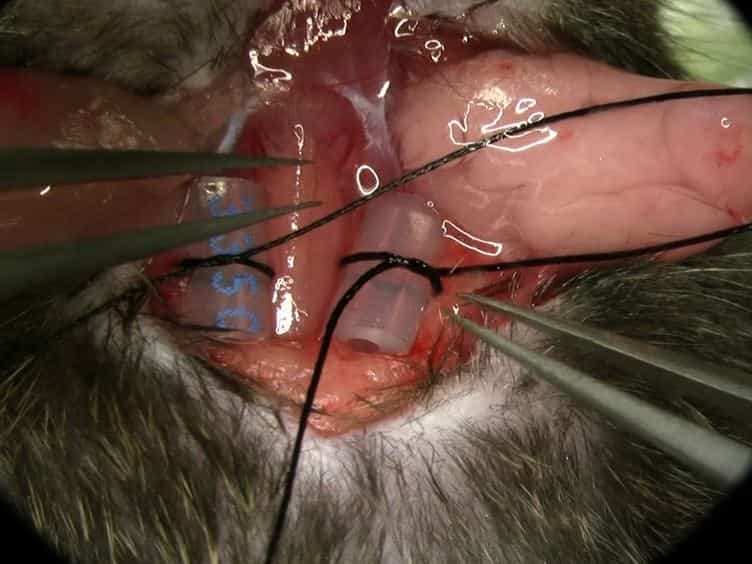

Bilateral Common Carotid Artery Occlusion as an Adequate Preconditioning Stimulus to Induce Early Ischemic Tolerance to Focal Cerebral Ischemia
Published on: May 9, 2013
[How to use the paradigm of ischemic preconditioning to protect the heart?]
1Inserm E0226 et Hôpital L. Pradel, Laboratoire de physiologie Lyon-Nord, 8, avenue Rockefeller, 69008 Lyon, France.

Abstract:
Ischemic preconditioning affords the most powerful protection to a heart submitted to a prolonged ischemia-reperfusion. During the past decade, a huge amount of work allowed to better understand the features of this protective effect as well as the molecular mechanisms. Ischemic preconditioning reduces infarct size and improves functional recovery; its effects on arrhythmias remain debated. Triggering of the protection involves cell surface receptors that activate pro-survival pathways including protein kinase C, PI3-kinase, possibly Akt and ERK1/2, whose downstream targets remain to be determined. Much attention has been recently focused on the role of mitochondrial K(+)ATP channels and the permeability transition pore that seem to play a major role in the progression toward irreversible cellular injury. Based on these experimental studies attempts have been made to transfer preconditioning from bench to bedside. Human experimental models of ischemic preconditioning have been set up, including cardiac surgery, coronary angioplasty or treadmill exercise, to perform pathophysiological studies. Yet, protecting the heart of CAD (coronary artery disease) patients requires a pharmacological approach. The IONA trial has been an example of the clinical utility of preconditioning. It helped to demonstrate that chronic administration of nicorandil, a K(+)ATP opener that mimics ischemic preconditioning in experimental preparations, improves the cardiovascular prognosis in CAD patients. Recent experimental studies appear further encouraging. It appears that "postconditioning" the heart (i.e. performing brief episodes of ischemia-reperfusion at the time of reperfusion) is as protective as preconditioning. In other words, a therapeutic intervention performed as late as at the time of reflow can still significantly limit infarct size. Further work is needed to determine whether this may be transferred to the clinical practice.


Related Concept Videos
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:15
Ischemic Stroke ll: Pathophysiology