Related Experiment Video
Updated: Aug 23, 2026
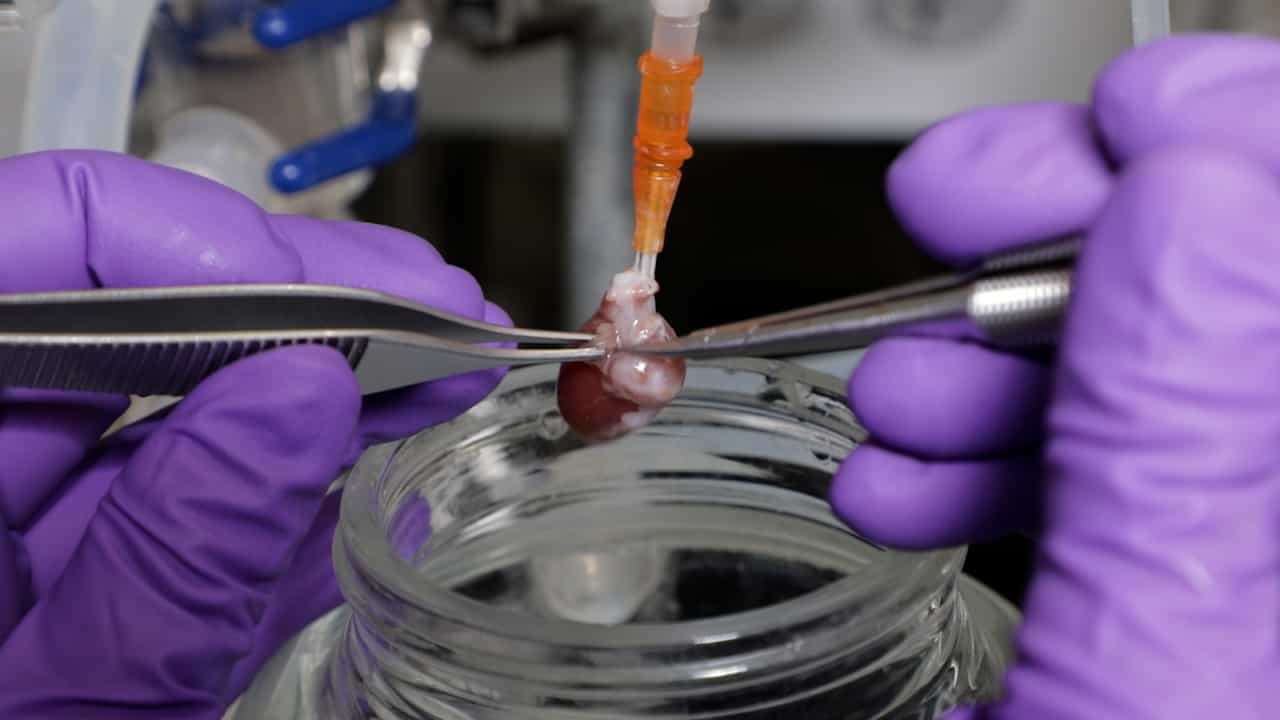

Modified Langendorff Perfusion for Extended Perfusion Times of Rodent Cardiac Grafts
Published on: June 14, 2024
Coronary grafts flow and cardiac pacing modalities: how to improve perioperative myocardial perfusion
Giuseppe D'Ancona1, Martin Hargrove, John Hinchion
1Department of Cardiac Surgery, Cork University Hospital, Cork, Ireland. rgea@hotmail.com

Insights
Dual chamber pacing (DDD) optimizes coronary graft flow after coronary artery bypass grafting (CABG) compared to ventricular pacing (VVI). Optimal results were seen with an atrio-ventricular delay of 175 ms, enhancing myocardial perfusion.
Area of Science:
- Cardiovascular Surgery
- Cardiac Electrophysiology
- Hemodynamics
Background:
- Coronary artery bypass grafting (CABG) is a common surgical procedure to restore blood flow to the heart muscle.
- Post-operative cardiac pacing is sometimes required to manage heart rhythm disturbances after CABG.
- Optimizing graft flow is crucial for successful myocardial reperfusion and patient recovery.
Purpose of the Study:
- To investigate the impact of different cardiac pacing modalities on coronary graft blood flow following CABG.
- To determine the optimal atrio-ventricular (A-V) delay during dual-chamber pacing for maximizing graft perfusion.
Main Methods:
- Prospective studies involving patients undergoing CABG who required intraoperative epicardial pacing.
- Coronary graft blood flow was measured using a transit-time flowmeter.
- Flow measurements were compared between dual-chamber pacing (DDD) and ventricular pacing (VVI) modes.
- In a separate cohort, graft flow was assessed during DDD pacing with varying A-V delay intervals (25 ms increments from 25 to 250 ms).
Main Results:
- Coronary graft flow was significantly higher during DDD pacing (47.4 ml/min) compared to VVI pacing (41.8 ml/min) (P = 0.0004).
- Systolic blood pressure was also significantly higher during DDD pacing.
- Maximal graft flow was observed during DDD pacing with an A-V delay of 175 ms (54 ml/min), while minimal flow occurred at 25 ms A-V delay.
Conclusions:
- Graft flowmetry is a valuable tool for guiding post-CABG supportive measures, including cardiac pacing.
- Dual-chamber pacing (DDD) mode is superior to ventricular pacing (VVI) for enhancing coronary graft perfusion.
- An atrio-ventricular delay of approximately 175 ms during DDD pacing should be preferred to maximize myocardial perfusion through coronary grafts.
Objective:
Aim of this study was to investigate modifications of coronary grafts flow during different pacing modalities after CABG.
Materials And Methods:
Two separate prospective studies were conducted in patients undergoing CABG and requiring intraoperative epicardial pacing. In a first study (22 patients) coronary grafts flows were measured during dual chamber pacing (DDD) and during ventricular pacing (VVI). In a second study (10 patients) flows were measured during DDD pacing at different atrio-ventricular (A-V) delay periods. A-V delay was adjusted in 25 ms increments from 25 to 250 ms and flow measurements were performed for each A-V delay increment. A transit time flowmeter was used for the measurements.
Results:
An average of 3.4 grafts/patient were performed. In the first study, average coronary graft flow was 47.4+/-20.8 ml/min during DDD pacing and 41.8+/-18.2 ml/min during VVI pacing (P = 0.0004). Furthermore average systolic pressure was 94.3+/-10.1 mmHg during DDD pacing and 89.6+/-12.2 mmHg during VVV pacing (P = 0.0007). No significant differences in diastolic pressure were recorded during the two different pacing modalities. In the second study, maximal flows were achieved during DDD pacing with an A-V delay of 175 ms (54+/-9.6 ml/min) and minimal flows were detected at 25 ms A-V delay (38.1+/-4.7 ml/min) (P=ns). No significant differences in systolic or diastolic blood pressure were noticed during the different A-V delays.
Conclusion:
Grafts flowmetry provides an extra tool to direct supportive measures such as cardiac pacing after CABG. DDD mode with A-V delay around 175 ms. should be preferred to allow for maximal myocardial perfusion via the grafts.
More Related Videos
 05:25
Surgical Porcine Model of Chronic Myocardial Ischemia Treated by Exosome-laden Collagen Patch and Off-pump Coronary Artery Bypass Graft
Published on: September 15, 2023
 08:49
Cardiac Loading using Passive Left Atrial Pressurization and Passive Afterload for Graft Assessment
Published on: August 2, 2024
