Related Experiment Video
Updated: Aug 23, 2026
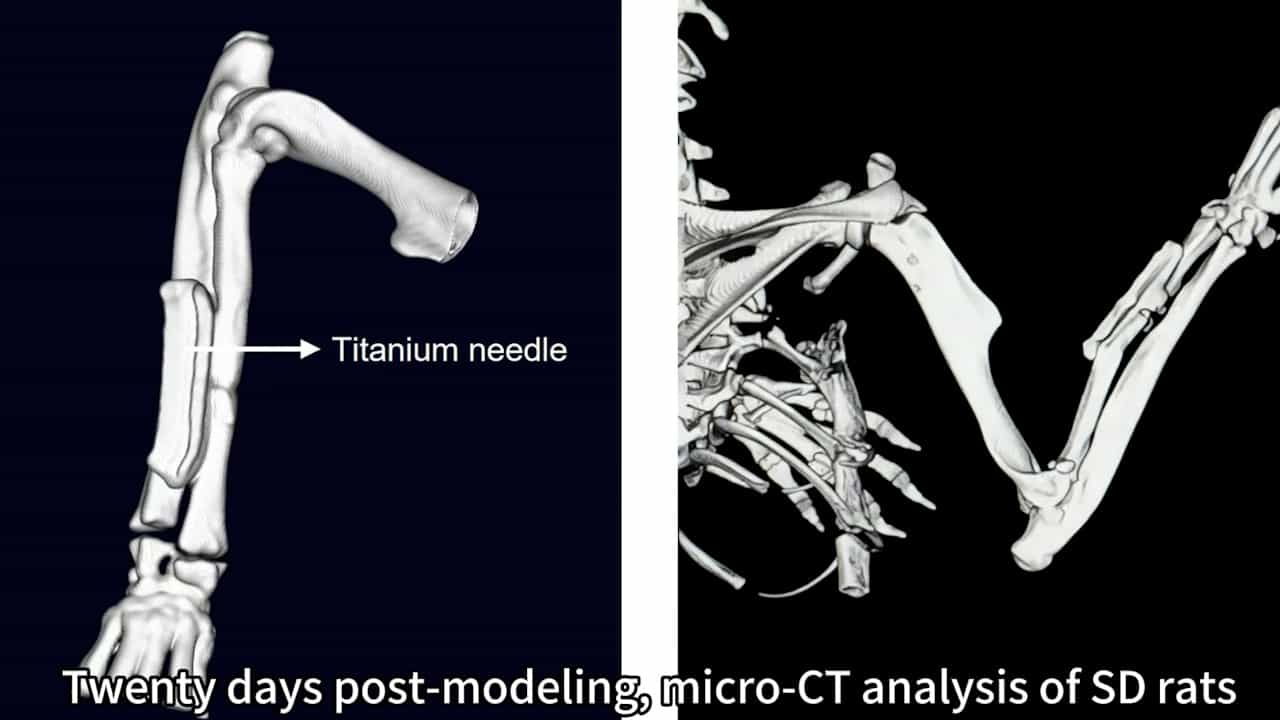

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Compartment syndrome following intramedullary fixation of pediatric forearm fractures
Philip S Yuan1, Maya E Pring, Tracey P Gaynor
1Department of Orthopaedics, Children's Hospital, San Diego, California, and the Department of Orthopaedics, University of California, San Diego, California 91123, USA.

Insights
Intramedullary fixation for pediatric both-bone forearm fractures increases compartment syndrome (CS) risk compared to casting. Longer surgeries and more fluoroscopy also elevate CS incidence in these pediatric fracture cases.
Area of Science:
- Pediatric Orthopedics
- Trauma Surgery
Background:
- Compartment syndrome (CS) is a serious complication following limb injuries.
- Both-bone forearm fractures are common in children and require effective treatment to minimize risks.
Purpose of the Study:
- To determine the incidence of compartment syndrome (CS) in children treated for both-bone forearm fractures.
- To compare CS rates across different treatment modalities for pediatric forearm fractures.
Main Methods:
- Retrospective analysis of 285 pediatric patients with both-bone forearm fractures.
- Categorization of fractures into closed and open injuries.
- Comparison of CS incidence based on treatment: closed reduction and casting, closed reduction and intramedullary fixation, and open reduction with intramedullary pinning.
Main Results:
- Intramedullary fixation (10% CS) showed a higher CS incidence than closed reduction and casting (0% CS) for closed fractures.
- Open fractures treated with debridement and intramedullary pinning had a 6% CS incidence.
- Intramedullary fixation overall had a significantly increased CS incidence compared to casting (P < 0.001).
- Longer operative times and increased intraoperative fluoroscopy use correlated with higher CS risk in surgically treated patients.
Conclusions:
- Intramedullary fixation for pediatric both-bone forearm fractures is associated with a higher risk of compartment syndrome than non-operative casting.
- Surgical factors such as operative duration and fluoroscopy use are critical considerations in managing CS risk for these fractures.
Abstract:
This study was designed to evaluate the incidence of compartment syndrome (CS) resulting from the treatment of both-bone forearm fractures in children. A retrospective analysis of 285 consecutive children who presented with both-bone forearm fractures was performed. Of 235 closed injuries, 205 were treated with closed reduction and casting; none of these patients developed CS. Thirty of the closed injuries were treated with closed reduction and intramedullary fixation; three of these patients (10%) developed CS. Fifty patients sustained open fractures and were treated with debridement and open reduction with intramedullary pinning; CS developed in three of these patients (6%). The eighty patients treated with intramedullary fixation had an increased incidence of CS compared with the 205 patients treated with closed reduction and casting (P < 0.001). Within the group of patients who had surgery, patients with longer operative times and more use of intraoperative fluoroscopy were at higher risk of developing CS.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
