Related Experiment Video
Updated: Aug 23, 2026


A Retrograde Implantation Approach for Peritoneal Dialysis Catheter Placement in Mice
Published on: July 20, 2022
Compared time profiles of ultrafiltration, sodium removal, and renal function in incident CAPD and automated
Ana Rodriguez-Carmona1, Miguel Pérez-Fontán, Rafael Garca-Naveiro
1Division of Nephrology, Hospital Juan Canalejo, A Coruña, Spain.

Background:
Fluid and sodium removal rates may not be equivalent in patients undergoing automated peritoneal dialysis (APD) and continuous ambulatory peritoneal dialysis (CAPD). This may influence compared cardiovascular outcomes in both groups.
Methods:
The authors compared prospectively the time courses of ultrafiltration, sodium removal, and residual renal function (RRF) in a group of incident patients treated with CAPD (n = 53) or APD (n = 51) for at least 1 year (mean follow-up, 28.9 months; range, 13 to 62). The authors analyzed potential effects of these factors on blood pressure (BP) control and cardiovascular morbidity and mortality.
Results:
Ultrafiltration and sodium removal rates were consistently lower in APD patients (mean differences, 236 mL/d; P = 0.012, and 36 mmol/d; P = 0.018, respectively, end of first year). Moreover, univariate and multivariate analysis indicated that APD therapy results in a moderate, but significantly faster decline of RRF than CAPD therapy. Analysis of clinical outcomes showed that CAPD (versus APD) therapy or higher ultrafiltration or sodium removal rates were associated with a better time course of systolic, but not diastolic, BP. We were unable to identify PD modality, ultrafiltration, or sodium removal rates as independent predictors of cardiovascular morbidity and mortality.
Conclusion:
Ultrafiltration and sodium removal rates are consistently lower in incident APD patients than in their counterparts undergoing CAPD. Moreover, RRF declines faster during APD than during CAPD therapy, although this difference may be partially counteracted by a detrimental effect of ultrafiltration on RRF. Aside from a better control of systolic BP in CAPD patients, these differences do not portend significant cardiovascular consequences during the first years of PD therapy.
Related Concept Videos
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:30
Peritoneal Dialysis I: Introduction and Procedure
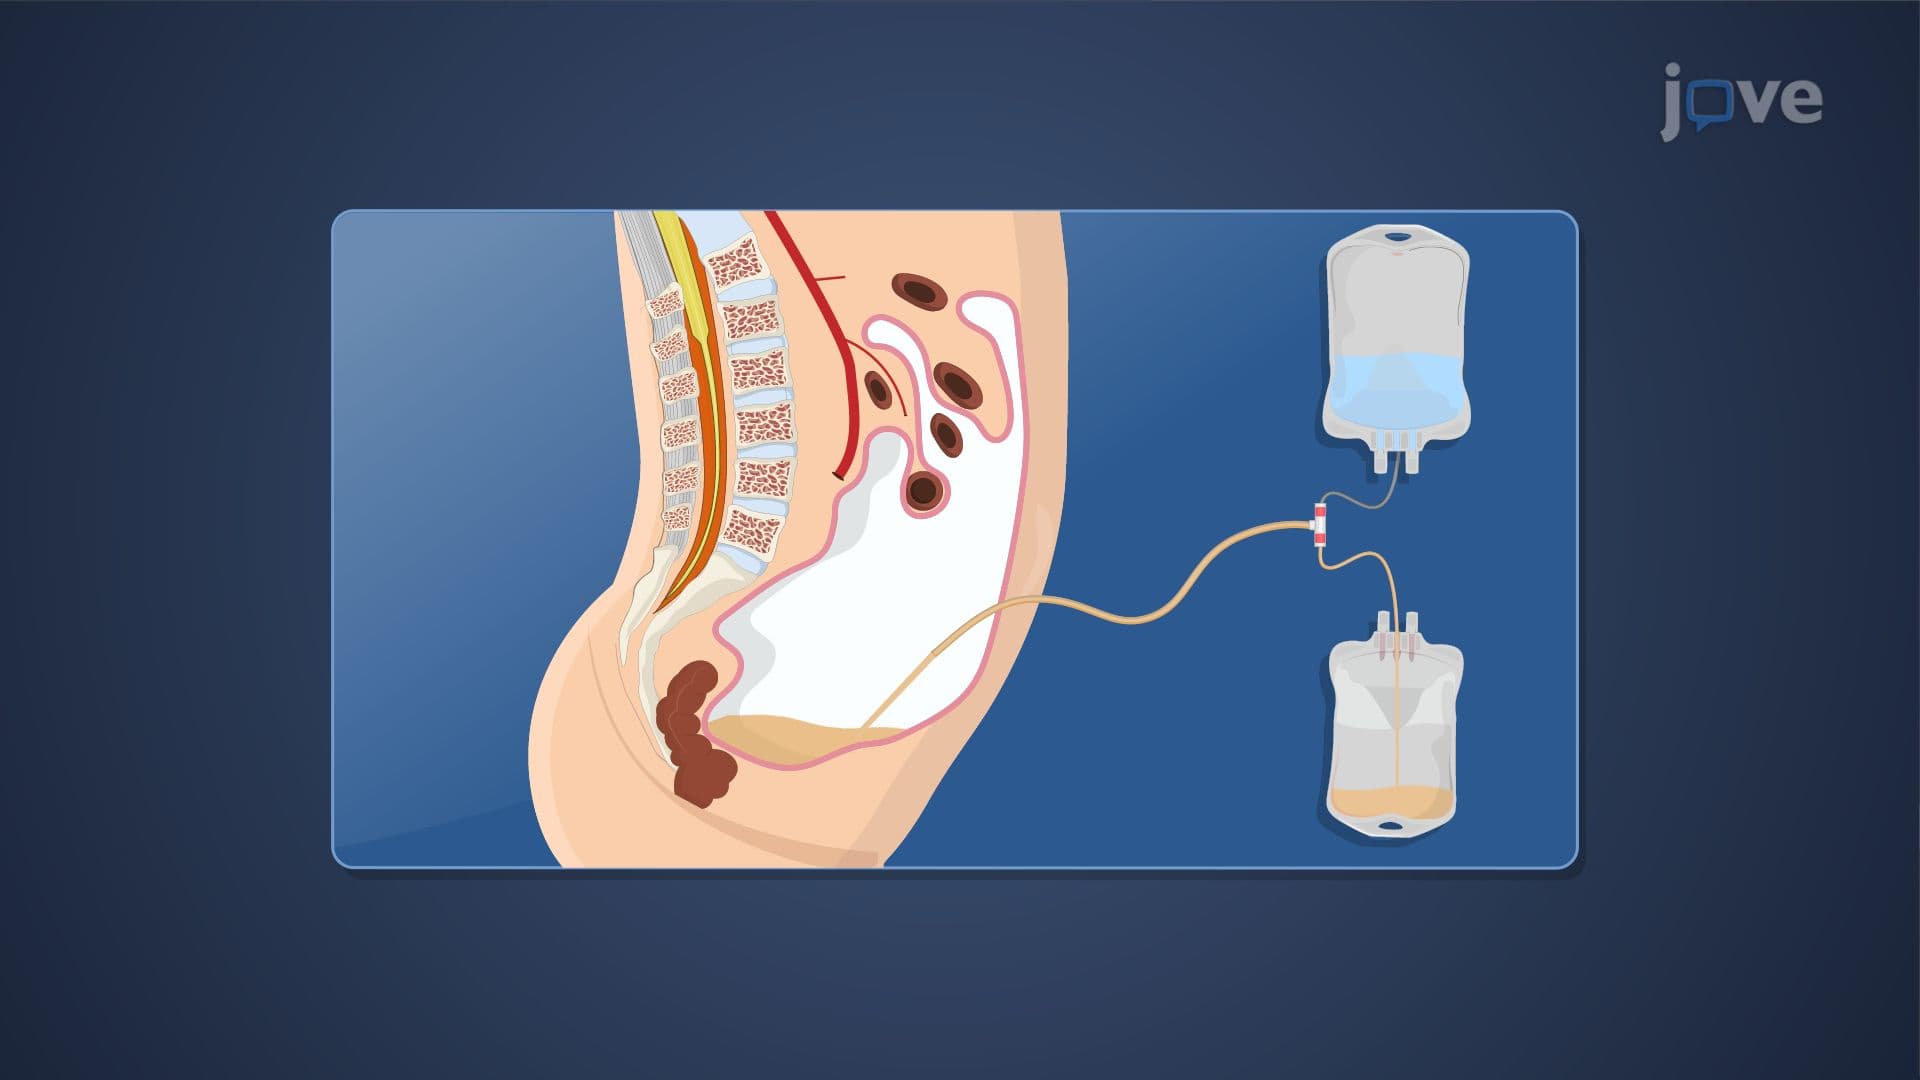 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis