Related Experiment Video
Updated: Oct 20, 2026
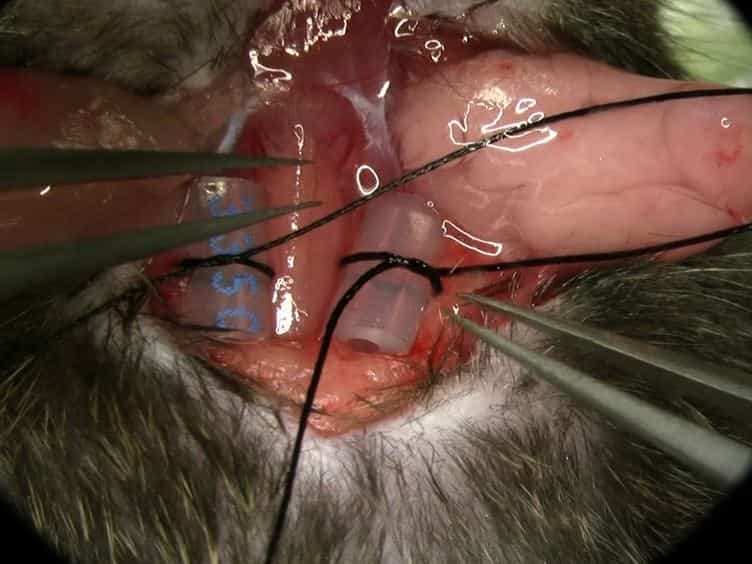
Bilateral Common Carotid Artery Occlusion as an Adequate Preconditioning Stimulus to Induce Early Ischemic Tolerance to Focal Cerebral Ischemia
Published on: May 9, 2013
Does contralateral internal carotid artery occlusion increase the risk of carotid endarterectomy?
B A Perler1, J F Burdick, G M Williams
1Department of Surgery, Johns Hopkins Hospital, Baltimore, MD 21205.

Insights
Carotid endarterectomy outcomes were similar when performed contralateral to an internal carotid artery occlusion versus a patent artery. This study found comparable perioperative stroke and mortality rates between the two groups.
Area of Science:
- Vascular Surgery
- Cerebrovascular Disease
- Cardiovascular Outcomes
Background:
- Carotid endarterectomy (CEA) is a common procedure to prevent stroke.
- The impact of contralateral internal carotid artery (ICA) status on CEA outcomes is debated.
- Understanding risks associated with CEA in the setting of contralateral ICA occlusion is crucial for patient selection and management.
Purpose of the Study:
- To compare the outcomes of CEA in patients with contralateral ICA occlusion versus those with a patent contralateral ICA.
- To assess perioperative stroke, mortality, and cardiac complication rates in these two patient groups.
Main Methods:
- Retrospective comparison of 36 patients undergoing CEA contralateral to ICA occlusion (Group I) and 169 patients with patent contralateral ICA (Group II).
- Patients were matched for age, gender, hypertension, diabetes, and hyperlipidemia.
- Outcomes analyzed included perioperative stroke, operative mortality, and cardiac complications.
Main Results:
- No significant difference in perioperative stroke rates (2.8% vs 4.1%) or operative mortality (0% vs 1.2%) between Group I and Group II.
- Group I patients had a higher incidence of prior myocardial infarction and exertional angina.
- Perioperative stroke incidence in Group II did not correlate with the degree of contralateral ICA stenosis.
Conclusions:
- CEA can be performed with similar safety and efficacy regardless of contralateral ICA status (occluded or patent).
- Patients with contralateral ICA occlusion may have higher pre-existing cardiac comorbidities.
- The degree of contralateral ICA stenosis does not appear to significantly influence perioperative stroke risk in patients undergoing CEA.
Abstract:
The results of every carotid endarterectomy performed contralateral to an internal carotid artery occlusion (n = 36) (group I) were compared with those performed contralateral to a patent internal carotid artery (n = 169) (group II) over the last 10 years. The patients in each group were evenly matched with respect to male gender (66% vs 69%); mean age (66.7 vs 65.9 years); and incidence of hypertension (55.6% vs 53.2%), diabetes (16.7% vs 20.1%), and hyperlipidemia (8.3% vs 11.8%). Patients in group I had a higher incidence of previous myocardial infarction (25% vs 11.8%, p less than 0.05) and exertional angina (55.6% vs 29.6%, p less than 0.01). Indications for carotid endarterectomy were equivalent, including stroke (19.4% vs 21.9%), transient ischemic attacks (36.1% vs 35.5%), amaurosis fugax (16.7% vs 11.8%), nonhemispheric symptoms (5.6% vs 8.3%), and asymptomatic stenoses (22.2% vs 22.5%), respectively. Perioperative strokes occurred in one (2.8%) patient in group I and seven (4.1%) patients in group II (NS). Among the patients in group II the incidence of perioperative stroke did not correlate directly with the degree of contralateral ICA stenosis: greater than 90% (4%); 70% to 90% (6.7%); 50% to 70% (8.7%); and less than 50% (2.8%). The operative mortality rate was 0% among patients in group I and 1.2% among patients in group II (NS). Cardiac complications occurred in two (5.6%) patients in group I and nine (5.3%) patients in group II (NS).(ABSTRACT TRUNCATED AT 250 WORDS)
More Related Videos
 13:18
Optimization of the Longa Middle Cerebral Artery Occlusion Method for Complete Reperfusion
Published on: November 22, 2024
 09:36
A Magnetic Resonance Imaging-based Computational Protocol for Analysis of Plaque Morphology and Hemodynamics in Patients with Carotid Artery Stenosis
Published on: August 12, 2025
Related Concept Videos
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:26
Aneurysm III: Interprofessional Care