Analgesic dose-response relation in cervical epidural block
Related Experiment Video
Updated: Aug 23, 2026

Electrophysiological Methods to Assess Peripheral Pain Block in an Anesthetized Rat
Published on: November 21, 2025
Y Hirabayashi1, I Matsuda, S Inoue
1Department of Anesthesiology, Jichi Medical School, Tochigi, Japan.

Abstract:
The relationship between the age and the spread of analgesia from different epidural anesthetic doses was examined by studying analgesic dose responses in cervical epidural analgesia. Two different anesthetic doses (5 ml or 10 ml) of 2% mepivacaine were injected into the cervical epidural space at a constant pressure (80 mmHg) using an intravenous apparatus, and the spread of analgesia to pinprick was assessed. The significant correlation was found between the patient's age and the number of spinal segments blocked (5 ml : r = 0.8498, P < 0.01, 10 ml : r = 0.5988, P < 0.01). The inverse linear relationship was found between the patient's age and the segmental dose requirement (5 ml : r = -0.6754, P < 0.01, 10 ml : r = -0.5784, P < 0.01). Patients under 39 years of age showed a direct relationship between the dose injected and the number of spinal segments blocked, enabling prediction of the number of segments blocked with a given dose of local anesthetic. Doubling the epidural dose approximately doubled the number of spinal segments blocked. The analgesic dose-response relation in patients over 60 years of age differed from that in patients under 39 years of age and doubling the epidural dose did not double the number of spinal segments blocked. Progressively more extensive analgesia was obtained from a given dose of local anesthetic with advancing age. It was difficult to limit the extent of analgesia by injecting a smaller dose of local anaesthetic in the elderly.
Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:03
Dose-Response Relationship: Overview
 01:25
Analgesia and Pain Management
 01:21
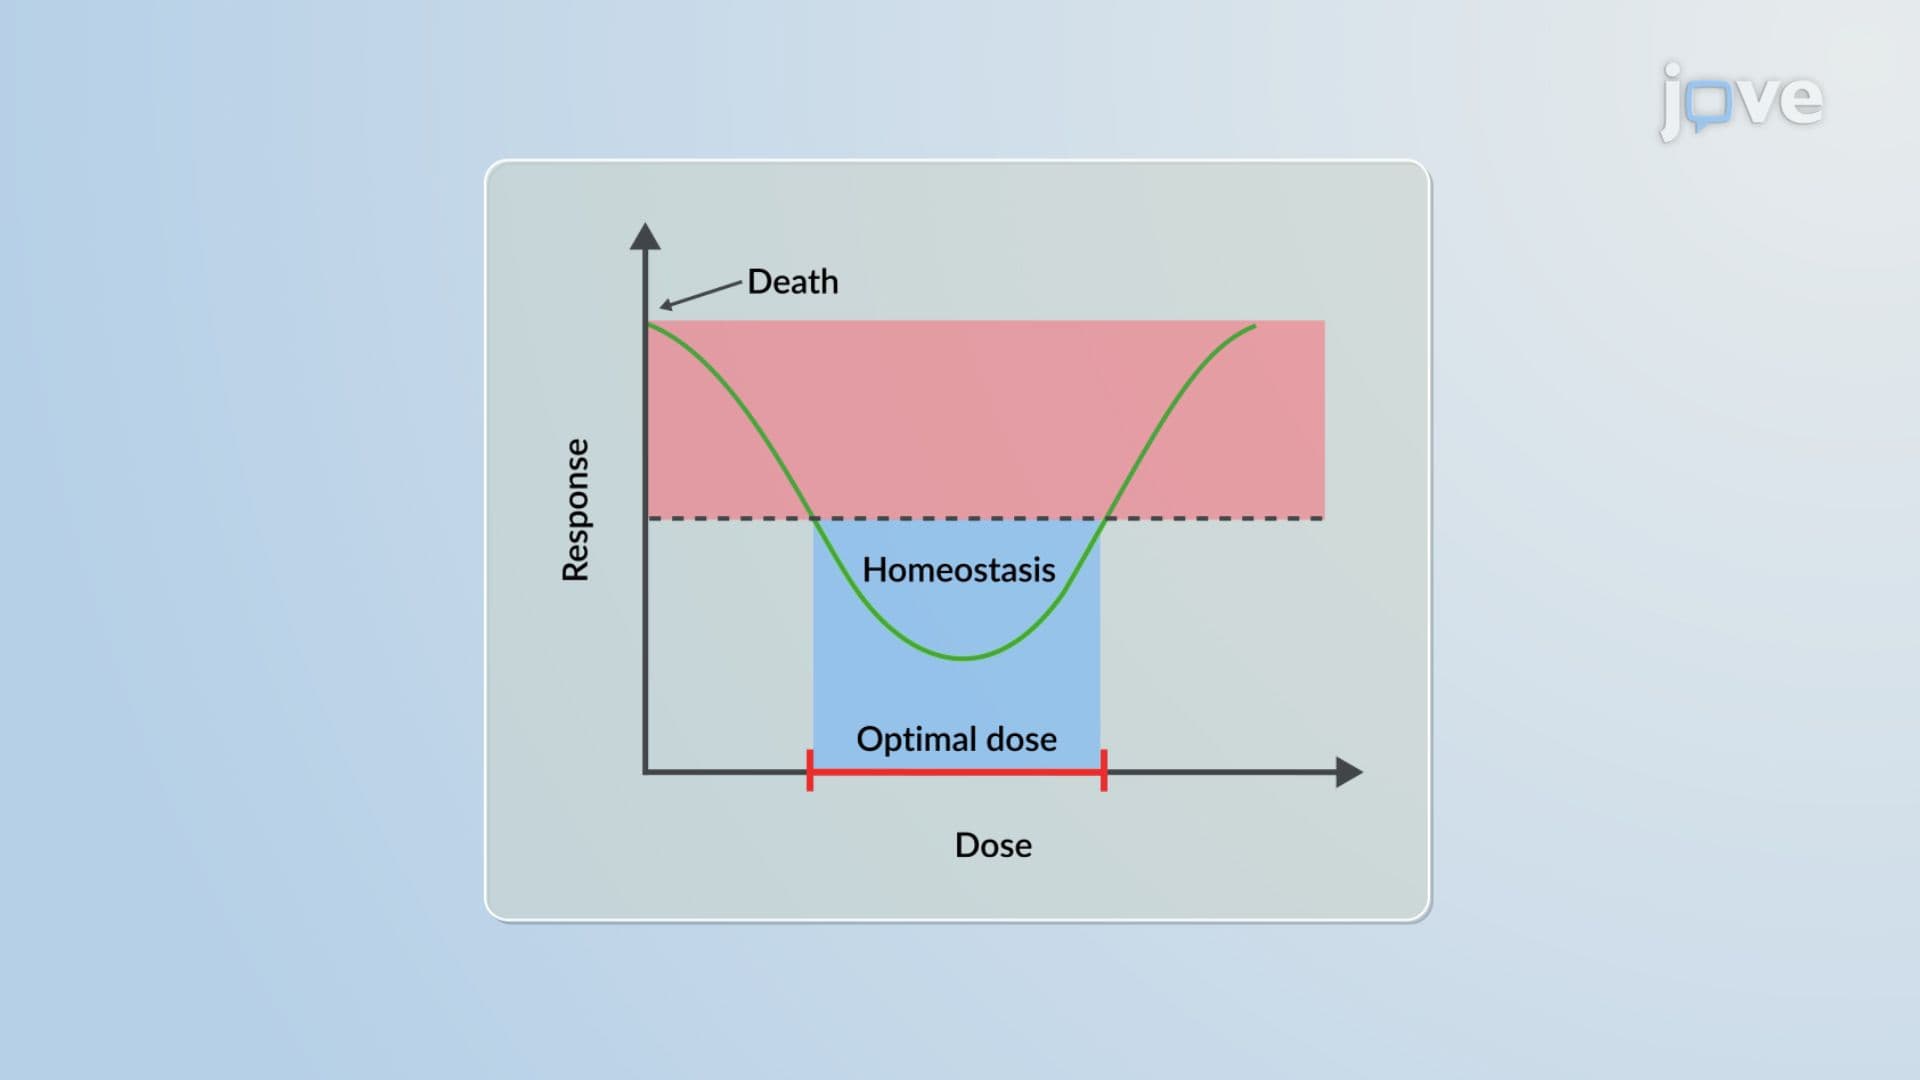
Dose Response Curve: Conventional Versus Nonmonotonic