Related Experiment Video
Updated: Aug 23, 2026

Isolation of Human Atrial Myocytes for Simultaneous Measurements of Ca2+ Transients and Membrane Currents
Published on: July 3, 2013
The cardiovascular effects of atracurium and it's metabolite
K Fukushima1, T Aoki, K Watanabe
1Department of Anesthesiology, National Defense Medical College, Tokorozawa, Japan.

Abstract:
The administration of atracurium to humans has been reported to produce little cardiovascular effects in clinical doses. The cardiovascular effect, histamine-releasing and catecholamine releasing effects of intravenous injection of atracurium 0.6 and 1.2 mg.kg(-1) were studied in man, and also the cardiovascular and catecholamine releasing effects of laudanosine which is a metabolite of atracurium by Hofmann degeneration, were studied in dogs. The increase in human plasma concentration of histamine, hypotension and tachycardia were found with the dose of atracurium 1.2 mg.kg(-1). The intravenous administration of laudanosine 10 micro g.kg(-1) to dogs produced minimal epinephrine, norepinephrine releases and cardiovascular changes.

Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:11
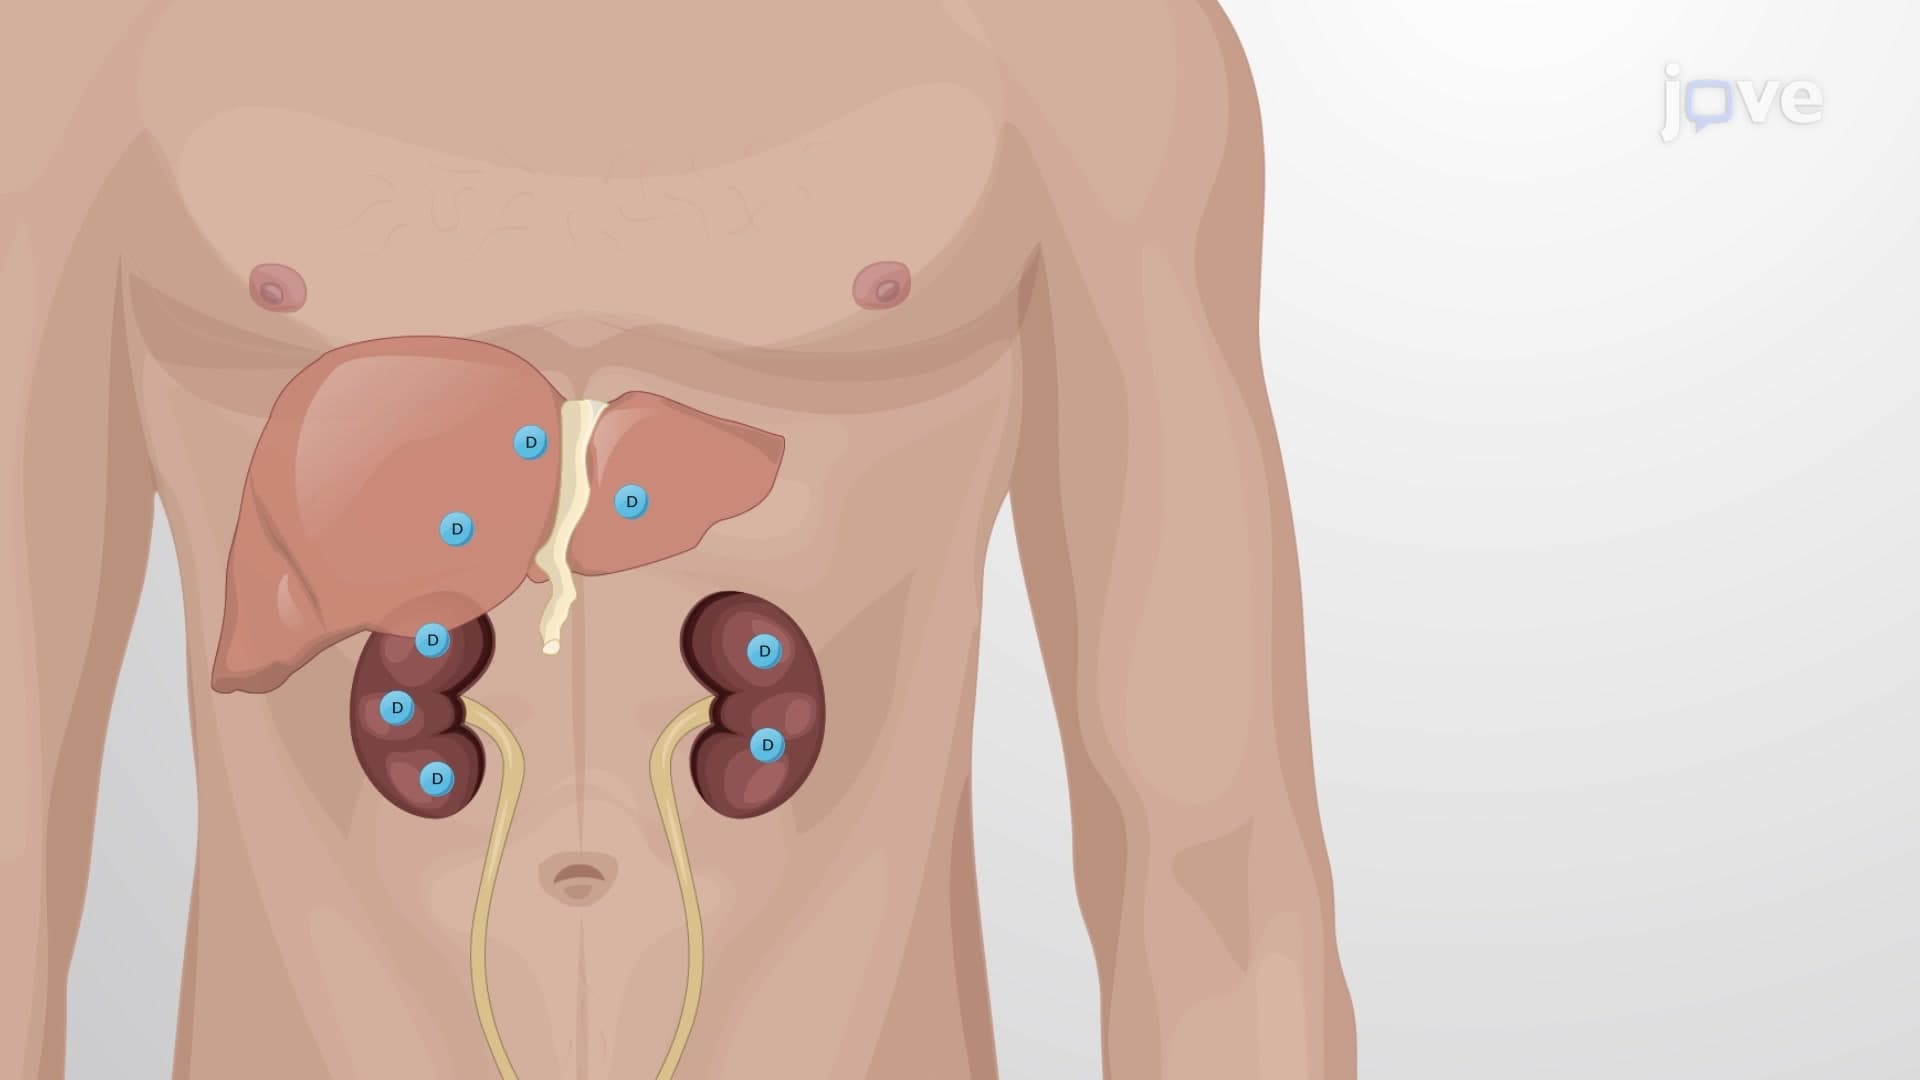
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:17
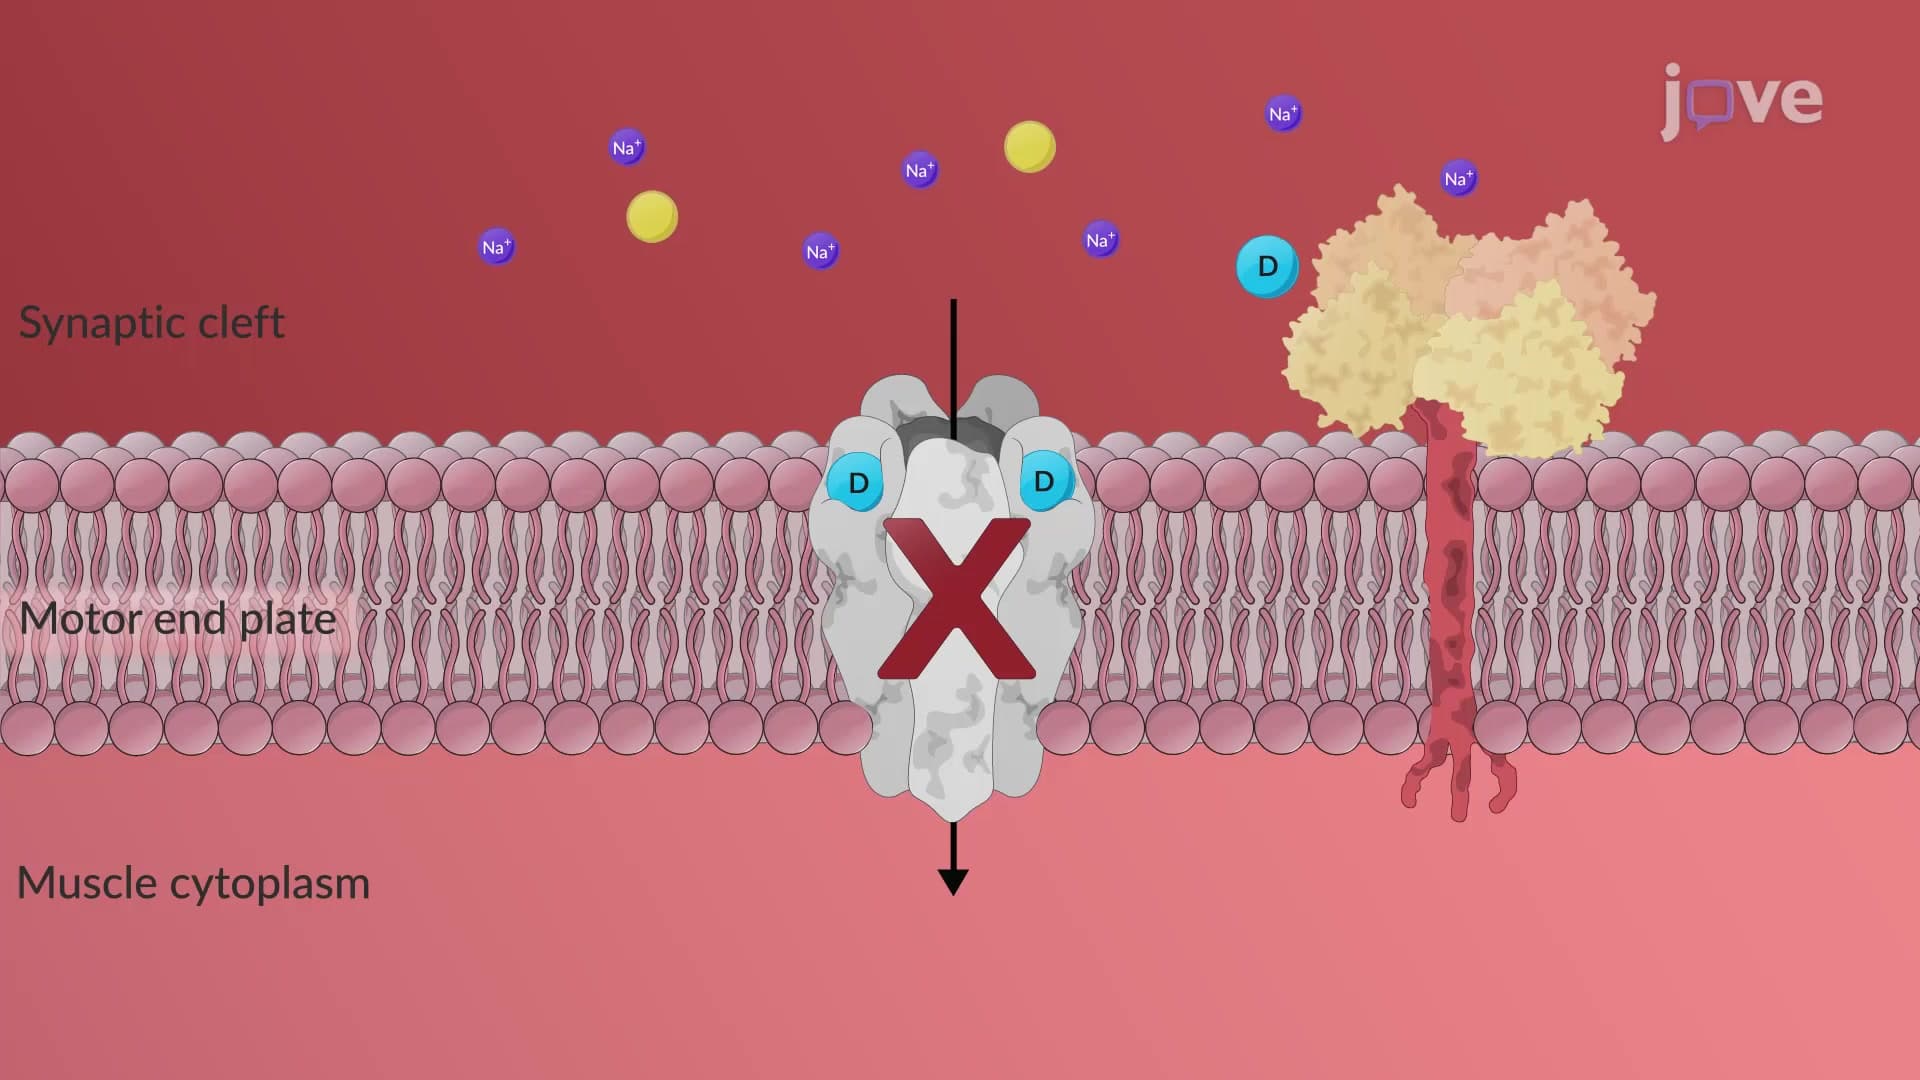
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System