Related Experiment Video
Updated: Aug 23, 2026
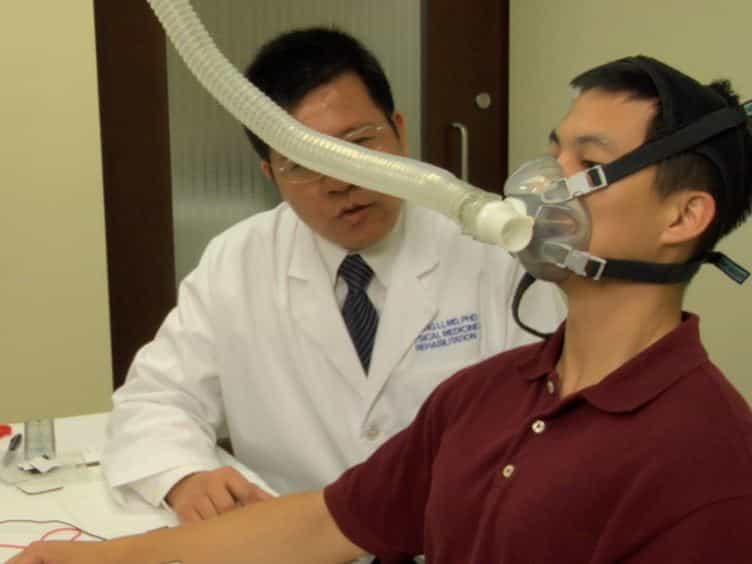

Breathing-controlled Electrical Stimulation (BreEStim) for Management of Neuropathic Pain and Spasticity
Published on: January 10, 2013
Orally delivered baclofen to control spastic hypertonia in acquired brain injury
Jay M Meythaler1, Warren Clayton, Linda K Davis
1Department of Physical Medicine and Rehabilitation, School of Medicine, University of Alabama at Birmingham, Spain Rehabilitation Center R157, 619 6th Avenue S., Birmingham, AL 35249, USA.

Abstract:
To determine if oral/systemic delivery of baclofen can effectively decrease spastic hypertonia due to acquired brain injury (traumatic brain injury, stroke, anoxia, or encephalopathy). Tertiary care outpatient rehabilitation center directly attached to a university hospital. Patients were a convenience sample recruited consecutively who had been referred for treatment of their spastic hypertonia to our spasticity clinic over a 5-year period. The spastic hypertonia was due to an acquired brain injury by either traumatic brain injury (TBI), stroke, or anoxic brain injury. All patients were more than 6 months postinjury or illness. Retrospective review of patients before and after initiation of treatment with oral baclofen, per standardized clinical data sheets. Thirty-five patients (22 TBI patients) were started on oral baclofen and were reevaluated between 1 to 3 months after initiation of treatment. Data for motor tone (Ashworth scores), spasm scores (Penn spasm frequency score), and deep tendon reflex scores were collected on the affected upper extremity (UE) and lower extremity (LE) side(s). Normal extremities were not assessed. Differences over time were assessed via descriptive statistics and Wilcoxon signed-rank. After 1 to 3 months of treatment when subjects had reached their maximal tolerated dosage, the average LE Ashworth score in the affected lower extremities (LEs) decreased from 3.5 to 3.2 (P =.0003), the reflex score decreased from 2.5 to 2.2 (P =.0274), and there was no statistical difference in the spasm score (P >.05). When the 22 TBI patients are analyzed separately, the average LE Ashworth score decreased from 3.5 to 3.2 (P =.0044) and the reflex score decreased from 2.7 to 2.0 (P =.0003). There was no statistically significant change in UE tone, spasm frequency, or reflexes after 1 to 3 months of treatment (P >.05). The average dosage at follow-up was 57 mg/day of baclofen (range 15-120 mg/day). There was a 17% incidence of somnolence that limited the maximum daily dosage of the medication. The oral delivery of baclofen is capable of reducing LE spastic hypertonia resulting from acquired brain injury. The lack of effect upon the upper extremities may be due to receptor specificity issues. GABA-B receptors may be less involved in the modulation of UE spastic hypertonia.

Related Concept Videos
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:29
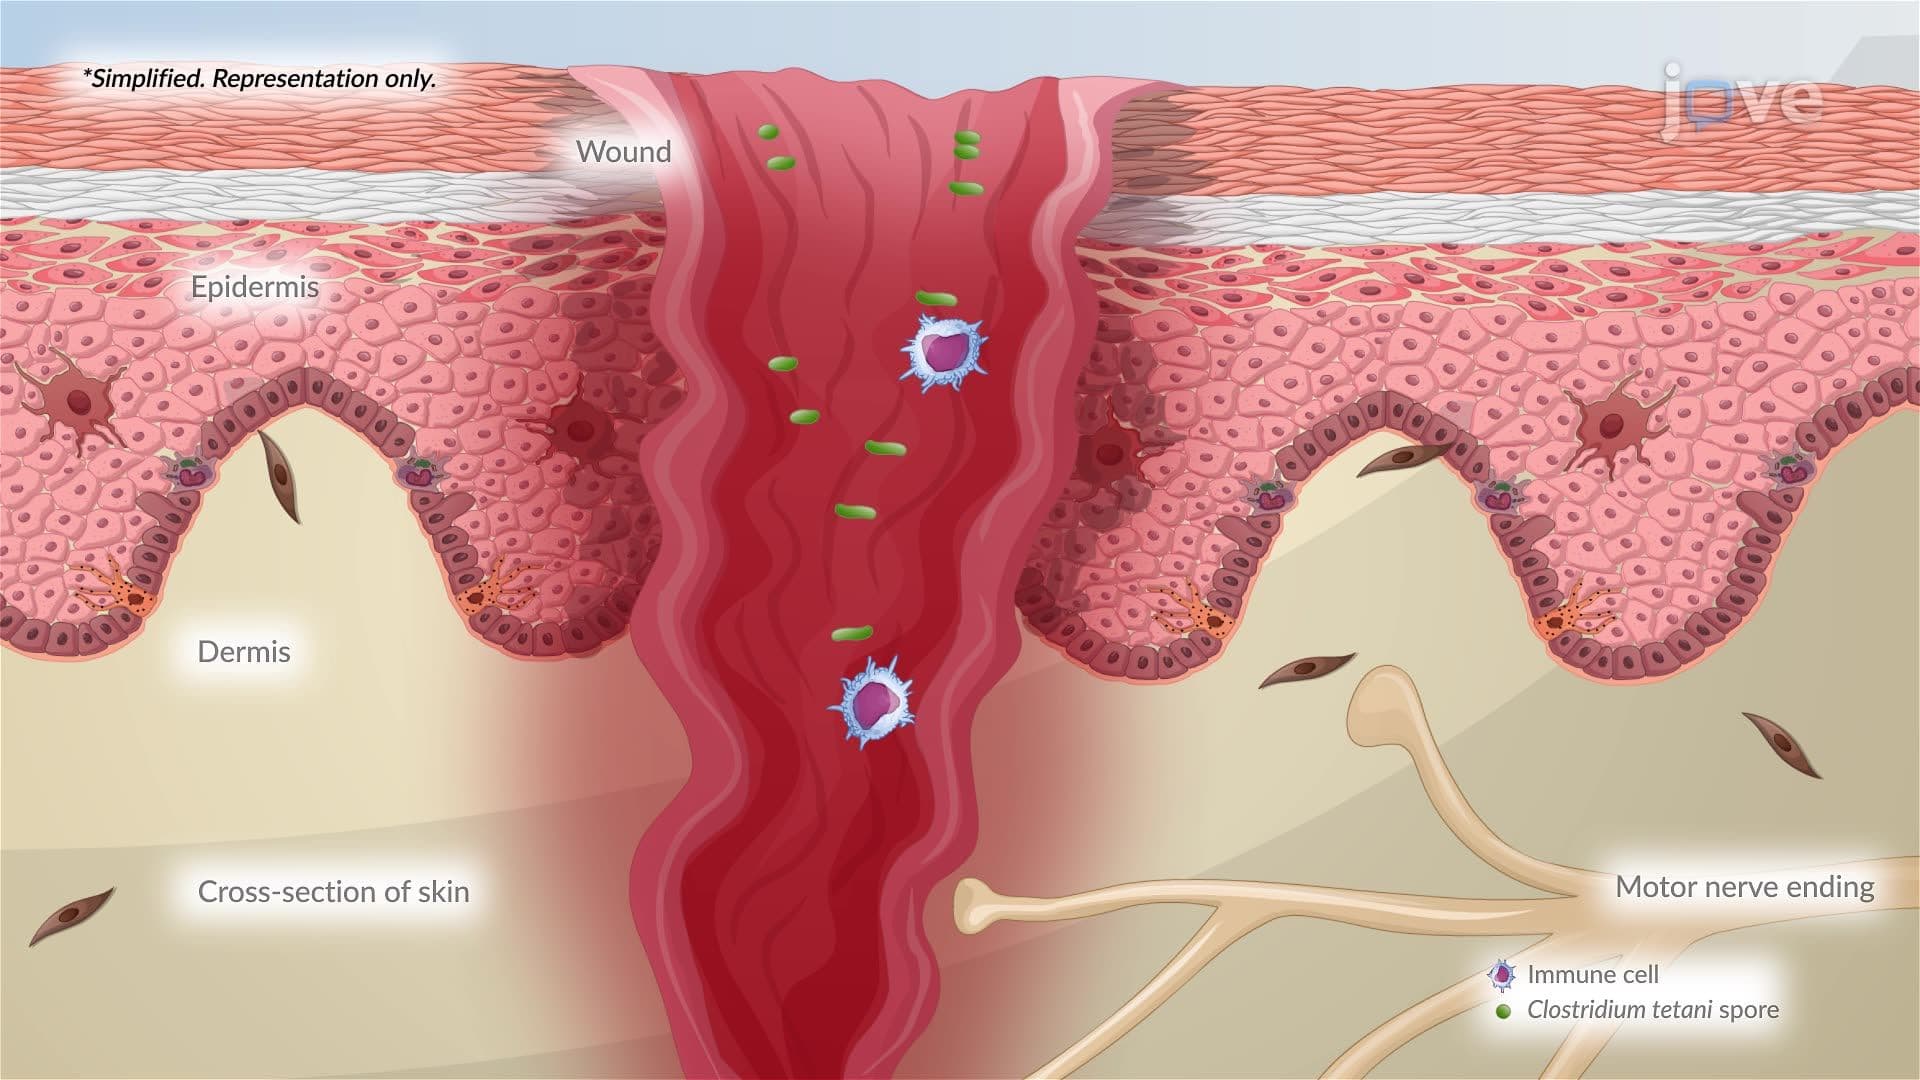
Tetanus
 01:24
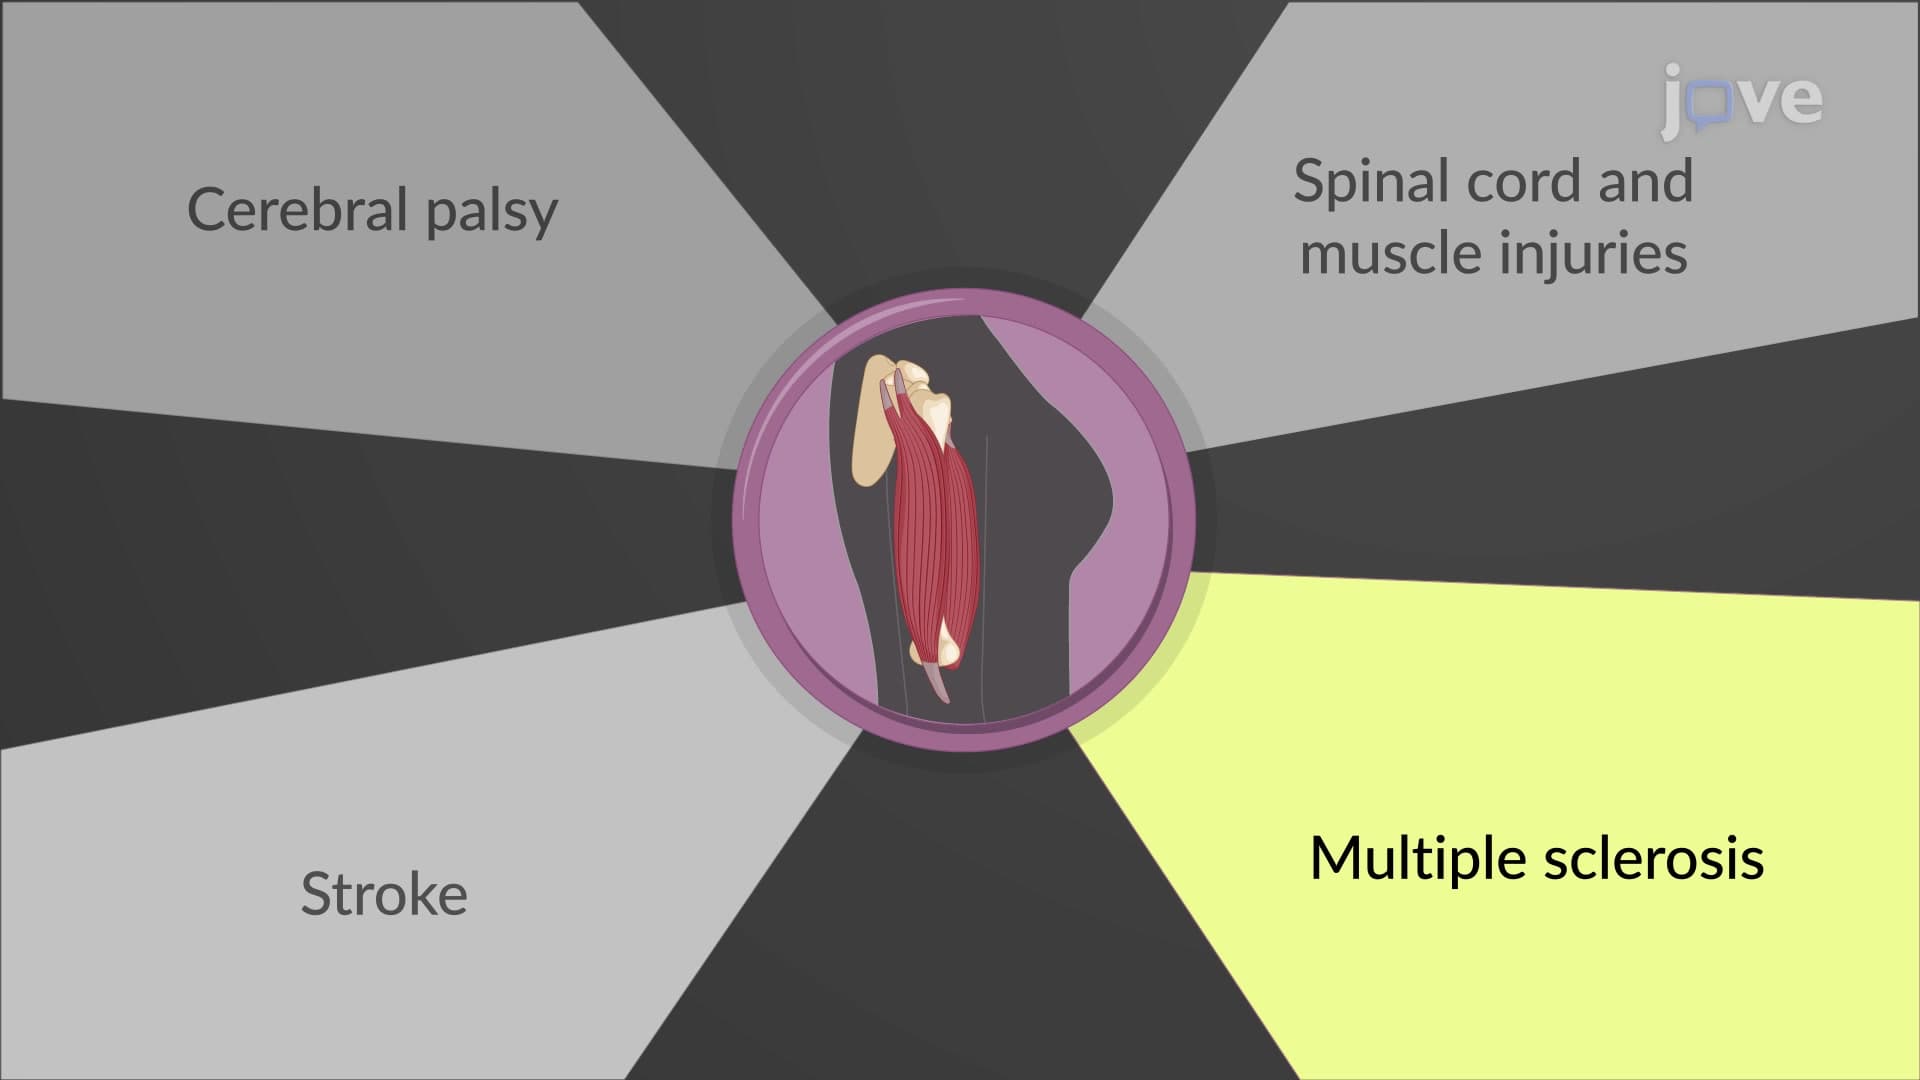
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...