Related Experiment Video
Updated: Aug 23, 2026


Isolation and Functional Characterization of Human Ventricular Cardiomyocytes from Fresh Surgical Samples
Published on: April 21, 2014
[Arrhythmias of primary hypertrophic cardiomyopathy]
D Babuty1, L Fauchier, D Nguyen
1Service de cardiologie B, hôpital Trousseau, Tours. d.babuty@chu-tours.fr

Insights
Primary hypertrophic cardiomyopathy, a genetic heart disease, causes arrhythmias like atrial fibrillation and ventricular tachycardia. Identifying high-risk patients is crucial for preventing sudden cardiac death, often requiring an automatic defibrillator.
Area of Science:
- Cardiology
- Genetics
- Molecular Biology
Context:
- Primary hypertrophic cardiomyopathy (HCM) is an inherited cardiac condition.
- It results from sarcomere gene mutations leading to myocardial structural and functional changes.
- These changes predispose patients to various cardiac arrhythmias.
Purpose:
- To review the types of arrhythmias associated with primary HCM.
- To discuss the diagnostic parameters for identifying patients at high risk of sudden cardiac death.
- To outline current treatment strategies for managing arrhythmias in HCM.
Summary:
- HCM causes arrhythmias through reentry and triggered automatic activity, with atrial fibrillation and ventricular arrhythmias being most common.
- Junctional tachycardias (e.g., Wolff-Parkinson-White syndrome) are rarer but linked to specific genetic mutations.
- Non-sustained ventricular tachycardia indicates a poor prognosis, especially in younger individuals, while sustained arrhythmias necessitate an automatic defibrillator.
Impact:
- Early identification of high-risk individuals through multi-parameter analysis (clinical, anatomical, functional, genetic) is key.
- Preventive measures, including automatic defibrillator implantation, are vital for managing life-threatening arrhythmias.
- This understanding aids cardiologists in risk stratification and timely intervention for HCM patients.
Abstract:
Primary hypertrophic cardiomyopathy is a genetic disease causing sarcomere dysfunction. The structural and functional myocardial changes combine to produce cardiac arrhythmias related to reentry phenomena and to triggered automatic activity. The commonest arrhythmias are atrial fibrillation and ventricular arrhythmias; junctional tachycardias via the bundle of Kent are rare. Atrial fibrillation and the Wolff-Parkinson-White syndrome are more commonly associated with certain genetic mutations. Their treatment is mainly based on medication with amiodarone or on radiofrequency ablation in cases of junctional tachycardia. Ventricular arrhythmias are mainly isolated ventricular extrasystoles and non-sustained ventricular tachycardia. The prognostic significance of the latter has been subject of debate for many years but recent studies report a poor prognosis with non-sustained ventricular tachycardia especially in the young patients. Sustained ventricular tachycardia and ventricular fibrillation, though life-threatening complications of hypertrophic cardiomyopathy, are rarely documented and justify implantation of an automatic defibrillator as the risk of recurrence is high. The main objective of the cardiologist in cases of primary hypertrophic cardiomyopathy is to identify the patient at high risk of sudden death. This requires analysis of several parameters: clinical, anatomical, haemodynamic, rhythmic, functional and genetic. The presence of at least two risk factors for sudden death justifies preventive measures. The implantation of an automatic defibrillator is the most reliable form of treatment.

Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:25
Cardiomyopathy I: Introduction and Classification
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
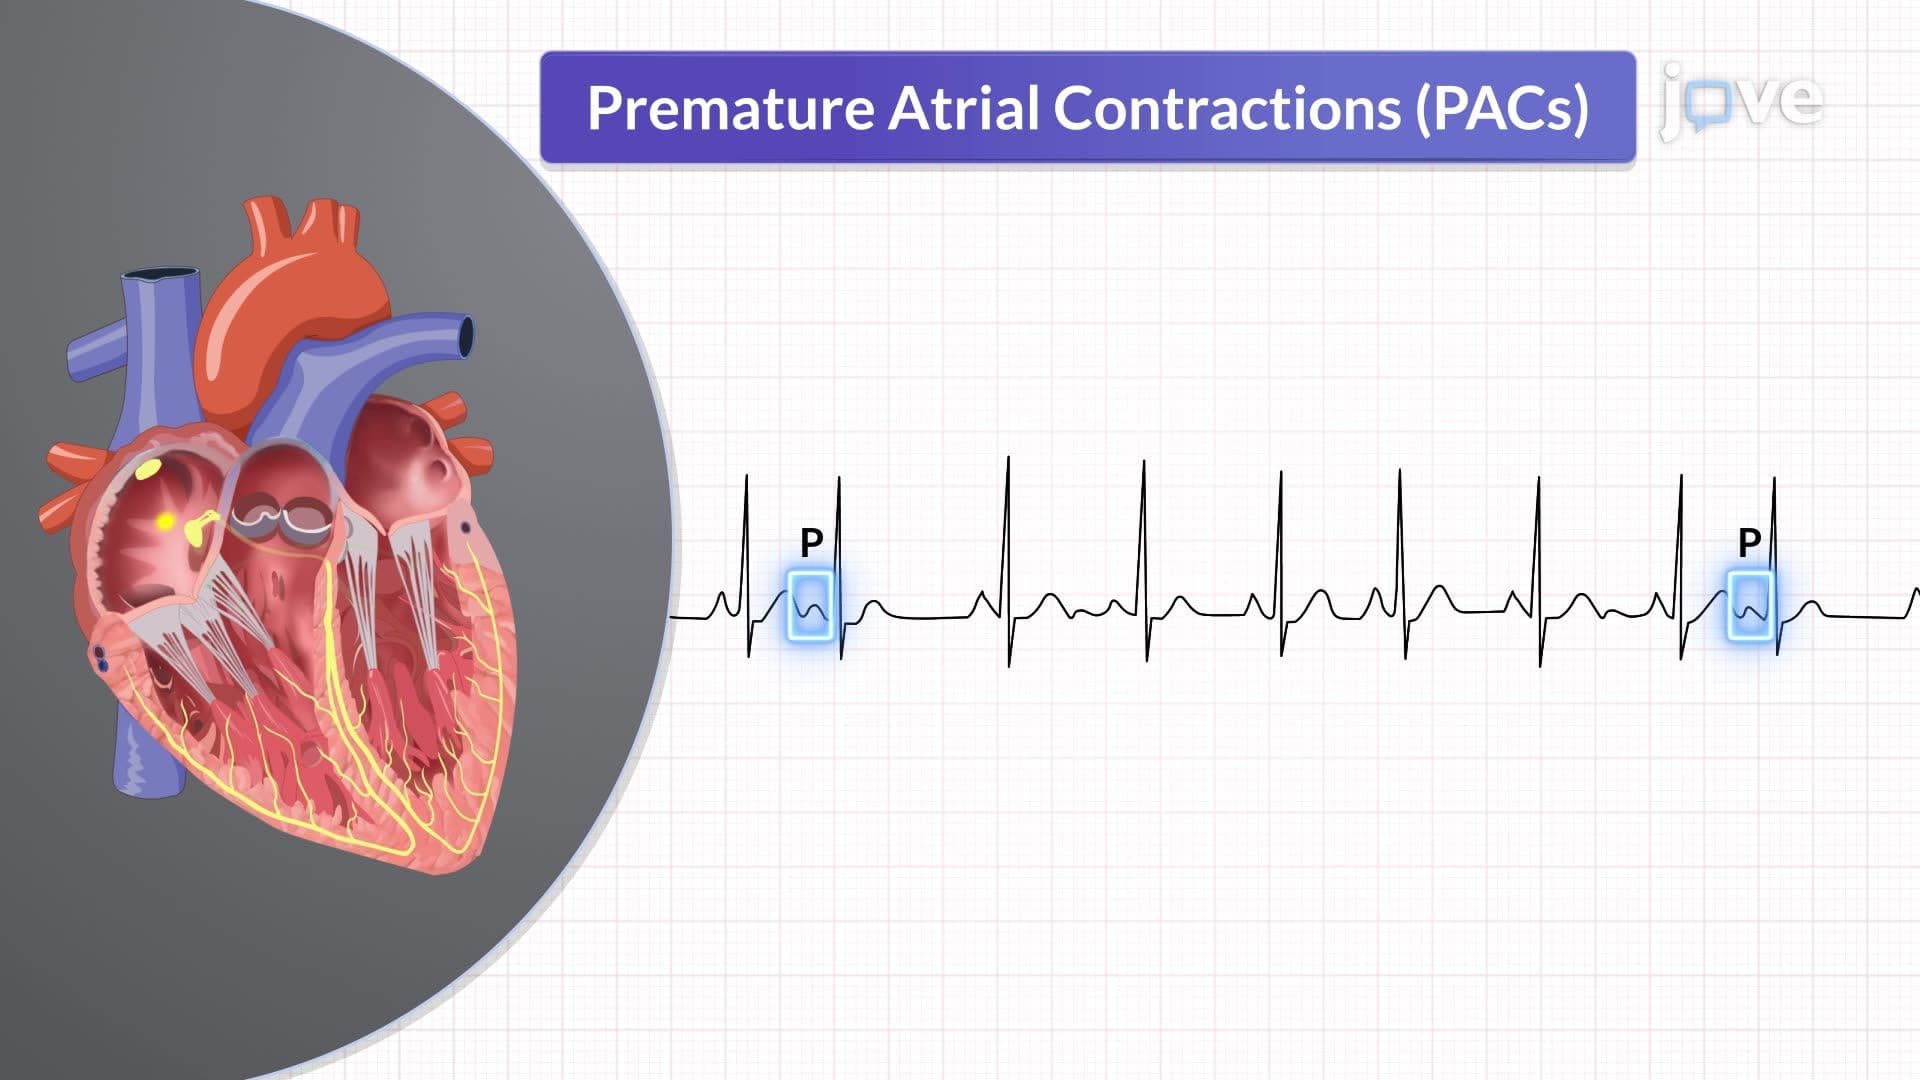
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias