

How can we diagnose and manage twin-twin transfusion syndrome?
1Department of Obstetrics and Fetal Medicine, Universitäts Klinikum-Eppendorf, Martimistrasse 52 D-20246 Hamburg, Germany.

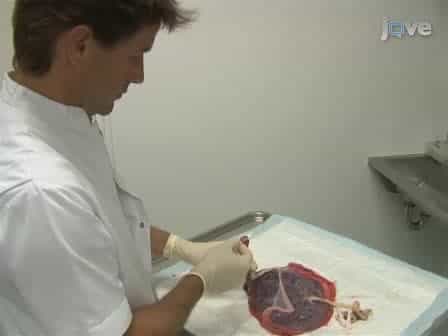
Severe mid-trimester twin-twin transfusion syndrome (TTS) complicates about 15% of monochorionic twin pregnancies. If left untreated, the mortality is 80-100%. The pathophysiological prerequisite for the onset of TTS is unequal blood flow via arteriovenous placental anastomoses from the so-called donor to the recipient twin. This can result in hypovolemia, hypotension and oligo- or anuria in the donor, and hypervolemia, hypertension, polyuria and finally heart failure in the recipient. Leading sonographic signs of TTS include severe oligo- or anhydramnios and a small or absent bladder filling in the donor in contrast to polyhydramnios with increased bladder filling in the recipient. Patients might present with clinical symptoms due to massive polyhydramnios. In severe mid-trimester TTS, fetoscopic laser occlusion of the anastomosing vessels on the placental surface under local anaesthesia plus subsequent amniodrainage is the most promising therapeutic option at present. In acute TTS after 26 weeks of gestation, amniodrainage is the therapy of choice. All patients suspected of this high-risk condition should be referred to a specialized fetal medicine centre.
Severe mid-trimester twin-twin transfusion syndrome (TTS) complicates about 15% of monochorionic twin pregnancies. If left untreated, the mortality is 80-100%. The pathophysiological prerequisite for the onset of TTS is unequal blood flow via arteriovenous placental anastomoses from the so-called donor to the recipient twin. This can result in hypovolemia, hypotension and oligo- or anuria in the donor, and hypervolemia, hypertension, polyuria and finally heart failure in the recipient. Leading sonographic signs of TTS include severe oligo- or anhydramnios and a small or absent bladder filling in the donor in contrast to polyhydramnios with increased bladder filling in the recipient. Patients might present with clinical symptoms due to massive polyhydramnios. In severe mid-trimester TTS, fetoscopic laser occlusion of the anastomosing vessels on the placental surface under local anaesthesia plus subsequent amniodrainage is the most promising therapeutic option at present. In acute TTS after 26 weeks of gestation, amniodrainage is the therapy of choice. All patients suspected of this high-risk condition should be referred to a specialized fetal medicine centre.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:28
Kidney Transplant I: Introduction
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care