Related Experiment Video
Updated: Aug 23, 2026

Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
Pharmacotyping of hypokalaemic salt-losing tubular disorders
S C Reinalter1, N Jeck, M Peters
1Department of Paediatrics, Philipps University, Marburg, Germany.

Unlabelled:
Long standing confusion exists in the terminology of hypokalaemic salt-losing tubulopathies (SLTs). SLTs are autosomal recessively transmitted and characterized by normotensive secondary hyperreninism/hyperaldosteronism with hypokalaemic metabolic alkalosis. Historically, four phenotypical variants have been described: (1) the (classic) Bartter syndrome (cBS), (2) the hypomagnesaemic hypocalciuric Gitelman syndrome (GS), (3) the hypercalciuric hyperprostaglandin-E-syndrome (HPS) or antenatal Bartter syndrome (aBS) and (4) the hyperprostaglandin-E-syndrome with sensorineural deafness (HPS + SND). The latter two syndromes are the most severe variants with antenatal manifestation with polyhydramnios and life-threatening course of salt- and water-loss. Defects in five renal membrane proteins involved in electrolyte reabsorption have been identified: In HPS-patients mutations in (1) either the furosemide-sensitive sodium-potassium-chloride cotransporter NKCC2, or (2) in the potassium channel ROMK have been identified, and (3) HPS + SND is caused by mutations in the beta-subunit of the chloride channels ClC-Kb and -Ka (named barttin), all mimicking the major pharmacological effects of furosemide with minor potassium-wasting in ROMK-patients as seen in patients treated with simultaneous furosemide and amiloride, and minor calcium-wasting in Barttin-patients resembling the combination of furosemide and thiazides. (4) cBS is caused by mutations in the chloride channel ClC-Kb with similar clinical characteristics as seen under combination of thiazides and furosemide, (5) GS is caused by mutations in the thiazide-sensitive sodium-chloride cotransporter NCCT resembling the effect of long-term thiazide administration.
Conclusion:
The combination of pharmacology and genetics suggests a new terminology for the above described SLTs: Furosemide-like-SLT for HPS caused by NKCC2-mutations, furosemide/amiloride-like-SLT for HPS caused by ROMK-mutations, furosemide/thiazide-like-SLT for HPS + SND, thiazide/furosemide-like-SLT for cBS, and thiazide-like-SLT for GS.
More Related Videos
 13:30
Use of the Ramsay Assay to Measure Fluid Secretion and Ion Flux Rates in the Drosophila melanogaster Malpighian Tubule
Published on: November 25, 2015
 07:06
Isolation of Primary Human Proximal Tubule Epithelial Cells and Their Use in Creating a Microphysiological Model of the Renal Proximal Tubule
Published on: May 9, 2025
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:22
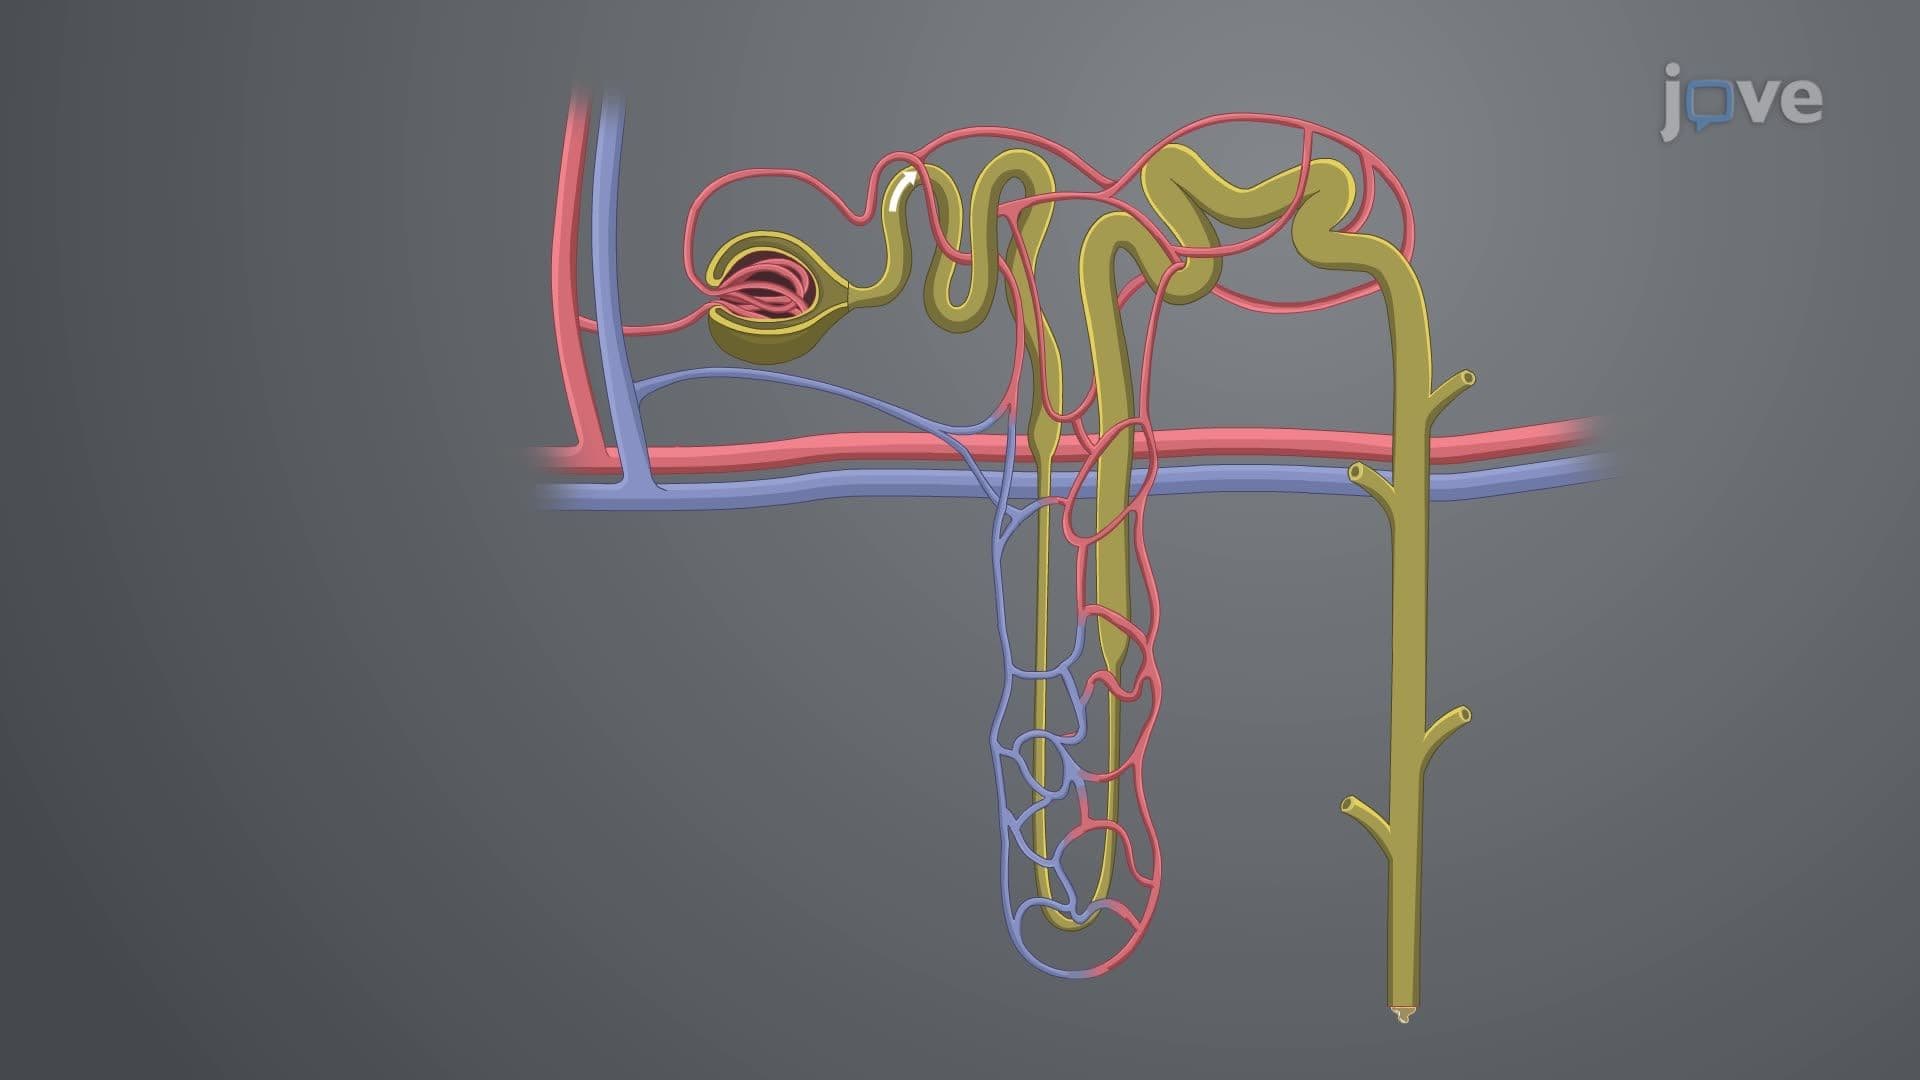
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:22
Heart Failure Drugs: Diuretics
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption