Related Experiment Video
Updated: Aug 23, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Plasma chromogranin A in incidental non-functioning, benign, solid adrenocortical tumors
Giampaolo Bernini1, Angelica Moretti, Vincenzo Fontana
1Department of Internal Medicine, University of Pisa, Pisa, Italy. g.bernini@med.unipi.it

Objective:
To evaluate whether adenomas arising from the adrenal cortex, a tissue of epithelial origin, are associated with high chromogranin A (CgA) levels and whether such tumors may express and release this protein. In addition, to investigate whether high CgA levels imply a neuroendocrine differentiation of the adrenocortical adenomas and, therefore, represent a humoral marker of malignant transformation of these tumors.
Design:
Plasma CgA of 80 patients with non-functioning, benign adrenocortical adenomas was compared with that of 137 tumor-free subjects. In 15 patients, the masses were surgically removed and CgA was measured 2 months later. The other 65 patients with adrenocortical adenomas underwent clinical and radiological follow-up (range 24-36 months).
Methods:
CgA was evaluated by immunoradiometric assay in peripheral blood and by immunohistochemistry in adrenal tissue specimens.
Results:
An increase in plasma CgA (P<0.001) was observed in patients with adrenocortical adenomas (83.4+/-7.5 ng/ml) in comparison with tumor-free subjects (43.1+/-1.5 ng/ml). The prevalence of high CgA levels was 25% in the former and 0.7% in the latter. By multiple regression analysis, an increase (49%) in the expected median CgA value was estimated for adrenocortical adenomas (P<0.001). Receiver operating characteristic analysis showed a good diagnostic performance of CgA in identifying patients with adrenocortical adenomas (pure accuracy=0.78, 95% CI=0.71-0.84). In the operated patients, CgA levels did not change before (80.6+/-16.5 ng/ml) and after (74.3+/-16.3 ng/ml) surgery and in no case was CgA immunoreactivity found in adenoma tissues. The non-operated patients did not develop signs or symptoms of disease and showed no features of malignant transformation of the masses.
Conclusions:
Our data showed a strong association between adrenocortical adenomas and high CgA levels. CgA hypersecretion was not due to adenoma tissue, which did not show immunoreactivity for CgA. Finally, elevated CgA levels did not represent a humoral marker of malignant transformation of cortical adenomas.

Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:26
Cushing Syndrome I: Introduction
 01:19
Cushing Syndrome II: Pathophysiology
 01:31
Hormones of the Adrenal Glands
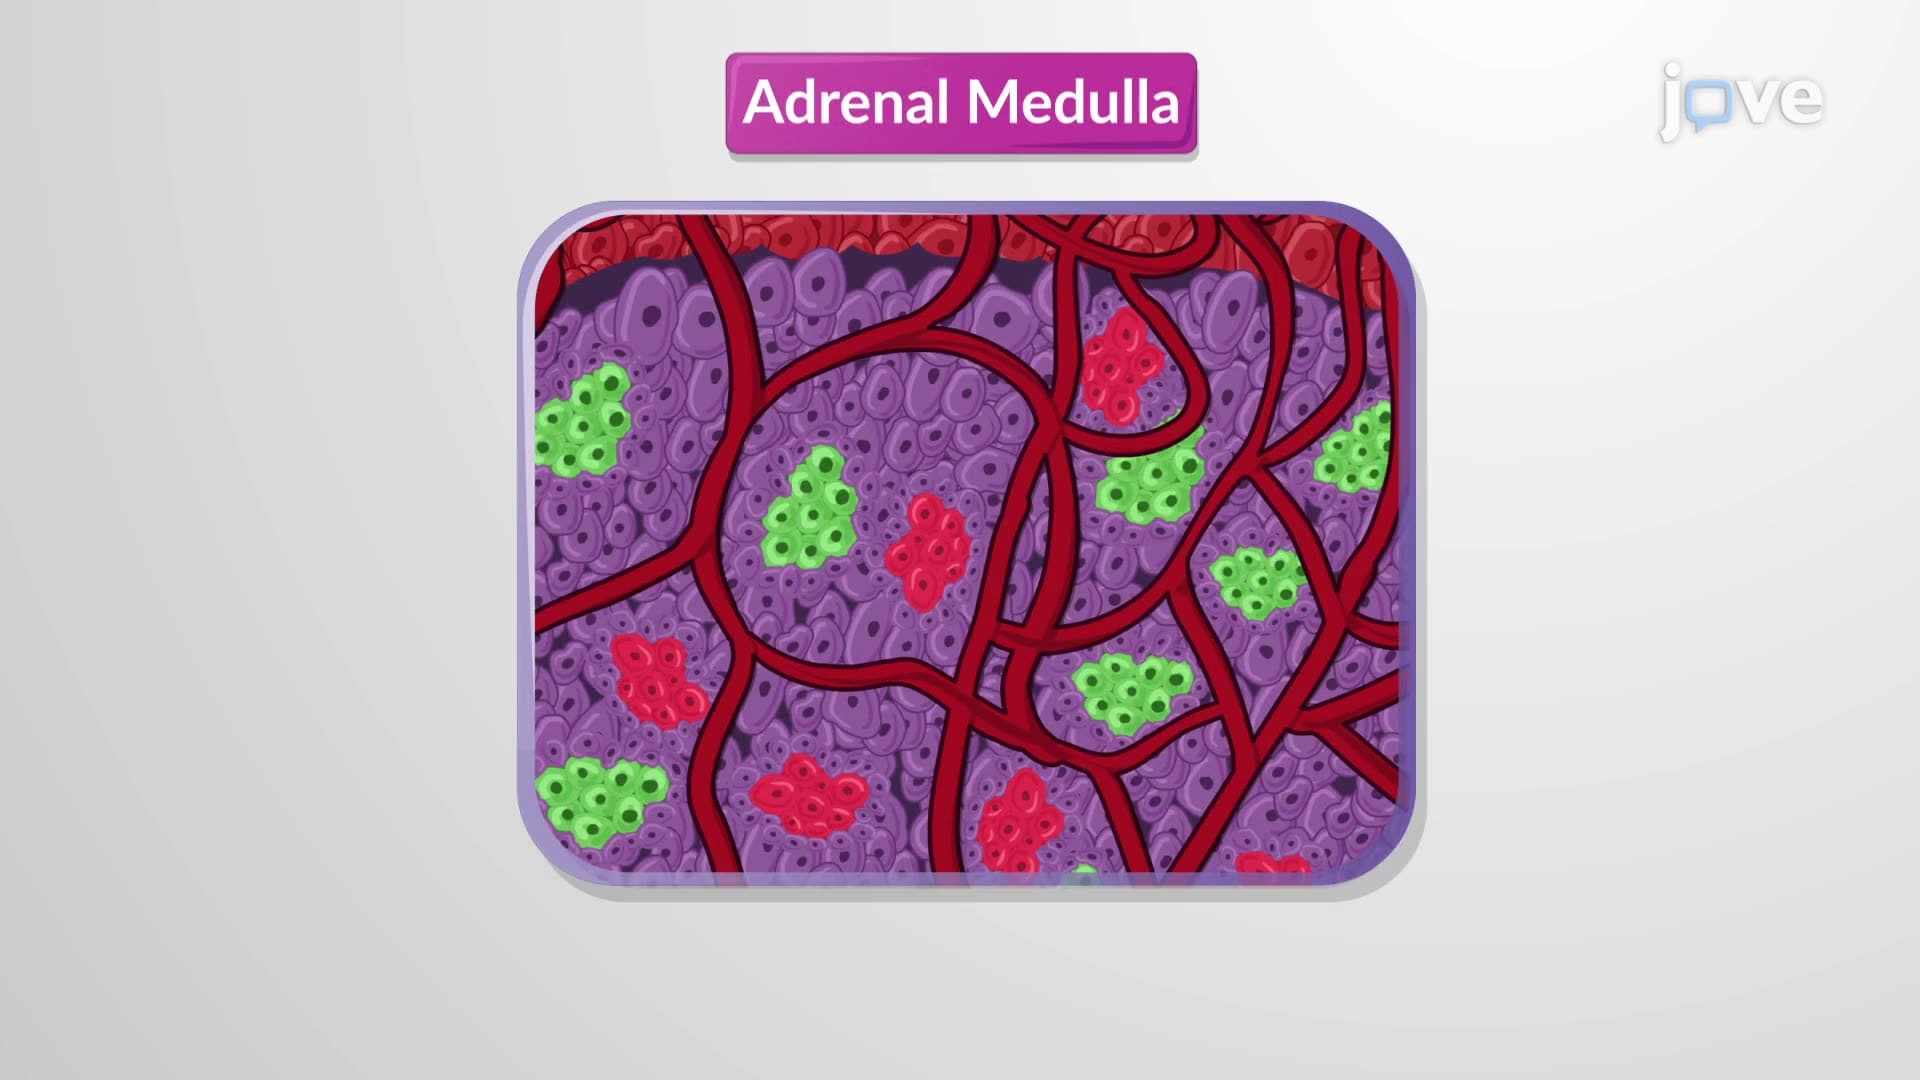
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:17
Anatomy of the Adrenal Glands
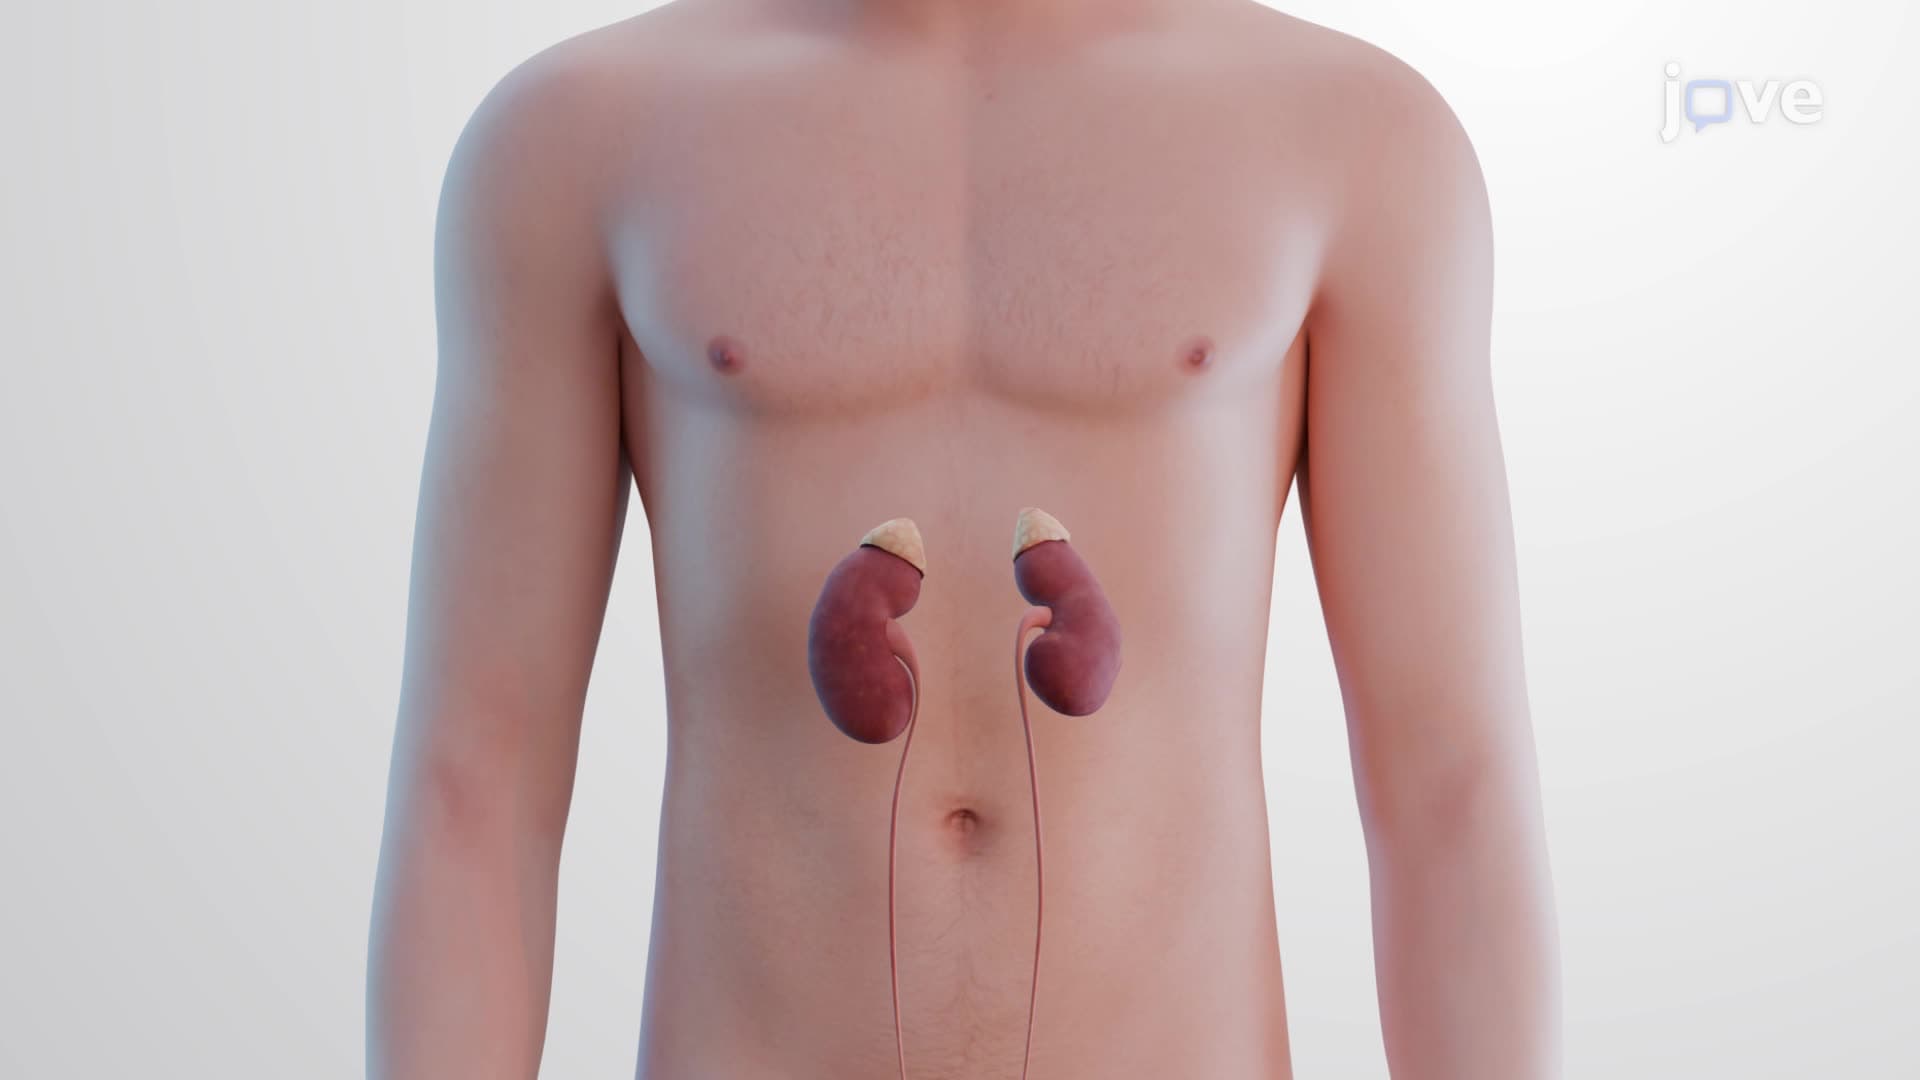
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:27
Sympathetic Pathways: Collateral Ganglia and Adrenal Medulla
Collateral Ganglia
Sympathetic preganglionic axons reach the collateral ganglia along the route of splanchnic nerves. These nerves bypass the sympathetic trunk and communicate with sympathetic postganglionic neurons housed in the prevertebral ganglia. These ganglia supply the organs of the abdominopelvic cavity.
The greater splanchnic nerve, formed by the...