Related Experiment Video
Updated: Aug 23, 2026


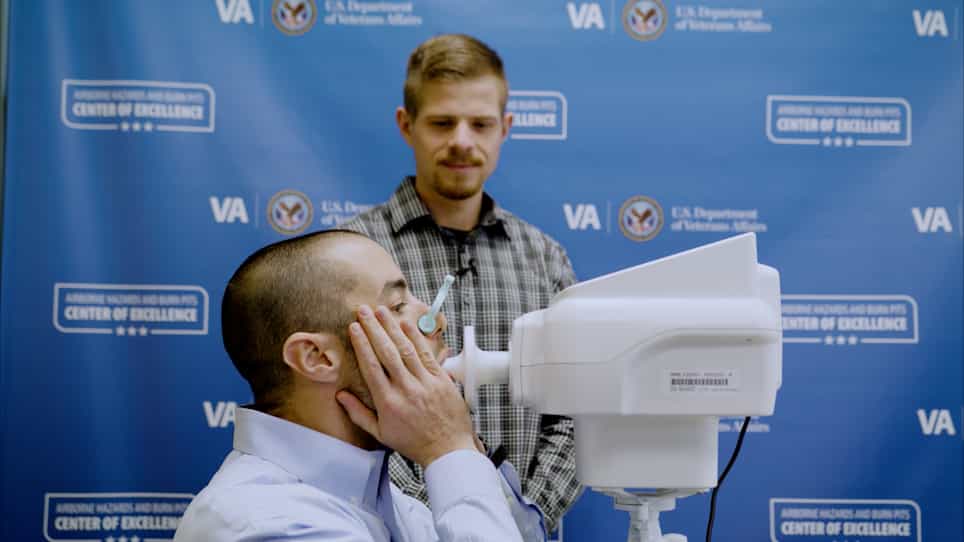
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
High-frequency oscillatory ventilation in adults: the Toronto experience
Sangeeta Mehta1, John Granton, Rod J MacDonald
1Mount Sinai Hospital, 600 University Ave, No. 1818, Toronto, ON, Canada, M5G 1X5. geeta.mehta@utoronto.ca

Study Objectives:
To review the clinical experience with high-frequency oscillatory ventilation (HFOV) in three medical-surgical ICUs in Toronto, ON, Canada, and to describe patient characteristics, HFOV strategies, and outcomes.
Design And Patients:
Retrospective chart review of all patients treated with HFOV at three academic university-affiliated ICUs since 1998. The data extracted included patient demographics, etiology of respiratory failure, ventilator settings, and gas exchange and cardiovascular data from baseline to 72 h of treatment, as well as at the transition from HFOV to conventional ventilation (CV). Heart rate and BP were recorded at regular intervals in all patients, and hemodynamic data were recorded in 32 patients who had pulmonary artery catheters in place. Cointerventions and ICU mortality were also recorded.
Measurements And Results:
A total of 156 adults (67 women and 89 men; mean [+/- SD] age, 48 +/- 18 years; mean acute physiology and chronic health evaluation [APACHE] II score, 23.8 +/- 7.5) with severe ARDS (ie, mean Pao(2)/fraction of inspired oxygen [Fio(2)] ratio, 91 +/- 48 mm Hg; mean oxygenation index [OI], 31 +/- 14) who had received CV for a duration of 5.6 +/- 7.6 days underwent 171 trials of HFOV. HFOV was discontinued within 4 h in 19 patients (12%) because of difficulties with oxygenation, ventilation, or hemodynamics. Pao(2)/Fio(2) ratios and OI ([Fio(2) x mean airway pressure x 100]/Pao(2)) improved significantly with the application of HFOV, and this benefit persisted for the 72-h study duration. Significant changes in hemodynamics following HFOV initiation included an increase in central venous pressure and a reduction in cardiac output (throughout the 72 h), and an increase in pulmonary artery occlusion pressure (at 3 and 6 h). Patients were treated with HFOV for 5.1 +/- 6.3 days. The 30-day mortality rate was 61.7%. Pneumothorax occurred in 21.8% of patients, 43.6% of patients were treated with inhaled nitric oxide, and 37.2% of patients were treated with steroids. Independent predictors of mortality on multivariate analysis were older age, higher APACHE II score, lower pH at the initiation of HFOV, and a greater number of days receiving CV prior to HFOV.
Conclusions:
HFOV has beneficial effects on Pao(2)/Fio(2) ratios and OI, and may be an effective rescue therapy for adults with severe oxygenation failure. The early institution of HFOV may be advantageous.

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:25
Hyperpnea and Hyperventilation
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)