Related Experiment Video
Updated: Aug 5, 2026

Surgical Technique for Spinal Cord Delivery of Therapies: Demonstration of Procedure in Gottingen Minipigs
Published on: December 7, 2012
Complications with 25-gauge and 27-gauge Whitacre needles during combined spinal-epidural analgesia in labor
R Landau1, C F Ciliberto, S R Goodman
1Department of Anesthesiology, Columbia University College of Physicians and Surgeons, New York, NY 10032, USA.

Needle size and shape may influence the incidence of paresthesias, post-dural puncture headache and other complications during combined spinal-epidural (CSE) procedures. We have noted a relatively high incidence of transient paresthesias during placement of the spinal needle during CSE for labor analgesia. The purpose of this study was to compare the occurrence of paresthesia and post-dural puncture headache in parturients who received CSE analgesia with either a 25-gauge or 27-gauge Whitacre needle. In a prospective observational study, data were gathered from 478 consecutive women receiving labor analgesia. Incidence, duration, and character of any paresthesias upon spinal needle placement and the incidence and treatment of headache were recorded. The incidence of paresthesia with the two needles was similar (16% with 25-gauge vs 15.4% with 27 gauge) but the incidence of post-dural puncture headache was higher with the 25-gauge needle (4% vs 0.7% with 27 gauge, P < 0.05). Our data suggest that with Whitacre needles, 27-gauge might be preferable to 25-gauge needles to reduce the rate of post-dural puncture headache in parturients but that they do not alter the incidence of transient paresthesias.
Needle size and shape may influence the incidence of paresthesias, post-dural puncture headache and other complications during combined spinal-epidural (CSE) procedures. We have noted a relatively high incidence of transient paresthesias during placement of the spinal needle during CSE for labor analgesia. The purpose of this study was to compare the occurrence of paresthesia and post-dural puncture headache in parturients who received CSE analgesia with either a 25-gauge or 27-gauge Whitacre needle. In a prospective observational study, data were gathered from 478 consecutive women receiving labor analgesia. Incidence, duration, and character of any paresthesias upon spinal needle placement and the incidence and treatment of headache were recorded. The incidence of paresthesia with the two needles was similar (16% with 25-gauge vs 15.4% with 27 gauge) but the incidence of post-dural puncture headache was higher with the 25-gauge needle (4% vs 0.7% with 27 gauge, P < 0.05). Our data suggest that with Whitacre needles, 27-gauge might be preferable to 25-gauge needles to reduce the rate of post-dural puncture headache in parturients but that they do not alter the incidence of transient paresthesias.
Related Concept Videos
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
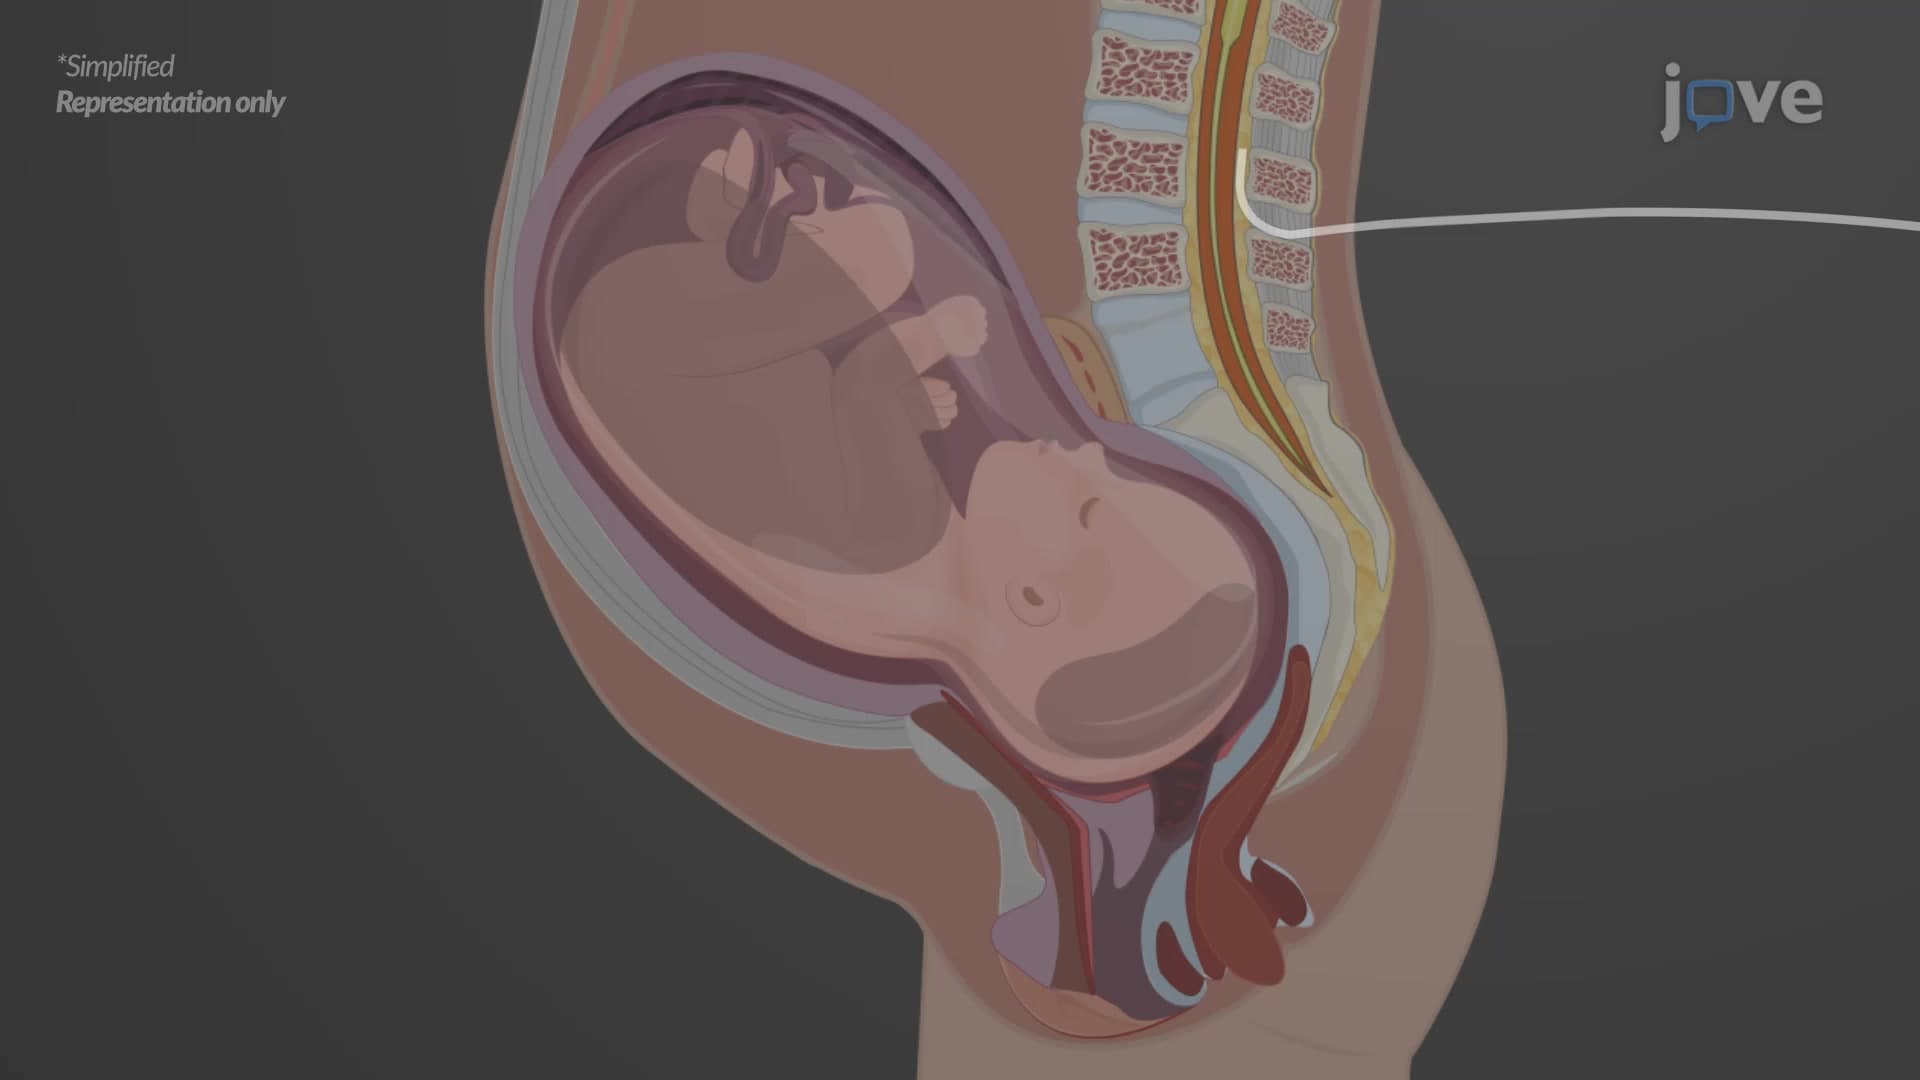
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...