Related Experiment Video
Updated: Aug 22, 2026
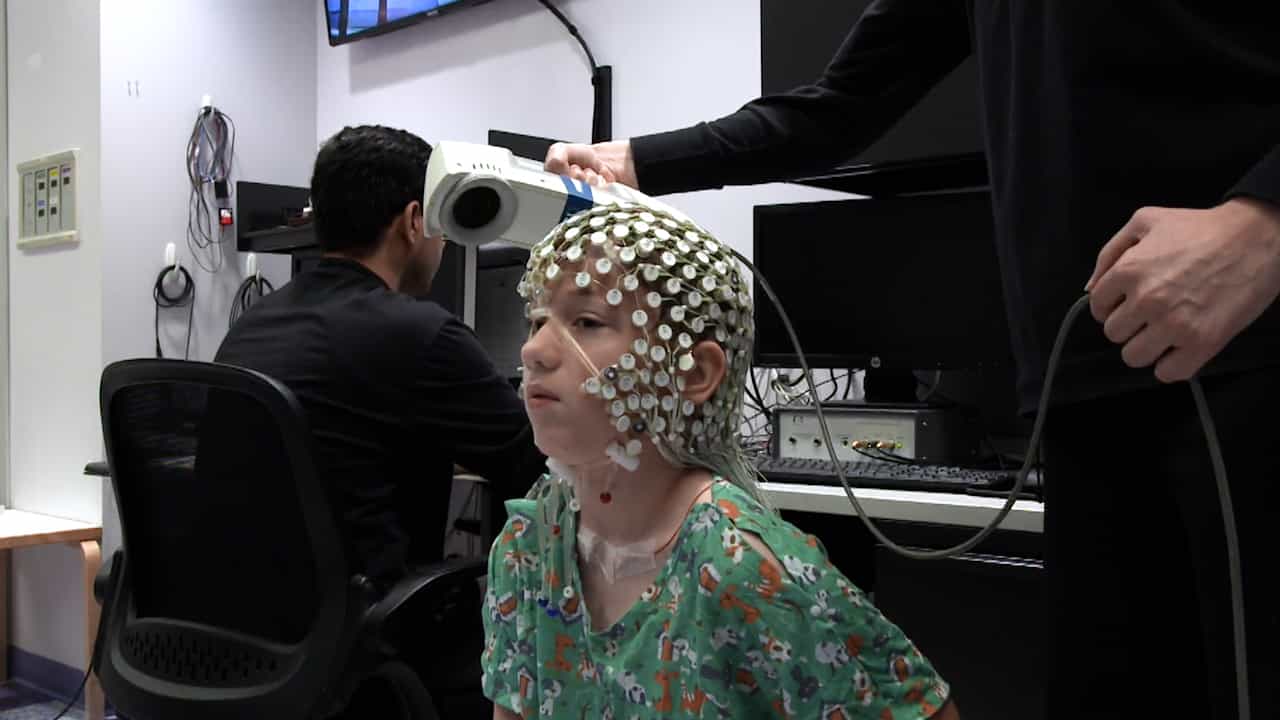
Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
[Refractory partial epilepsy: morphological imaging in children]
1Neuroradiologie, CHU Timone, Université de la Méditerranée, 13000 Marseille, France. craybaud@mail.ap-hm.fr

Insights
Pediatric refractory partial epilepsy imaging requires specialized approaches due to immature brains. Tailored neuroimaging and clinical correlation are crucial for surgical planning in children.
Area of Science:
- Pediatric Neurology
- Neuroradiology
- Epileptology
Context:
- Refractory partial epilepsy in children presents unique diagnostic challenges.
- Surgical intervention is often considered, necessitating precise neuroimaging.
- Pediatric brain development influences imaging interpretation.
Purpose:
- To outline the specialized neuroimaging strategies for pediatric refractory partial epilepsy.
- To highlight differences in imaging findings compared to adults.
- To emphasize the importance of integrating imaging with clinical and EEG data.
Summary:
- Pediatric epilepsy imaging shares similarities with adult approaches but requires modifications for immature brains and sedation risks.
- Malformations of cortical development, including focal cortical dysplasias and tumors, are common specific lesions.
- Temporal lobe lesions in children differ from adults, with mesial sclerosis being less frequent.
Impact:
- Optimized neuroimaging protocols can improve surgical candidacy assessment in pediatric epilepsy.
- Understanding age-specific imaging characteristics aids in accurate diagnosis and lesion identification.
- This approach facilitates more confident surgical decision-making based on morphological data in children.
Abstract:
The imaging approach to refractory partial epilepsy in children is essentially the same as the one used for any epilepsy at that age, except that surgery being generally proposed, it has to be oriented and complete. Yet there are differences. Sedation introduces a risk. The brain of the young child is still immature, and specially designed sequences are needed for proper imaging. Brain immaturity also modifies the usual image contrast and may conceal (or on the contrary enhance) an area of dysplasia. Repeating studies after a few months has to be considered. Obviously, the brain imaging study has to be closely oriented by the clinical and EEG findings and if necessary, by functional imaging data. The abnormalities are extremely diverse as compared to what is observed in an adult population. The brain may be "normal", or demonstrate only non-specific abnormalities. Among the specific lesions, scars are common, and above all, malformations, especially malformations of cortical development (even diffuse malformations are commonly expressed by partial seizures), including focal cortical dysplasias and their close relatives, dysplastic tumors. In children, the most common lesions in the temporal lobe are scars, tumors/dysplastic lesions and malformative lesions, while mesial sclerosis is significantly less common than in adults. In the event of a simple lesion, the decision for surgery on the basis of morphological data alone is more easily made in children than in adults.

