Related Experiment Videos
Management of Fecal Incontinence in Children Without Functional Fecal Retention
Licia Pensabene1, Samuel Nurko
1Department of Gastroenterology and Nutrition, Hunnewell Ground, 300 Longwood Avenue, Boston, MA 02115, USA. Samuel.Nurko@childrens.harvard.edu

Insights
Managing childhood fecal incontinence is challenging. New treatments like the Antegrade Colonic Enema (ACE) offer improved predictability and independence for children with severe cases.
Area of Science:
- Pediatric Gastroenterology
- Colorectal Surgery
- Child Psychology
Background:
- Fecal incontinence in children presents significant management challenges and profound social impacts.
- Causes range from functional fecal retention and soiling to organic issues like congenital malformations affecting the anorectum or spinal cord.
Purpose of the Study:
- To outline the diverse therapeutic strategies for pediatric fecal incontinence based on underlying causes.
- To highlight advancements in bowel management programs aiming for social continence, predictability, and independence.
Main Methods:
- Review of therapeutic regimens for nonretentive fecal soiling, including behavioral approaches and cautious laxative use.
- Description of multi-modal treatments for congenital/neuropathic incontinence, addressing stool consistency, colonic transit, and anorectal function.
- Introduction of the Antegrade Colonic Enema (ACE) procedure for severe cases.
Main Results:
- Nonretentive fecal soiling management involves education, support, and reward-based toilet training; biofeedback and laxatives require careful consideration.
- Congenital/neuropathic incontinence requires interventions targeting stool properties, transit, and evacuation, with options like dietary changes, medications, and enemas.
- The Antegrade Colonic Enema (ACE) procedure provides a continent conduit, enabling predictable and independent bowel management.
Conclusions:
- Effective fecal incontinence management in children necessitates tailored approaches based on etiology.
- The Antegrade Colonic Enema (ACE) represents a significant advancement, revolutionizing treatment by enhancing patient independence and predictability.
Abstract:
The management of the fecal incontinence in children is difficult, and its social consequences are usually devastating. The general objectives of any bowel program are to produce social continence, predictability, and eventually independence. How to achieve those goals depends in part on the underlying condition. In children, fecal incontinence can occur from a variety of conditions. The most common is overflow incontinence from functional fecal retention, but it can also occur in otherwise healthy children with functional nonretentive fecal soiling or in children with organic causes of fecal incontinence, such as congenital malformations, or any other condition affecting the anorectum, anal sphincters, or the spinal cord. The therapeutic regimen that is recommended in patients with nonretentive fecal soiling consists of explanation and support for the child and parents, a nonaccusatory approach, and a toilet training program with a rewarding system. Biofeedback does not play an important role, and laxatives need to be used with caution, as they may exacerbate the incontinence. For those patients with congenital/neuropathic incontinence a combination of maneuvers to change stool consistency, colonic transit, anorectal function, and rectosigmoid evacuation is used. Stool consistency can be changed with the use of dietary interventions or medications. Stool transit can be slowed (antimotility agents) or accelerated (laxatives) with the use of medications. Anorectal function can be improved with the use of biofeedback or procedures to alter sphincter pressure, and the production of a bowel movement can be induced with maneuvers to empty the sigmoid (suppositories, enemas). With the recent advent of the Antegrade Colonic Enema (ACE), the patient is then able to be predictable and independent. This procedure creates a continent conduit from the skin to the cecum that can be catheterized or accessed for self-administration of enemas. The ACE has revolutionized the treatment of children with fecal incontinence.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:26
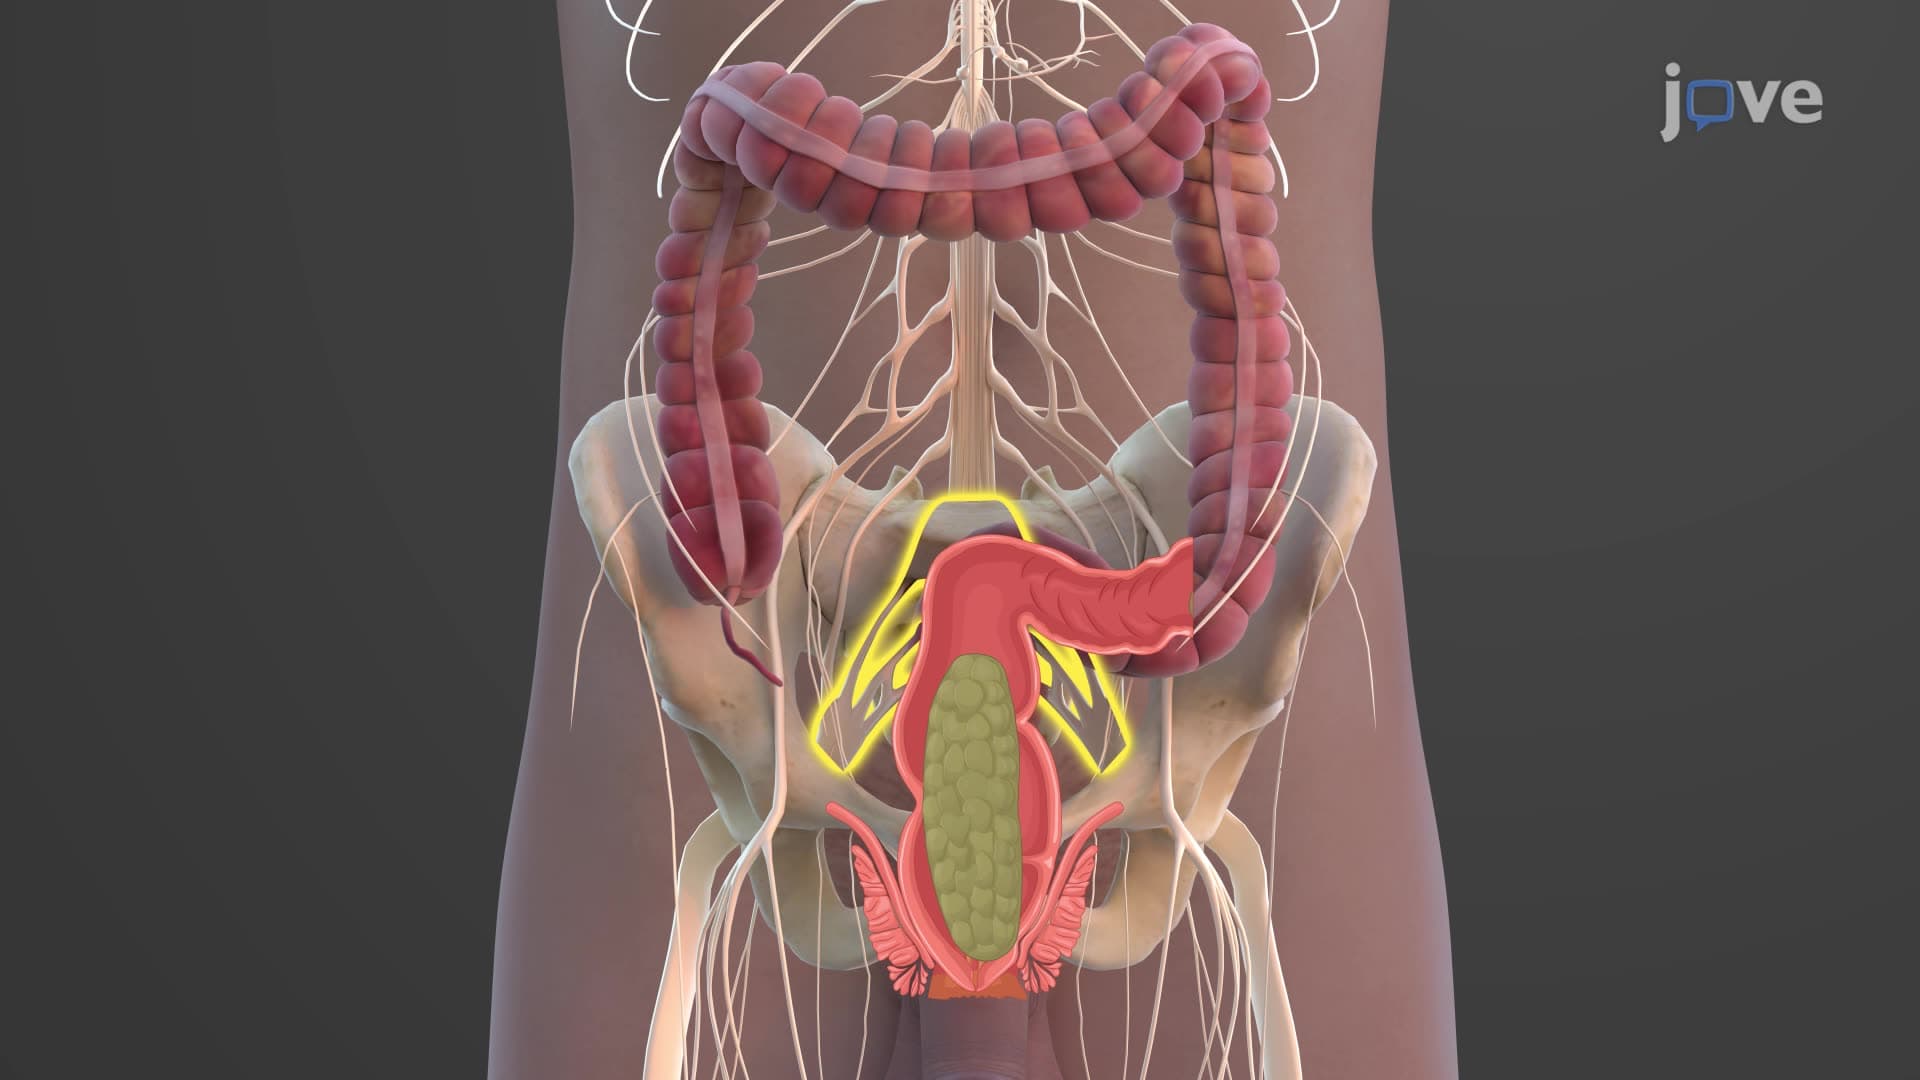
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...