Related Experiment Video
Updated: Aug 22, 2026
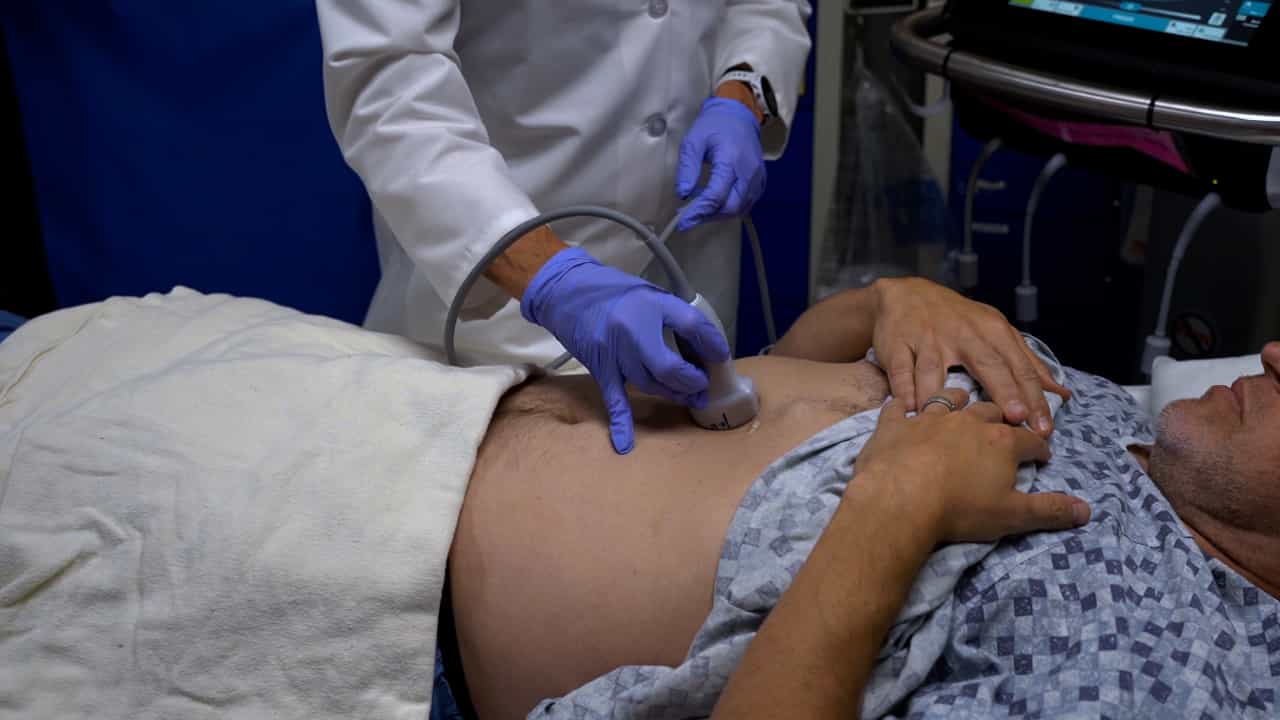
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
Gastric emptying in children with cerebral palsy and gastroesophageal reflux
Kleomenis Spiroglou1, Ioannis Xinias, Nikolaos Karatzas
1Third Department of Pediatrics, Hippocration Hospital Thessaloniki, Thessaloniki, Greece.

Insights
Gastroesophageal reflux is common in children with cerebral palsy, often causing complications. However, delayed gastric emptying time does not influence reflux severity in these patients.
Area of Science:
- Pediatric Gastroenterology
- Neurology
- Medical Imaging
Background:
- Gastroesophageal reflux (GER) is frequently observed in children with cerebral palsy (CP).
- Delayed gastric emptying is a suspected contributor to GER in this population.
- The relationship between gastric emptying time and GER severity in children with CP remains unclear.
Purpose of the Study:
- To investigate the association between gastric emptying time and the severity of gastroesophageal reflux in children with cerebral palsy.
- To determine if gastric emptying influences reflux complications in this patient group.
Main Methods:
- Seventy-six children with cerebral palsy and GER symptoms underwent 24-hour pH monitoring.
- Gastric emptying time was assessed using gastric scintigraphy.
- A control group of 28 children with resistant asthma was included for emptying time comparison.
Main Results:
- Gastroesophageal reflux was diagnosed in 51.3% of children with cerebral palsy, with 53.8% classified as severe.
- Common complications included iron deficiency (51.3%), anemia (41.0%), and malnutrition (33.3%).
- No significant difference in gastric emptying time was found between children with CP and the control group, nor was a relationship identified between emptying time and reflux severity.
Conclusions:
- Moderate to severe gastroesophageal reflux is prevalent in children with cerebral palsy and is associated with significant complications.
- Delayed gastric emptying time is not a contributing factor to the severity of reflux in this population.
- The study findings suggest that interventions targeting gastric emptying may not be effective in managing reflux severity in children with CP.
Abstract:
Gastric emptying time is considered a factor in the increased frequency of gastroesophageal reflux in children with cerebral palsy. It is unknown if emptying time influences the severity of reflux. In this study, 76 cerebral palsy patients with reflux indicative symptoms were investigated by 24-hour pH monitoring. Reflux complications were also studied. Emptying time in children with reflux was investigated using gastric scintigraphy. Twenty-eight children with resistant asthma scanned for pulmonary aspiration were studied as control subjects for emptying time. Reflux was diagnosed in 51.3%; it was severe in 53.8%, moderate in 38.5%, and mild in 7.7%. Occurrence of reflux did not differ significantly among different forms of cerebral palsy or between males and females. The most frequent complications in reflux-positive patients were iron deficiency (51.3%), anemia (41.0%), malnutrition (33.3%), recurrent upper respiratory tract infections (28.2%), and low body weight (28.2%). Patients without reflux had less frequent complications. Gastric emptying time measured by gastric scintigraphy in 28 patients with reflux manifested no difference in comparison to the control group (P > 0.05). No relationship was found between emptying time and reflux severity (P > 0.05). In conclusion, reflux (moderate or severe) is common in children with cerebral palsy, frequently leading to complications but no delayed emptying time. The patients described in this report had no delayed emptying time. There was also no relationship between emptying time and severity of reflux.

Related Concept Videos
 01:16
Gastric Emptying
 01:11
Pyloric Obstruction
 01:27
Esophageal Achalasia
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:20
Gastrointestinal Motility Disorders
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...