Related Experiment Video
Updated: Aug 22, 2026

Trans-Tympanic Drug Delivery for the Treatment of Ototoxicity
Published on: March 16, 2018
Vestibular toxicity due to inhaled tobramycin in a patient with renal insufficiency
Randall S Edson1, Robert H Brey, Thomas J McDonald
1Division of Infectious Diseases, Mayo Clinic College of Medicine, 200 First St SW, Rochester, MN 55905, USA. edson.randall@mayo.edu

Abstract:
Inhaled tobramycin is being used increasingly in patients with cystic fibrosis and other forms of bronchiectasis for treatment of bronchial colonization with Pseudomonas aeruginosa. The goal of inhaled antibiotics is to provide maximal concentrations at the site of infection without risking systemic toxicity. We report an unusual case of reversible vestibular toxicity due to inhaled tobramycin in a patient with renal failure who was undergoing hemodialysis. Although systemic absorption after inhaled tobramycin is reportedly negligible, no recommendations have been published regarding monitoring of serum concentrations in patients receiving this form of therapy. We suggest that clinicians consider monitoring serum concentrations of tobramycin in patients at risk of renal toxicity and/or ototoxicity, such as those with predisposing renal or otologic compromise. Further studies in at-risk patients are needed to determine the optimal frequency and timing of such monitoring.
More Related Videos
 07:38
Induction of Nephrotic Syndrome in Mice by Retrobulbar Injection of Doxorubicin and Prevention of Volume Retention by Sustained Release Aprotinin
Published on: May 6, 2018
 07:10
Direct Intrabronchial Administration to Improve the Selective Agent Deposition Within the Mouse Lung
Published on: May 20, 2019
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
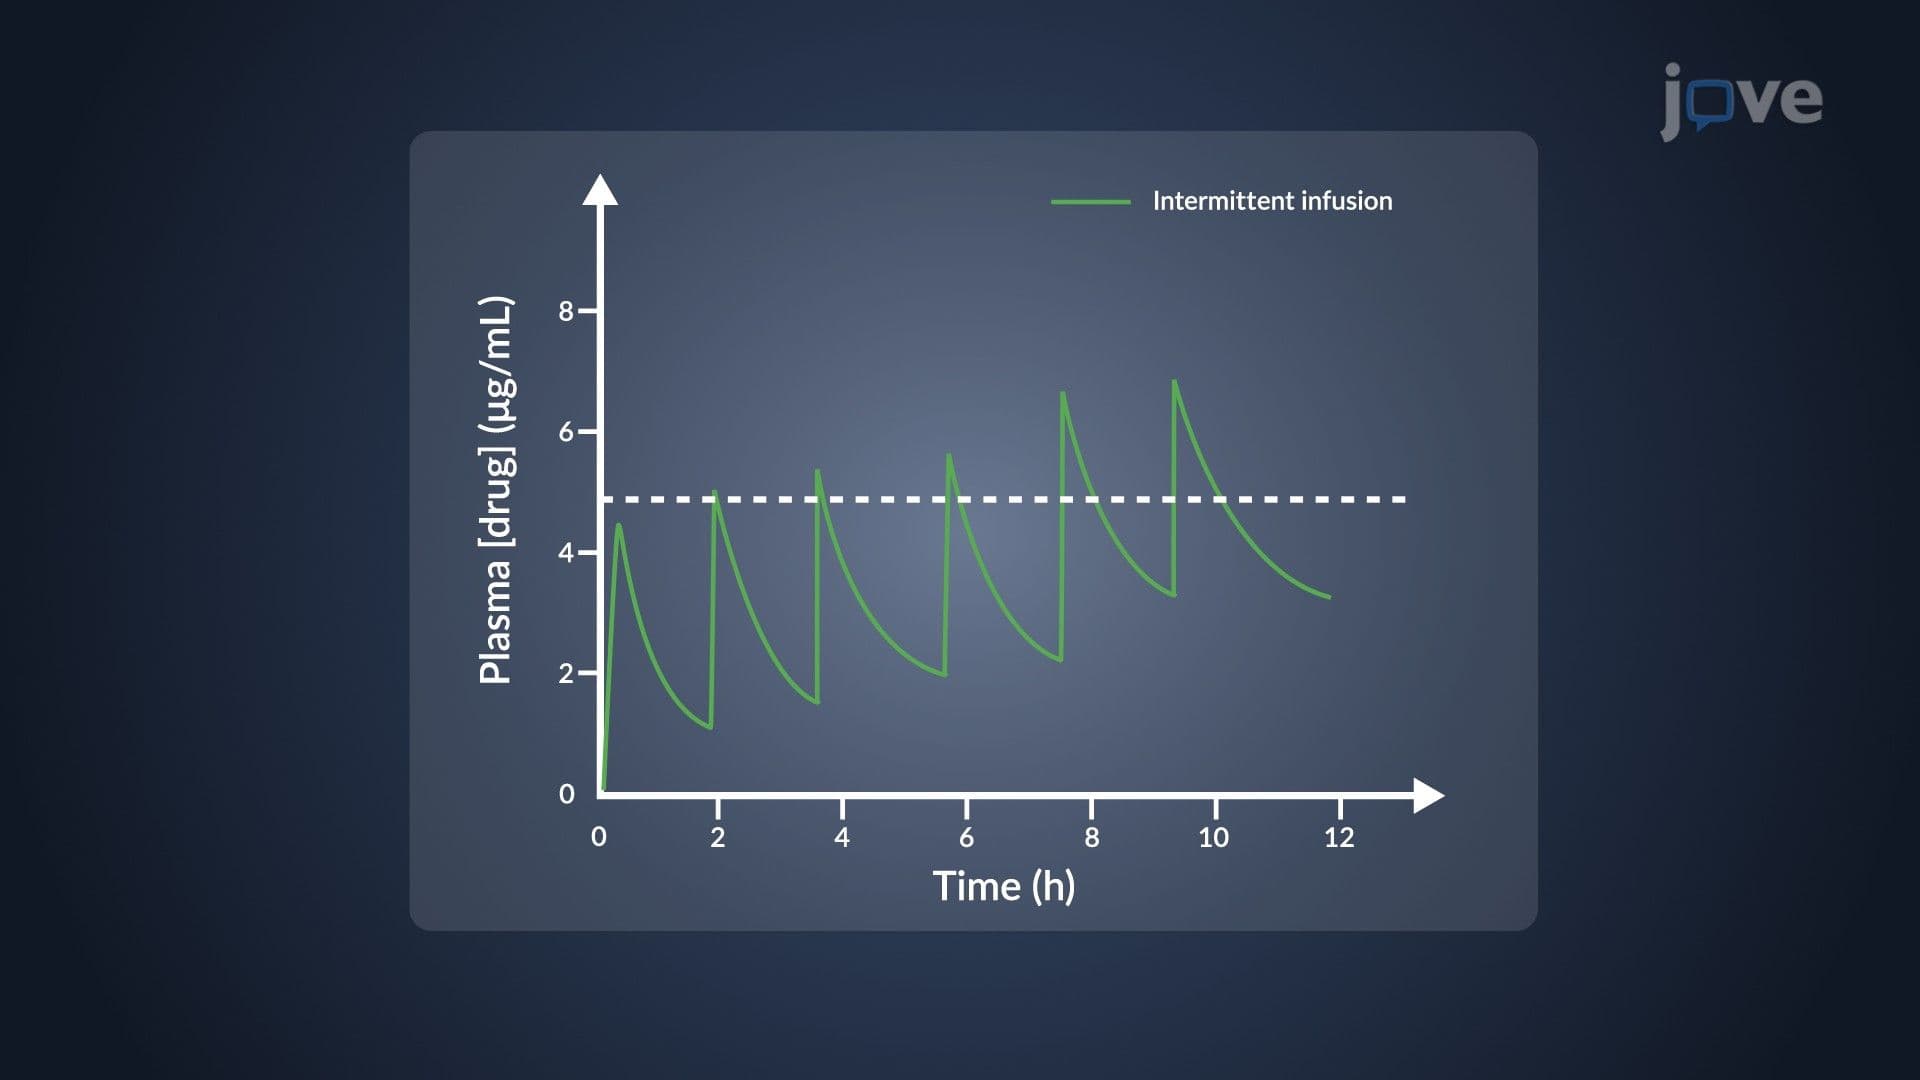
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion