Related Experiment Video
Updated: Aug 22, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
What is the practical conversion dose when changing from epoetin alfa to darbepoetin outside of clinical trials?
1Department of Renal Medicine, Gosford Hospital, Gosford, New South Wales, Australia. sroger@doh.health.nsw.gov.au

Background:
The recommended conversion dose for changing from epoetin alfa to darbepoetin alfa is 200 units to 1 microg. However, this may result in the over treatment of uraemic anaemia.
Methods:
All in-centre haemodialysis patients (n = 60) were converted from an existing subcutaneous epoetin alfa regimen to weekly intravenous darbepoetin alfa. The protocol for anaemia management included a target haemoglobin (Hb) concentration of 120-130 g/L and a ferritin of 300-600 microg/L. Patient treatments were converted from subcutaneous epoetin alfa to weekly, intravenous darbepoetin alfa at month 0, at a conversion dose of 200 units epoetin alfa to 1 microg darbepoetin.
Results:
Both Hb and ferritin concentrations remained within the target range, but darbepoetin dosages fell from 50.8 to 42.3 microg/week by month 3 (P = 0.02). The initial conversion factor of 210 units/microg rose to 275 units/microg (P = 0.01) at month 4. No difference in conversion dosage could be determined between patients who were epoetin sensitive (<200 units/kg per week) or resistant (>200 units/kg per week, P = NS). Patients were then switched to fortnightly darbepoetin alfa dosing treatments; the existing weekly dose being doubled and Hb levels fell from 125 to 110 g/L (P < 0.0001), despite an increase in the mean dose from 44.9 to 47.5 microg/week (P = 0.02).
Conclusion:
The original dosage reduction after the switch from epoetin alfa to weekly intravenous darbepoetin alfa may offset the increased relative cost of the latter. When administered weekly and intravenously, darbepoetin alfa maintains Hb at a more favourable conversion rate than is currently recommended.
Related Concept Videos
 01:28
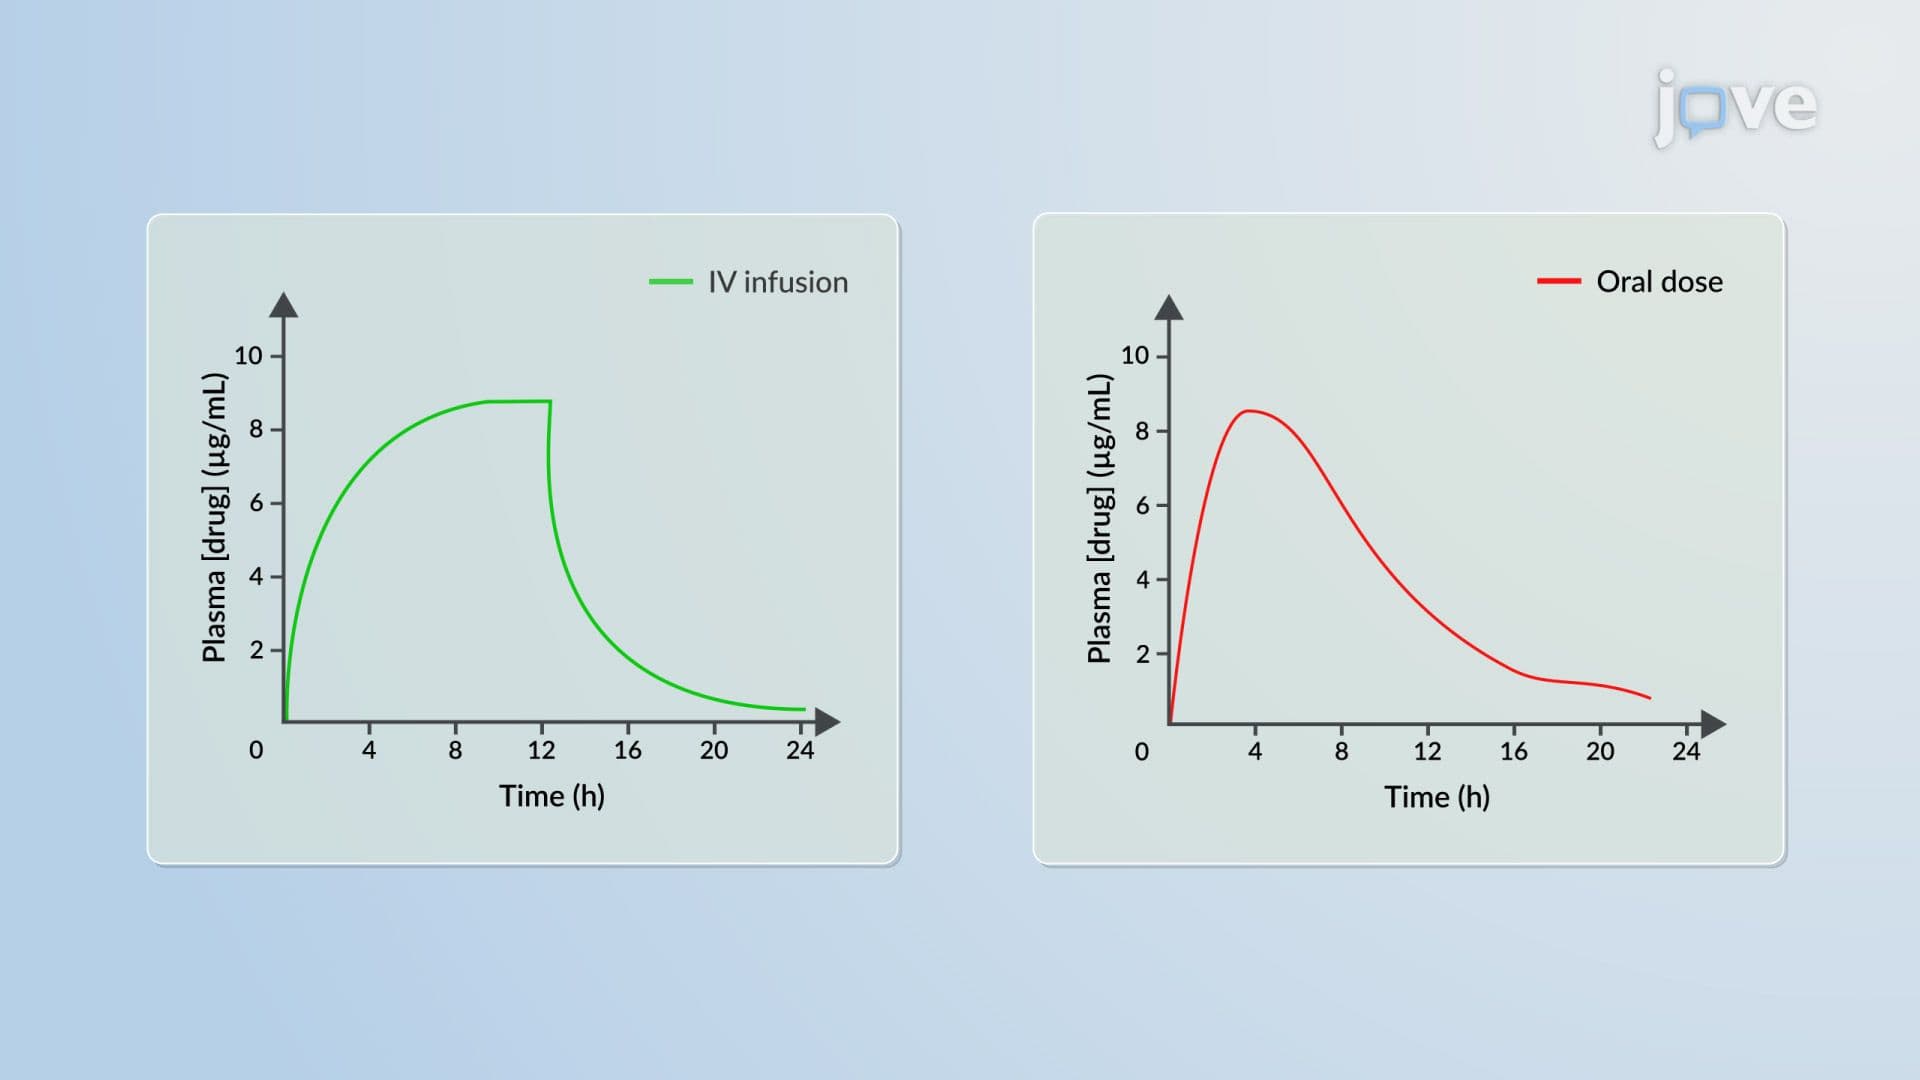
IV Infusion to Oral Dosing: Conversion Methods
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:09
Bioequivalence of Drugs: Drugs with Multiple Indications